


Key takeaways
- Extubation readiness thresholds include Rate ≤15-20 bpm, PIP ≤14-16 cm H2O, MAP ≤7-8 cm H2O on conventional ventilation, or MAP ≤8-10 cm H2O on HFOV, with FiO2 <0.30-0.40.
- Caffeine citrate loading dose is 20 mg/kg, with standard maintenance of 5-10 mg/kg/day and high maintenance of 10-20 mg/kg/day for frequent apnea or difficult weaning.
- Extubation Readiness Trials use CPAP of 5-7 cm H2O via the endotracheal tube over a 3 to 10 minute observation window to predict extubation success.
- Permissive hypercapnia accepts PaCO2 of 55-65 mmHg with pH >7.20 to facilitate weaning and minimize barotrauma.
- Absolute reintubation criteria include refractory respiratory acidosis, persistent hypoxemia requiring FiO2 >0.60-0.70, hemodynamic instability, and severe unremitting work of breathing leading to exhaustion.
References
- Shalish W, Sant’Anna G, Keszler M. Weaning and Extubation From Mechanical Ventilation. In: Goldsmith’s Assisted Ventilation of the Neonate. 7th ed.

Neonatal Weaning and Extubation from Mechanical Ventilation
Evidence-Based Strategies, Readiness, and Post-Extubation Management
Shalish W, Sant’Anna G, Keszler M. Weaning and Extubation From Mechanical Ventilation. In: Goldsmith’s Assisted Ventilation of the Neonate. 7th ed.
Invasive Weaning Strategies: Modality Comparison
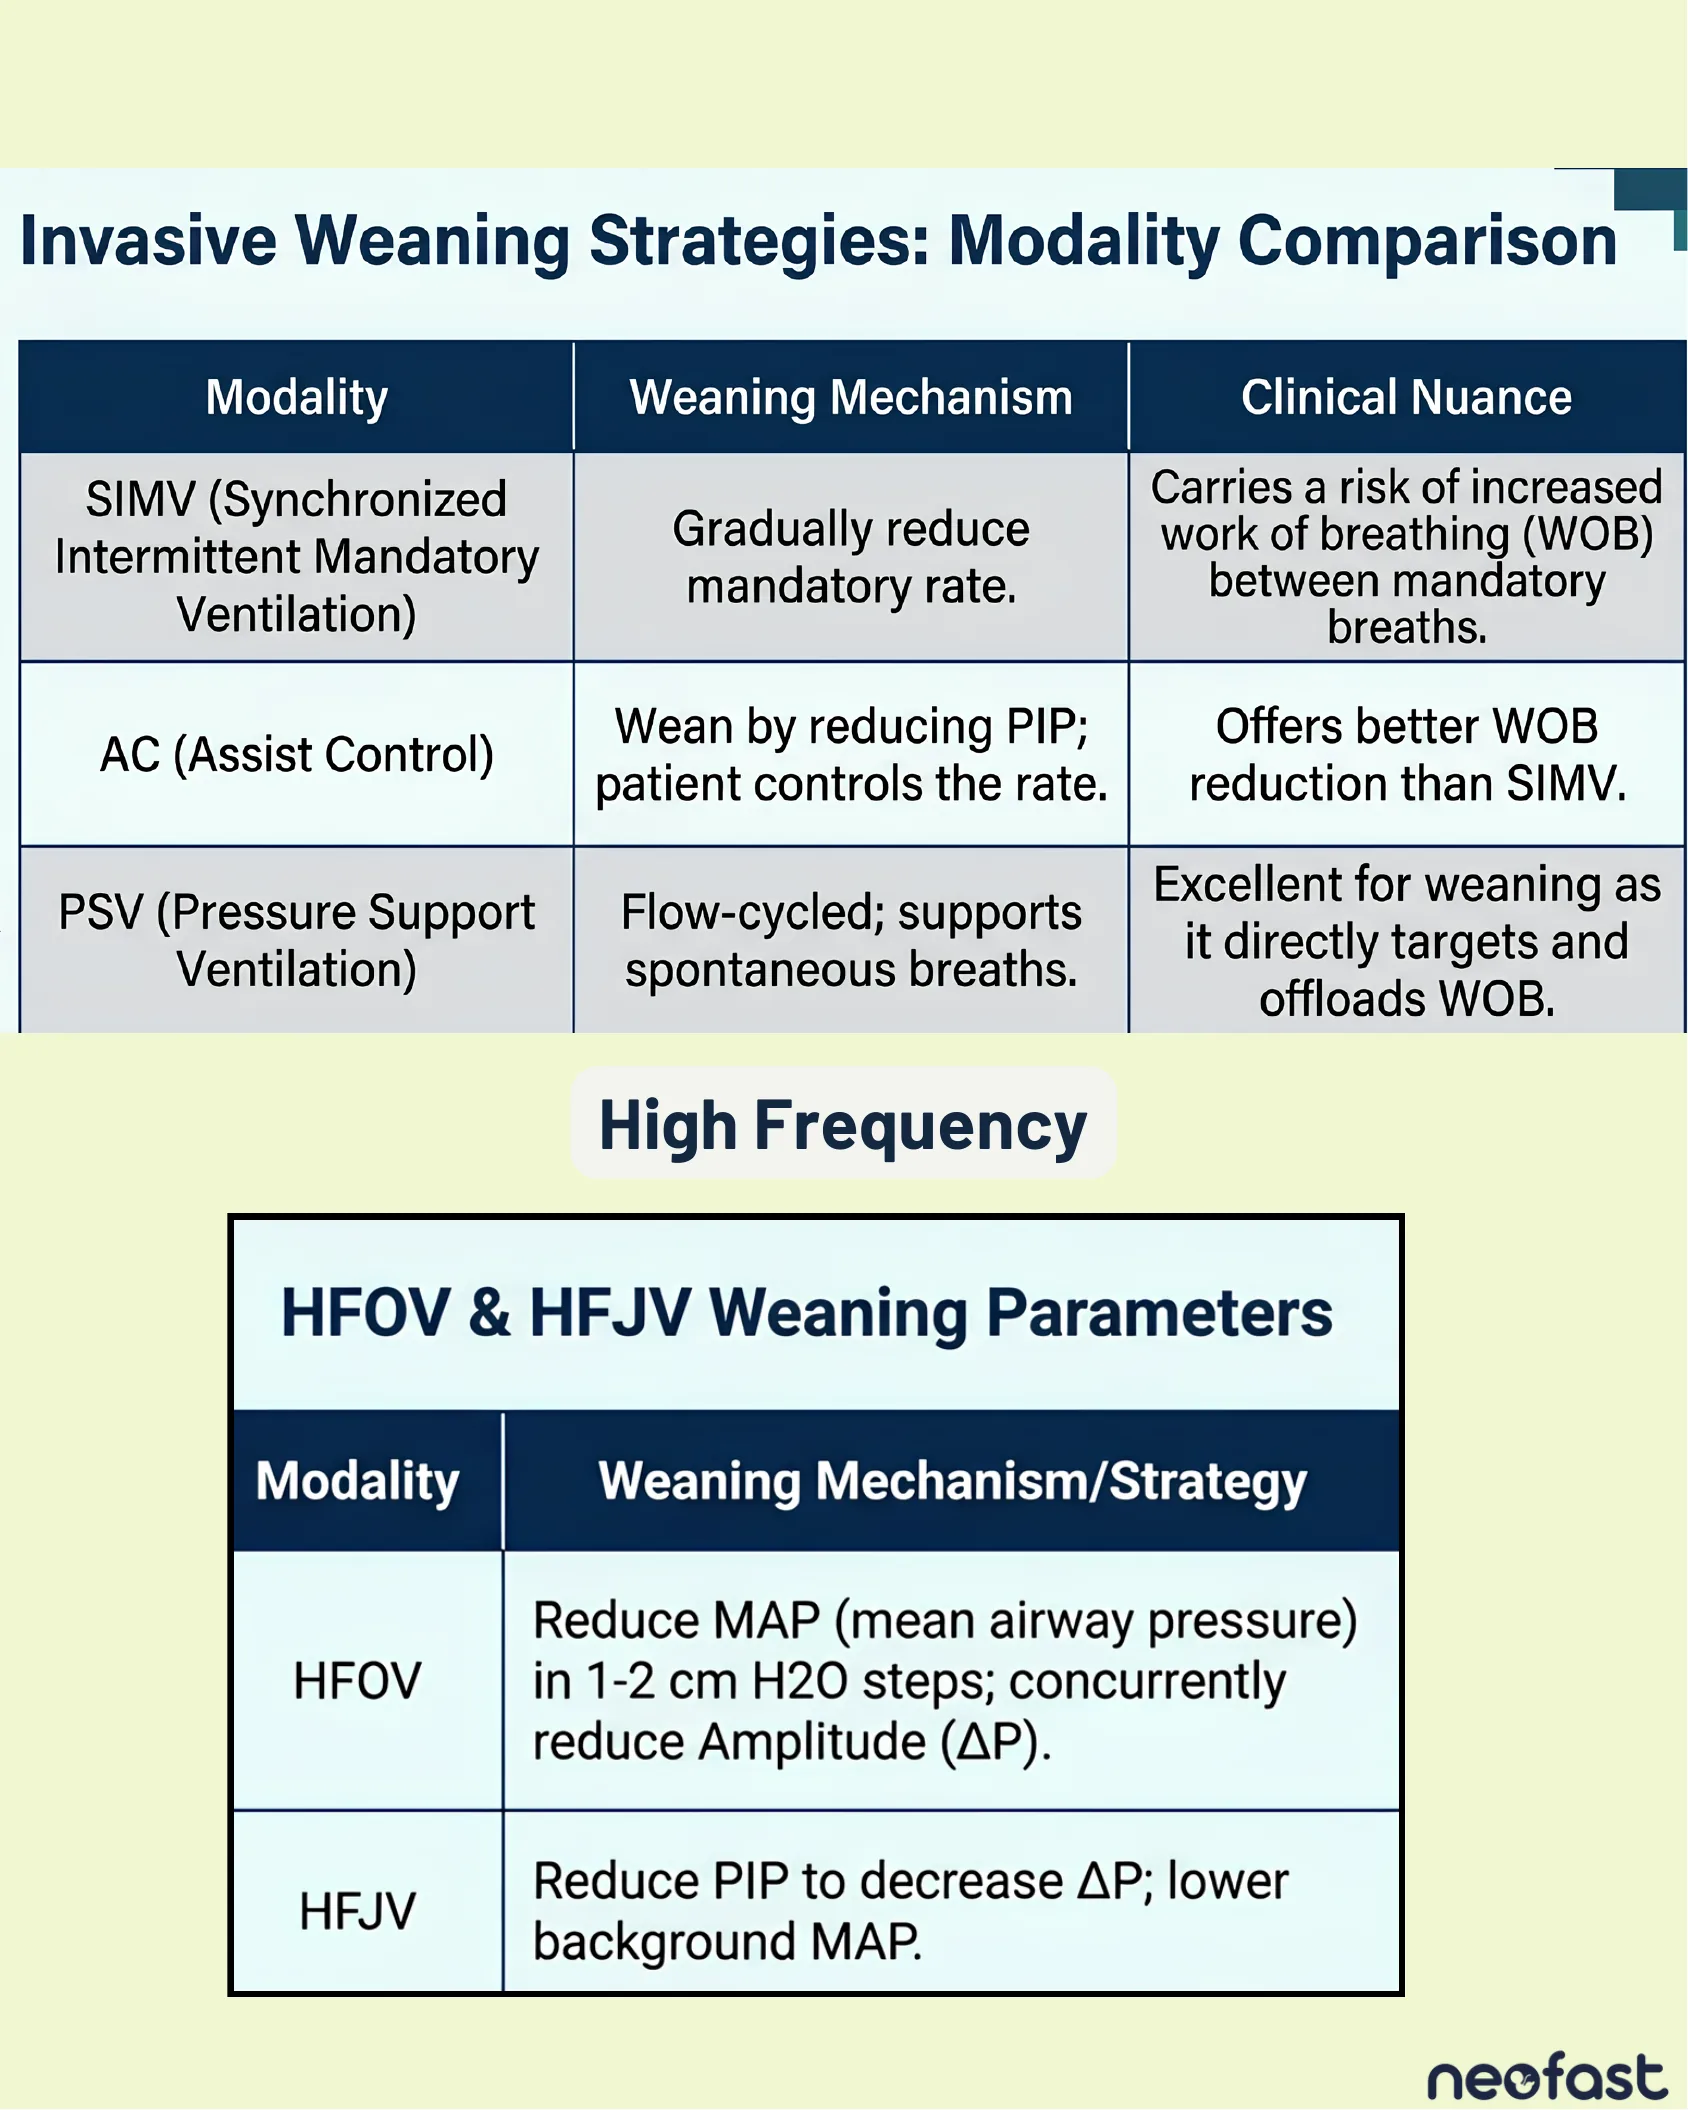
Invasive Weaning Strategies: Modality Comparison
| Modality | Weaning Mechanism | Clinical Nuance |
|---|---|---|
| SIMV (Synchronized Intermittent Mandatory Ventilation) | Gradually reduce mandatory rate. | Carries a risk of increased work of breathing (WOB) between mandatory breaths. |
| AC (Assist Control) | Wean by reducing PIP; patient controls the rate. | Offers better WOB reduction than SIMV. |
| PSV (Pressure Support Ventilation) | Flow-cycled; supports spontaneous breaths. | Excellent for weaning as it directly targets and offloads WOB. |
High Frequency
HFOV & HFJV Weaning Parameters
| Modality | Weaning Mechanism/Strategy |
|---|---|
| HFOV | Reduce MAP (mean airway pressure) in 1-2 cm H2O steps; concurrently reduce Amplitude (ΔP). |
| HFJV | Reduce PIP to decrease ΔP; lower background MAP. |
Volume Targeting
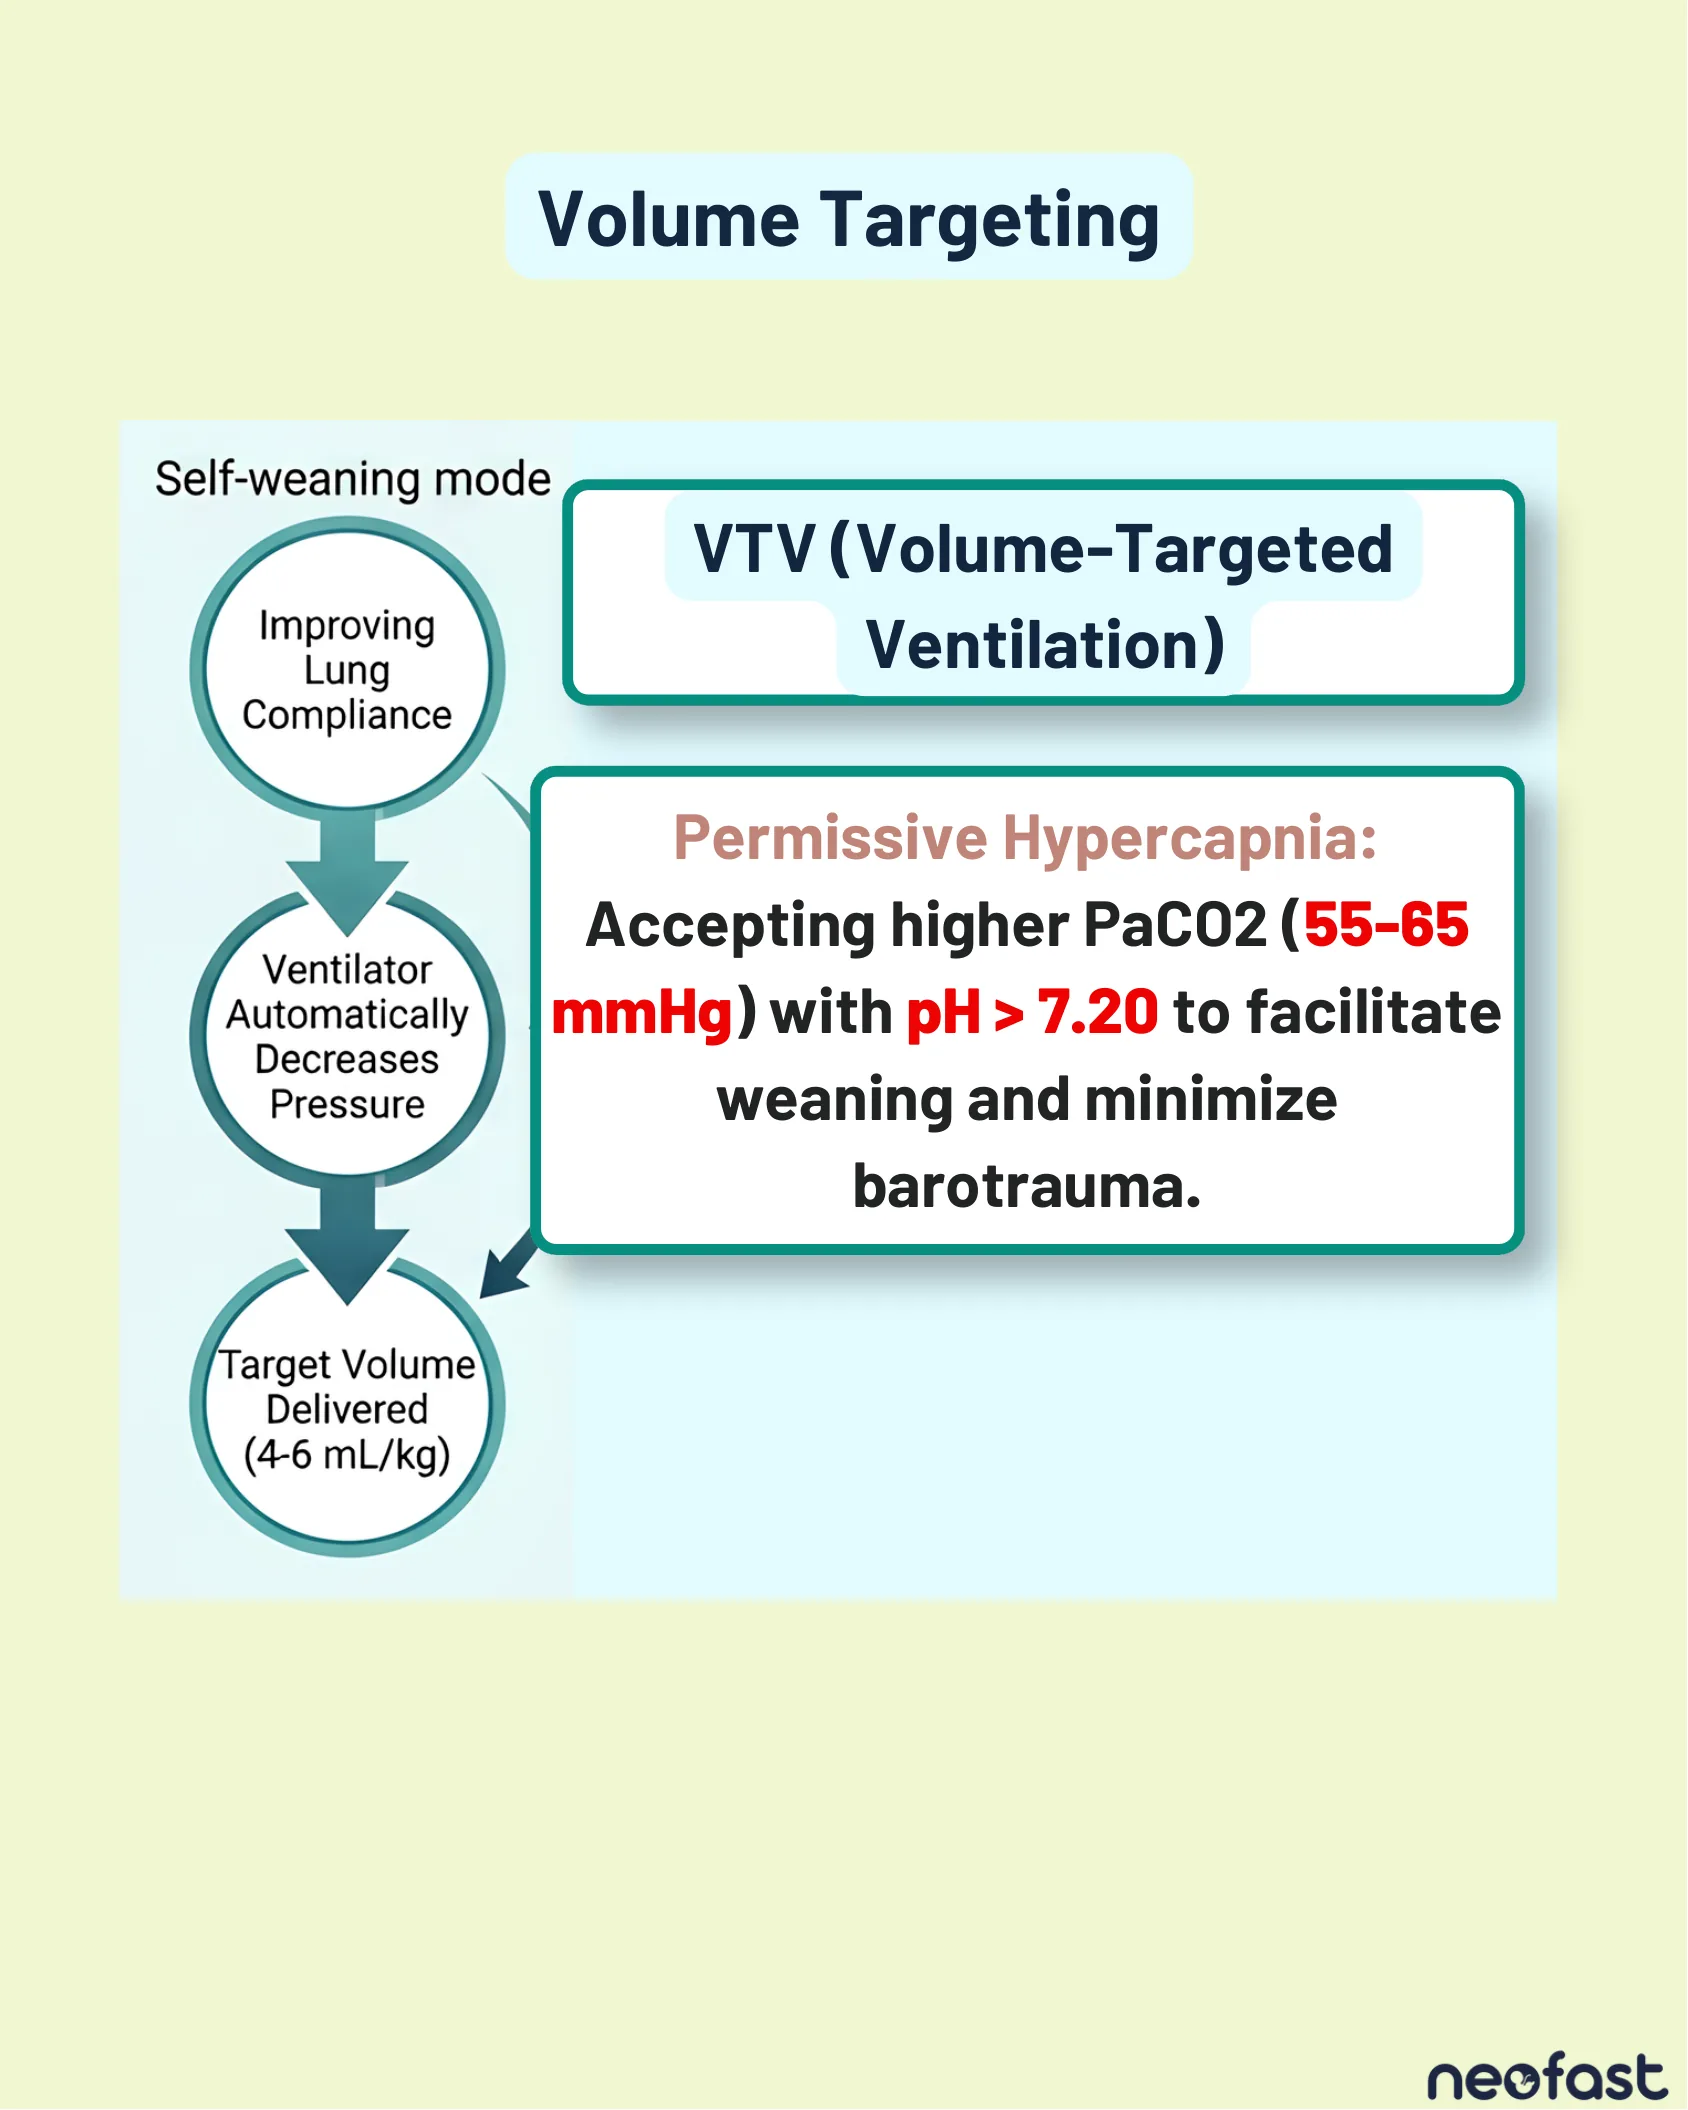
Volume Targeting
Self-weaning mode
- Improving Lung Compliance
- Ventilator Automatically Decreases Pressure
- Target Volume Delivered (4-6 mL/kg)
VTV (Volume-Targeted Ventilation)
Permissive Hypercapnia: Accepting higher PaCO2 (55-65 mmHg) with pH > 7.20 to facilitate weaning and minimize barotrauma.
The Weaning & Extubation Continuum
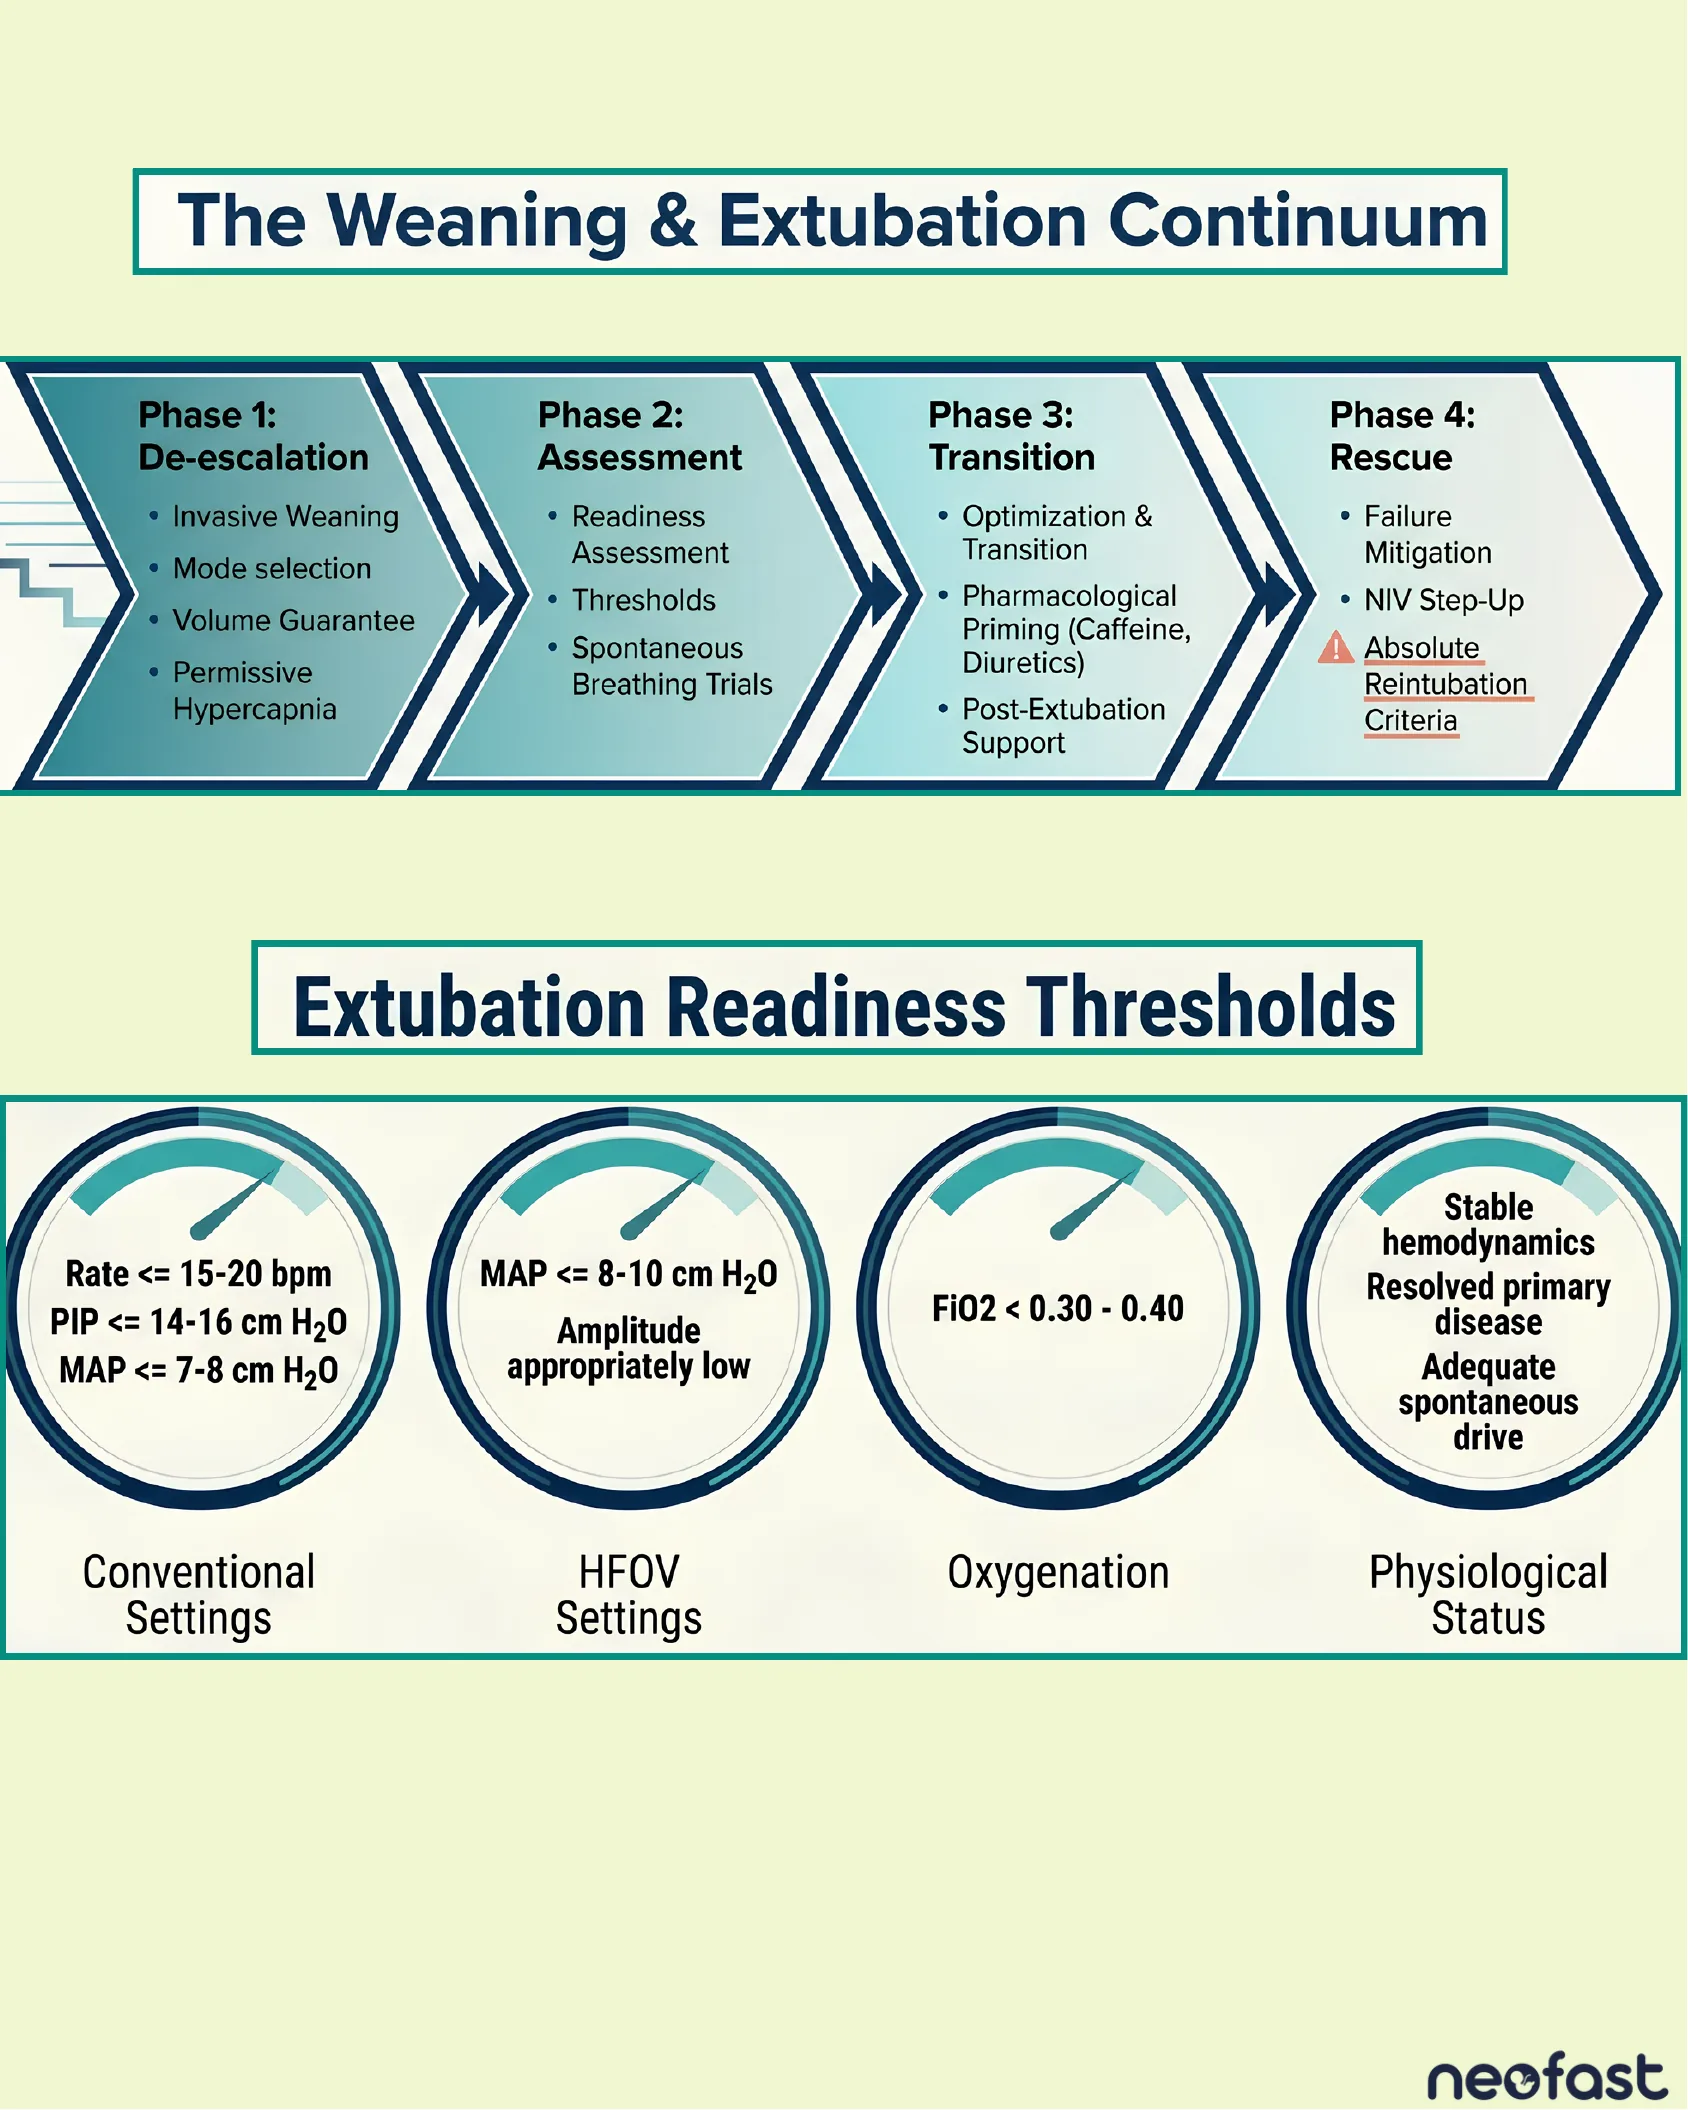
The Weaning & Extubation Continuum
- Phase 1: De-escalation
- Invasive Weaning
- Mode selection
- Volume Guarantee
- Permissive Hypercapnia
- Phase 2: Assessment
- Readiness Assessment
- Thresholds
- Spontaneous Breathing Trials
- Phase 3: Transition
- Optimization & Transition
- Pharmacological Priming (Caffeine, Diuretics)
- Post-Extubation Support
- Phase 4: Rescue
- Failure Mitigation
- NIV Step-Up
- Absolute Reintubation Criteria
Extubation Readiness Thresholds
| Conventional Settings | HFOV Settings | Oxygenation | Physiological Status |
|---|---|---|---|
| Rate <= 15-20 bpm PIP <= 14-16 cm H2O MAP <= 7-8 cm H2O | MAP <= 8-10 cm H2O Amplitude appropriately low | FiO2 < 0.30 – 0.40 | Stable hemodynamics Resolved primary disease Adequate spontaneous drive |
Extubation Readiness Trials & Caffeine Optimization

Extubation Readiness Trials (ERTs) / Spontaneous Breathing Trials (SBTs)
- Setup: Place patient on CPAP (5-7 cm H2O) via the endotracheal tube to simulate post-extubation WOB.
- 3 to 10 Minute Observation Window
- Pass (Success): Maintenance of SpO2, absence of severe bradycardia, adequate spontaneous tidal volumes. → Proceed to Extubation.
- Fail: Desaturation, bradycardia, poor effort. → Resume baseline support.
Clinical Value: A predictive tool to reduce unnecessary extubation failures. Highly valuable in complex or prolonged ventilation cases.
Pharmacological Adjuncts: Caffeine Citrate Optimization
Mechanism: Centrally acting respiratory stimulant; increases minute ventilation, improves diaphragm contractility.
- 1. Loading Dose: 20 mg/kg
- 2. Standard Maintenance: 5 – 10 mg/kg/day
- 3. High Maintenance: 10 – 20 mg/kg/day (Utilized for frequent apnea or difficult weaning, guided by clinical response)
Administer loading dose well prior to planned extubation to ensure peak serum concentrations.
Caffeine Citrate Dosing Tool – Setup
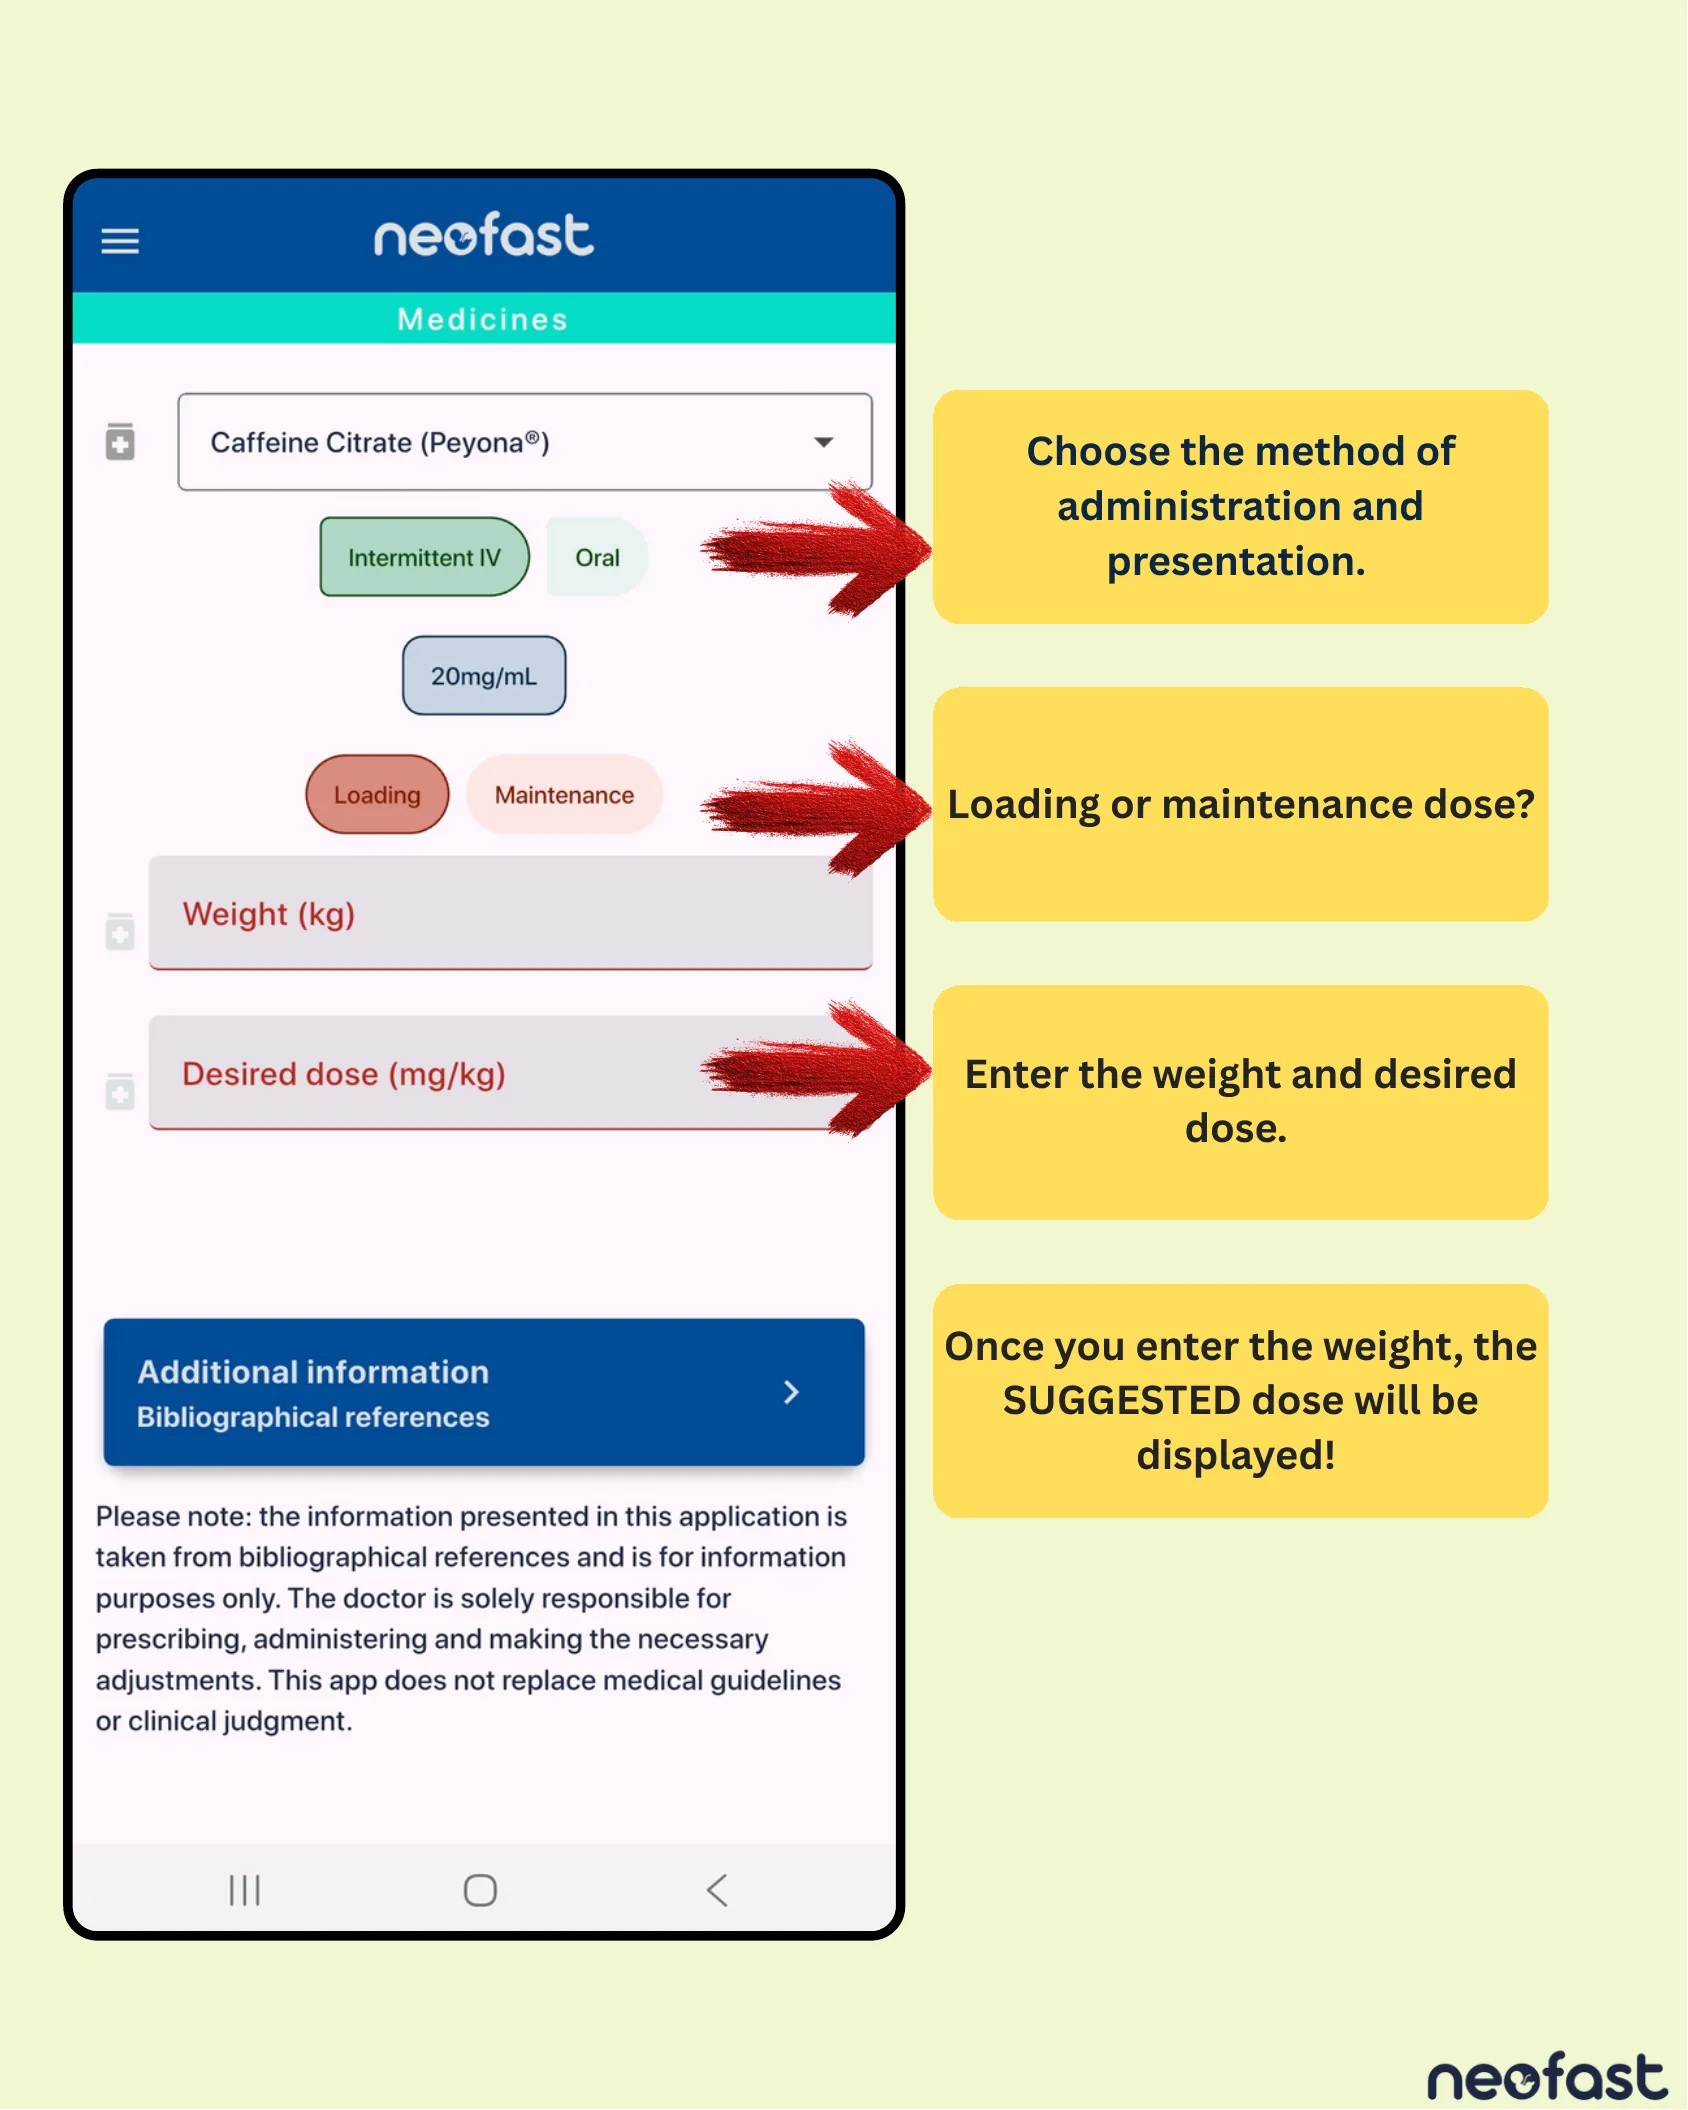
Caffeine Citrate (Peyona®) Dosing Tool
- Choose the method of administration and presentation.
- Loading or maintenance dose?
- Enter the weight and desired dose.
- Once you enter the weight, the SUGGESTED dose will be displayed!
Options shown: Intermittent IV, Oral; concentration 20mg/mL; Loading, Maintenance; fields for Weight (kg) and Desired dose (mg/kg); link to Additional information / Bibliographical references.
Please note: the information presented in this application is taken from bibliographical references and is for information purposes only. The doctor is solely responsible for prescribing, administering and making the necessary adjustments. This app does not replace medical guidelines or clinical judgment.
Caffeine Citrate Dosing Tool – Loading vs Maintenance
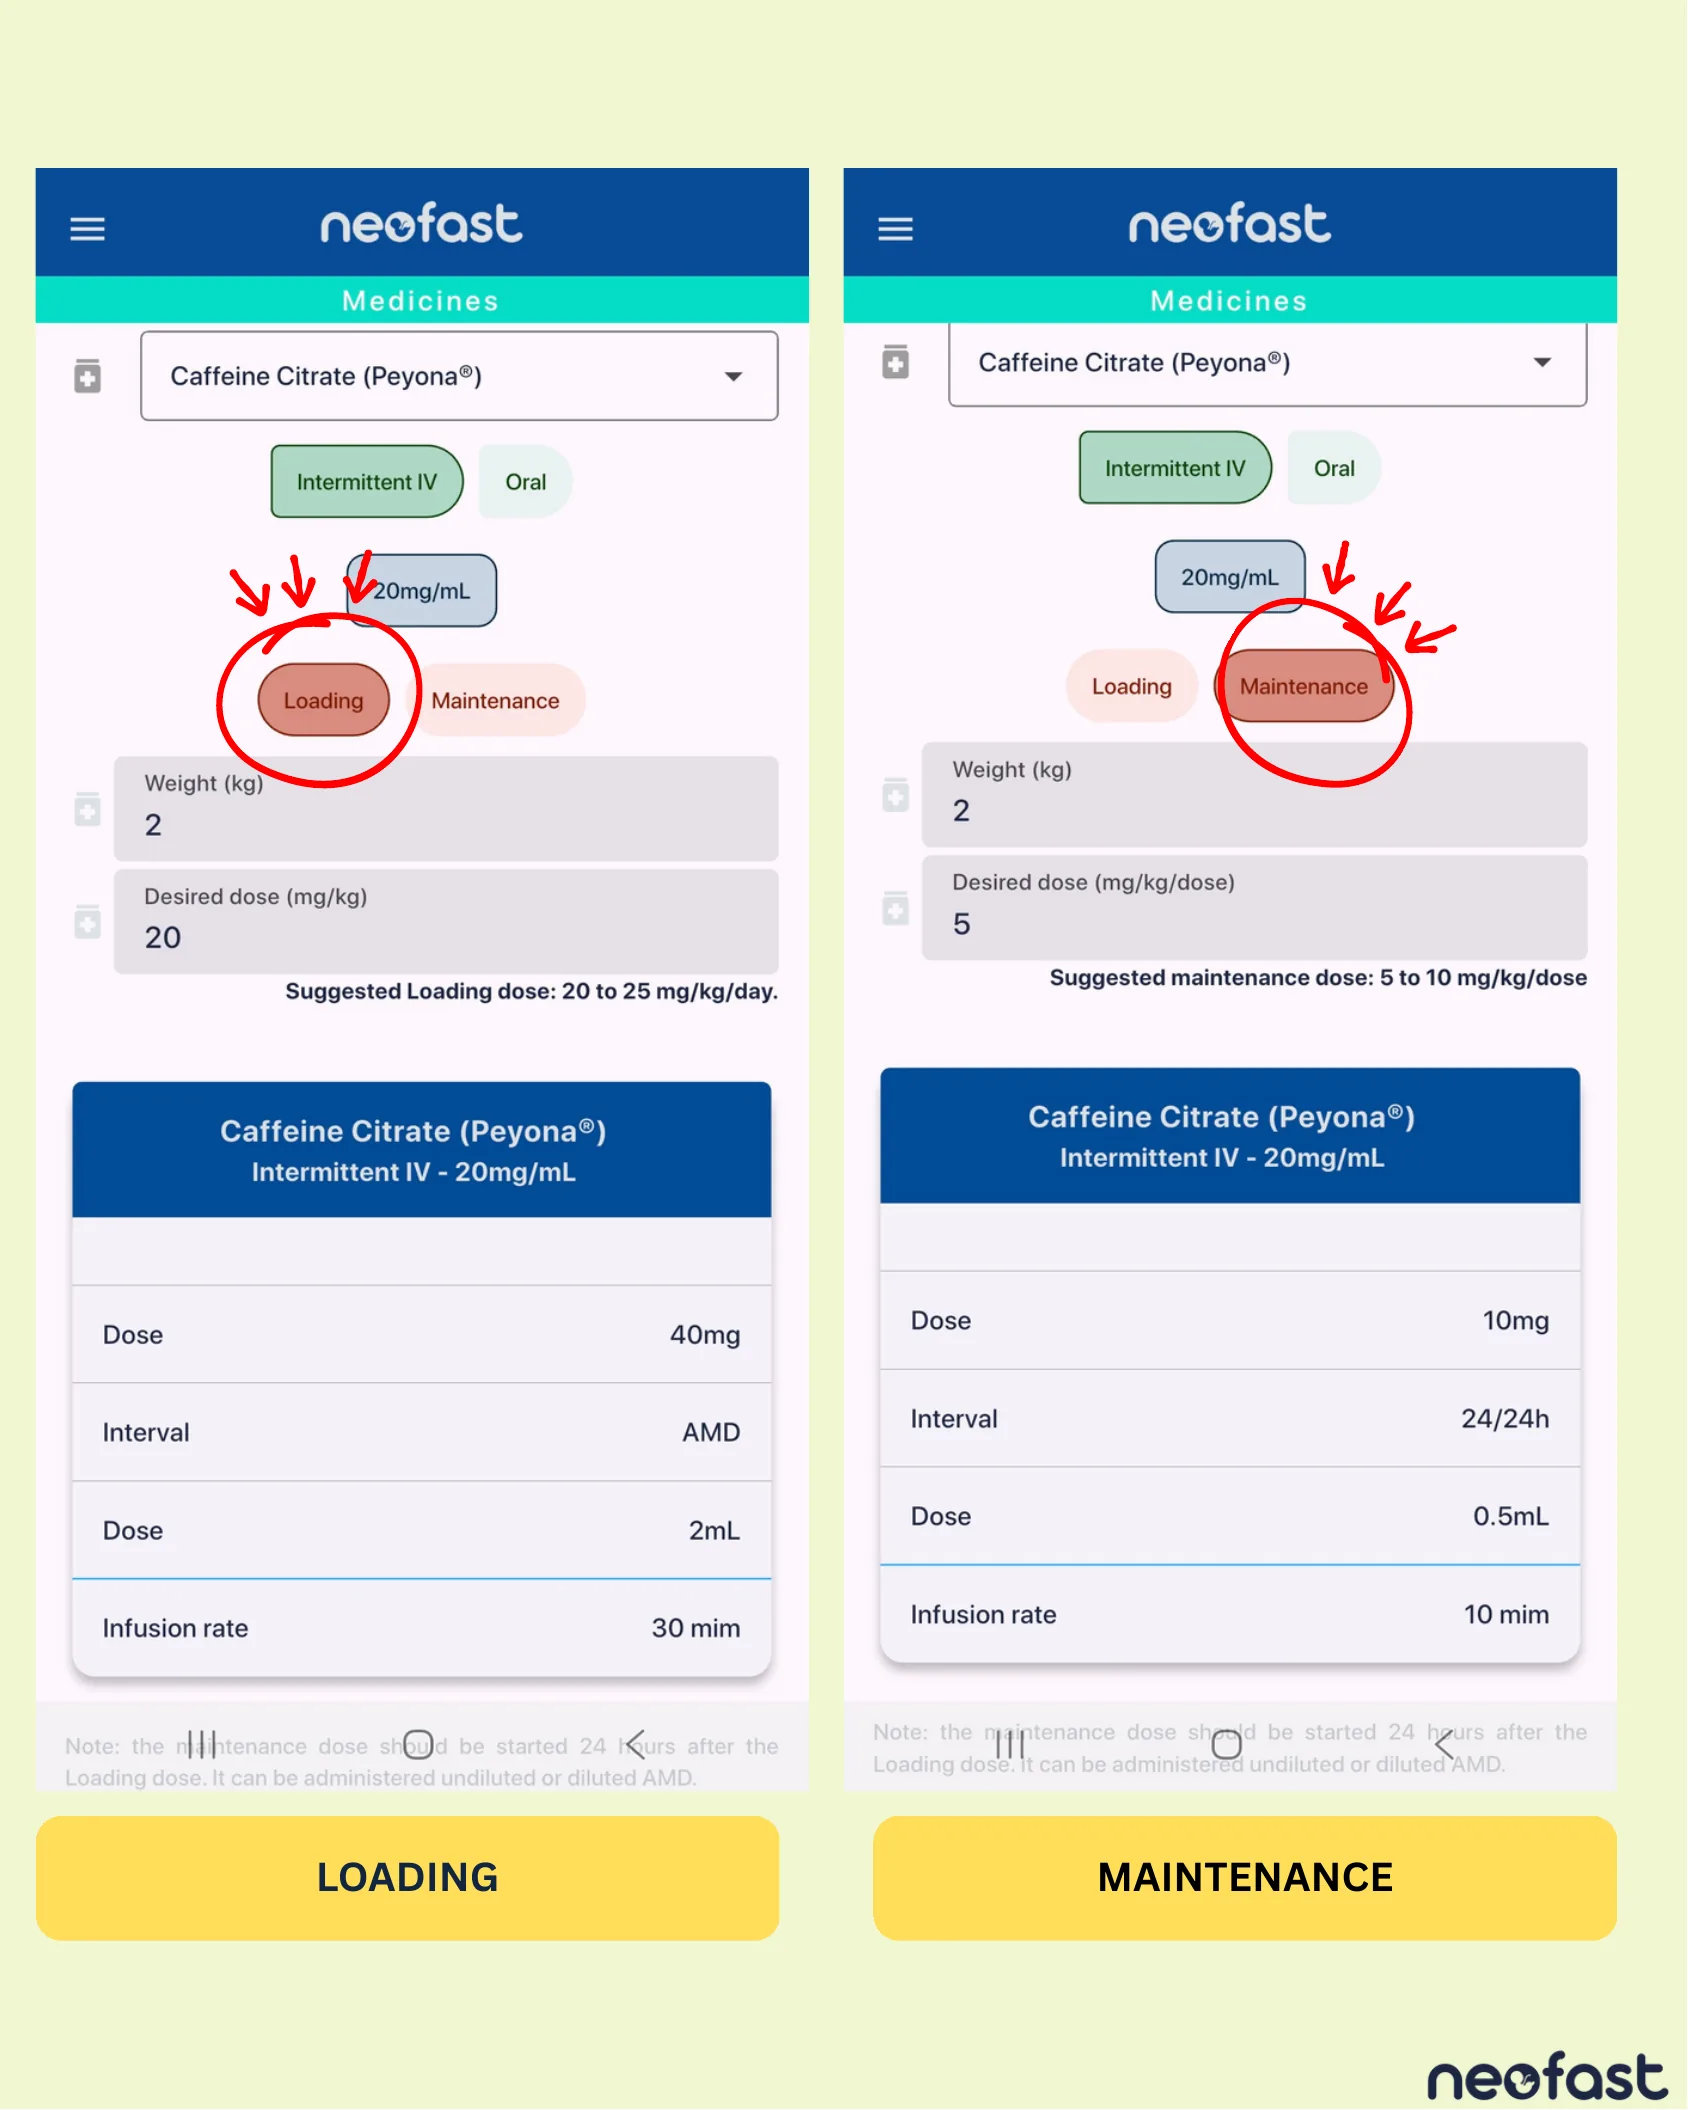
Caffeine Citrate (Peyona®) – Intermittent IV – 20mg/mL
LOADING
- Weight (kg): 2
- Desired dose (mg/kg): 20
- Suggested Loading dose: 20 to 25 mg/kg/day.
- Dose: 40mg
- Interval: AMD
- Dose: 2mL
- Infusion rate: 30 min
MAINTENANCE
- Weight (kg): 2
- Desired dose (mg/kg/dose): 5
- Suggested maintenance dose: 5 to 10 mg/kg/dose
- Dose: 10mg
- Interval: 24/24h
- Dose: 0.5mL
- Infusion rate: 10 min
Note: the maintenance dose should be started 24 hours after the Loading dose. It can be administered undiluted or diluted AMD.
Diuretics and Post-Extubation Non-Invasive Support
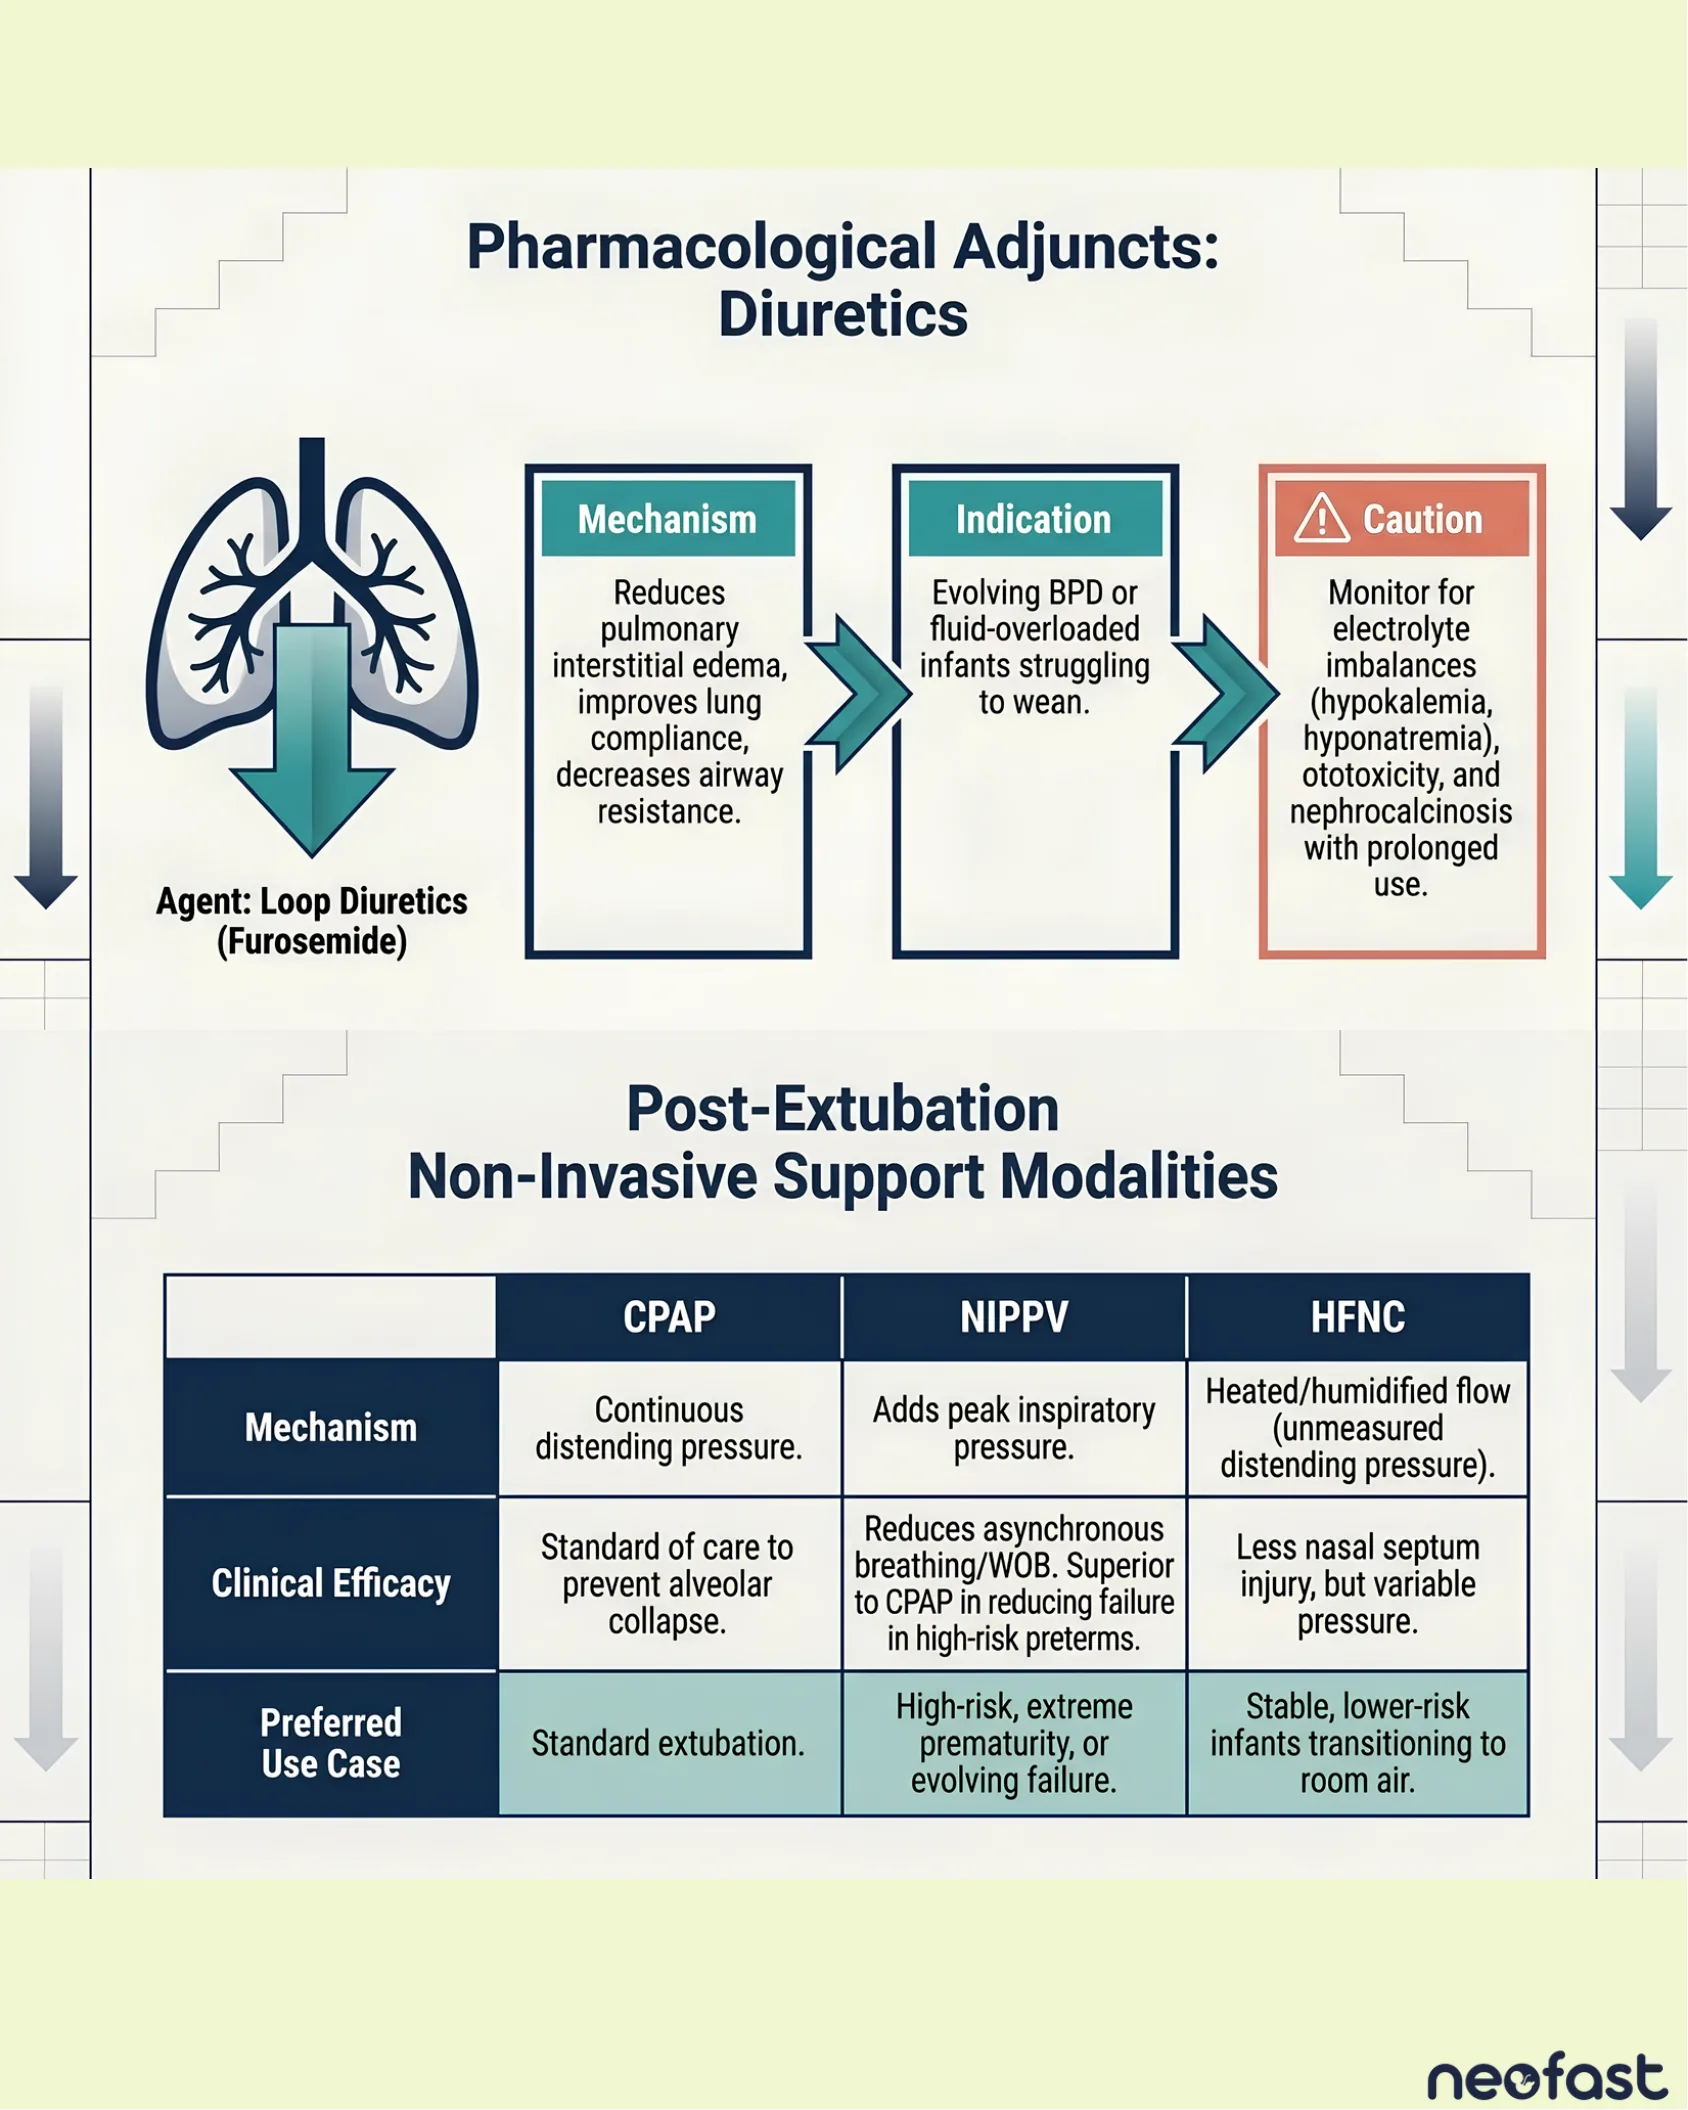
Pharmacological Adjuncts: Diuretics
Agent: Loop Diuretics (Furosemide)
- Mechanism: Reduces pulmonary interstitial edema, improves lung compliance, decreases airway resistance.
- Indication: Evolving BPD or fluid-overloaded infants struggling to wean.
- Caution: Monitor for electrolyte imbalances (hypokalemia, hyponatremia), ototoxicity, and nephrocalcinosis with prolonged use.
Post-Extubation Non-Invasive Support Modalities
| CPAP | NIPPV | HFNC | |
|---|---|---|---|
| Mechanism | Continuous distending pressure. | Adds peak inspiratory pressure. | Heated/humidified flow (unmeasured distending pressure). |
| Clinical Efficacy | Standard of care to prevent alveolar collapse. | Reduces asynchronous breathing/WOB. Superior to CPAP in reducing failure in high-risk preterms. | Less nasal septum injury, but variable pressure. |
| Preferred Use Case | Standard extubation. | High-risk, extreme prematurity, or evolving failure. | Stable, lower-risk infants transitioning to room air. |
Risk Factors & Causes of Extubation Failure
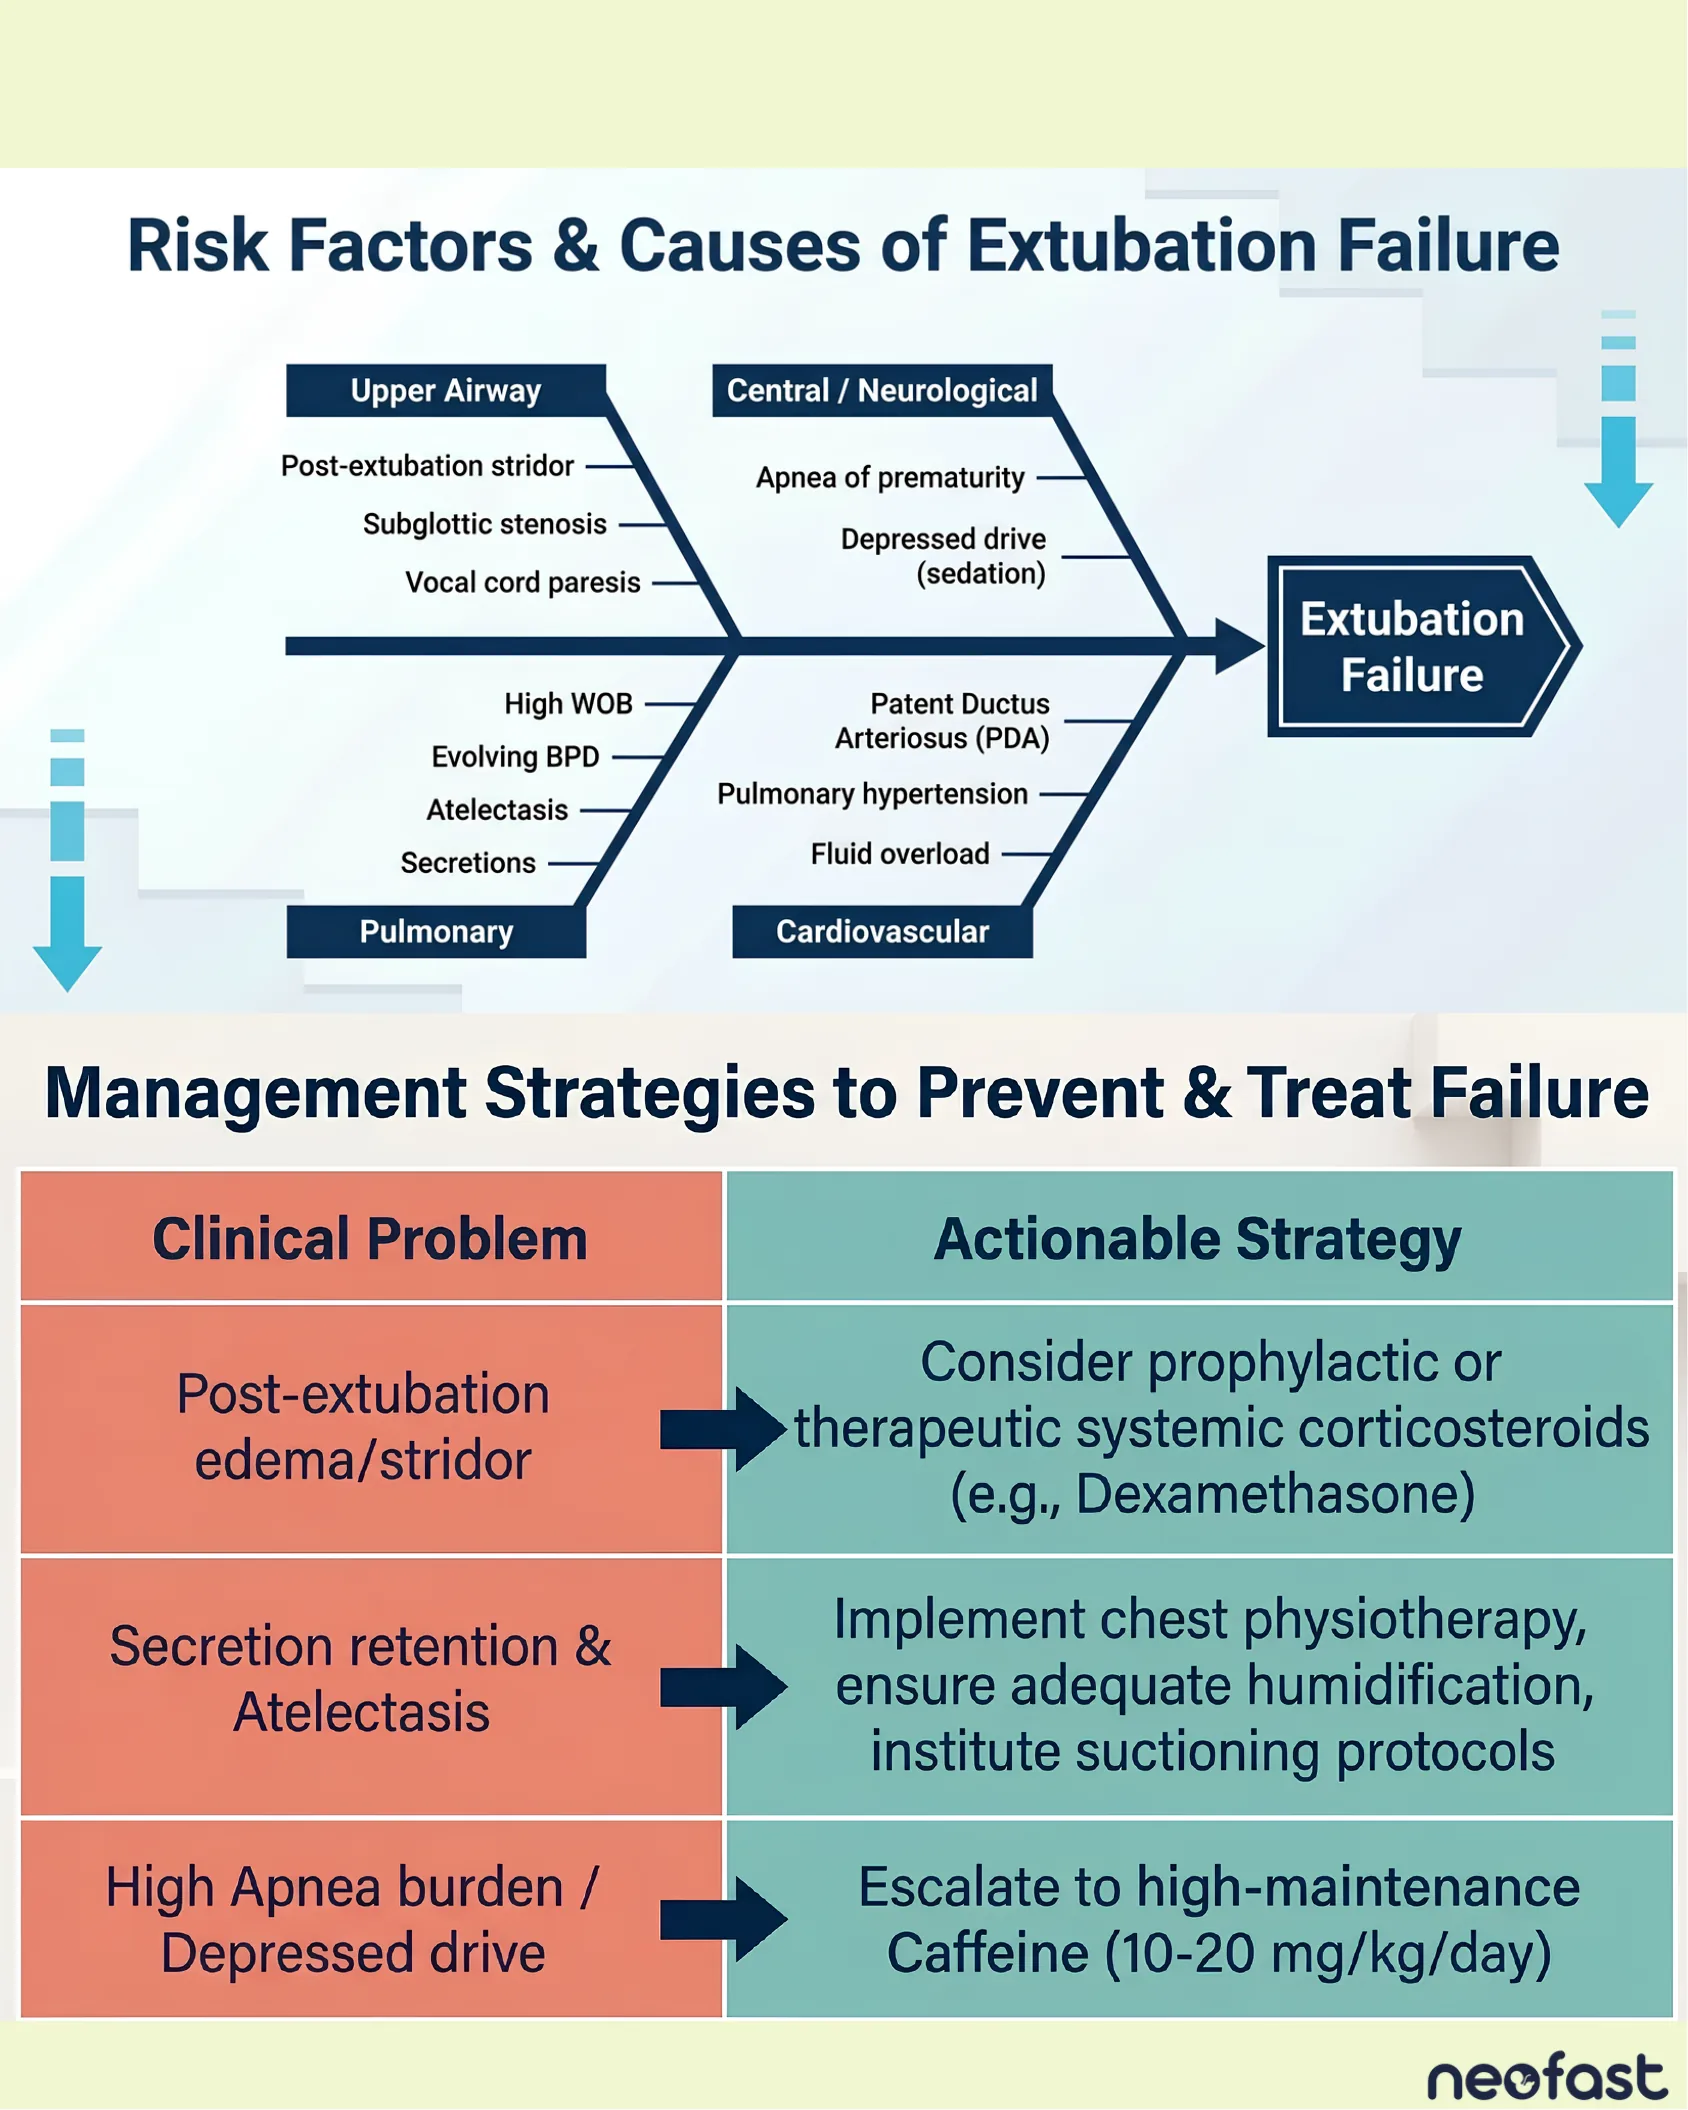
Risk Factors & Causes of Extubation Failure
- Upper Airway
- Post-extubation stridor
- Subglottic stenosis
- Vocal cord paresis
- Central / Neurological
- Apnea of prematurity
- Depressed drive (sedation)
- Pulmonary
- High WOB
- Evolving BPD
- Atelectasis
- Secretions
- Cardiovascular
- Patent Ductus Arteriosus (PDA)
- Pulmonary hypertension
- Fluid overload
All factors converge toward: Extubation Failure
Management Strategies to Prevent & Treat Failure
| Clinical Problem | Actionable Strategy |
|---|---|
| Post-extubation edema/stridor | Consider prophylactic or therapeutic systemic corticosteroids (e.g., Dexamethasone) |
| Secretion retention & Atelectasis | Implement chest physiotherapy, ensure adequate humidification, institute suctioning protocols |
| High Apnea burden / Depressed drive | Escalate to high-maintenance Caffeine (10-20 mg/kg/day) |
Post-Extubation Failure: Step-Wise Escalation
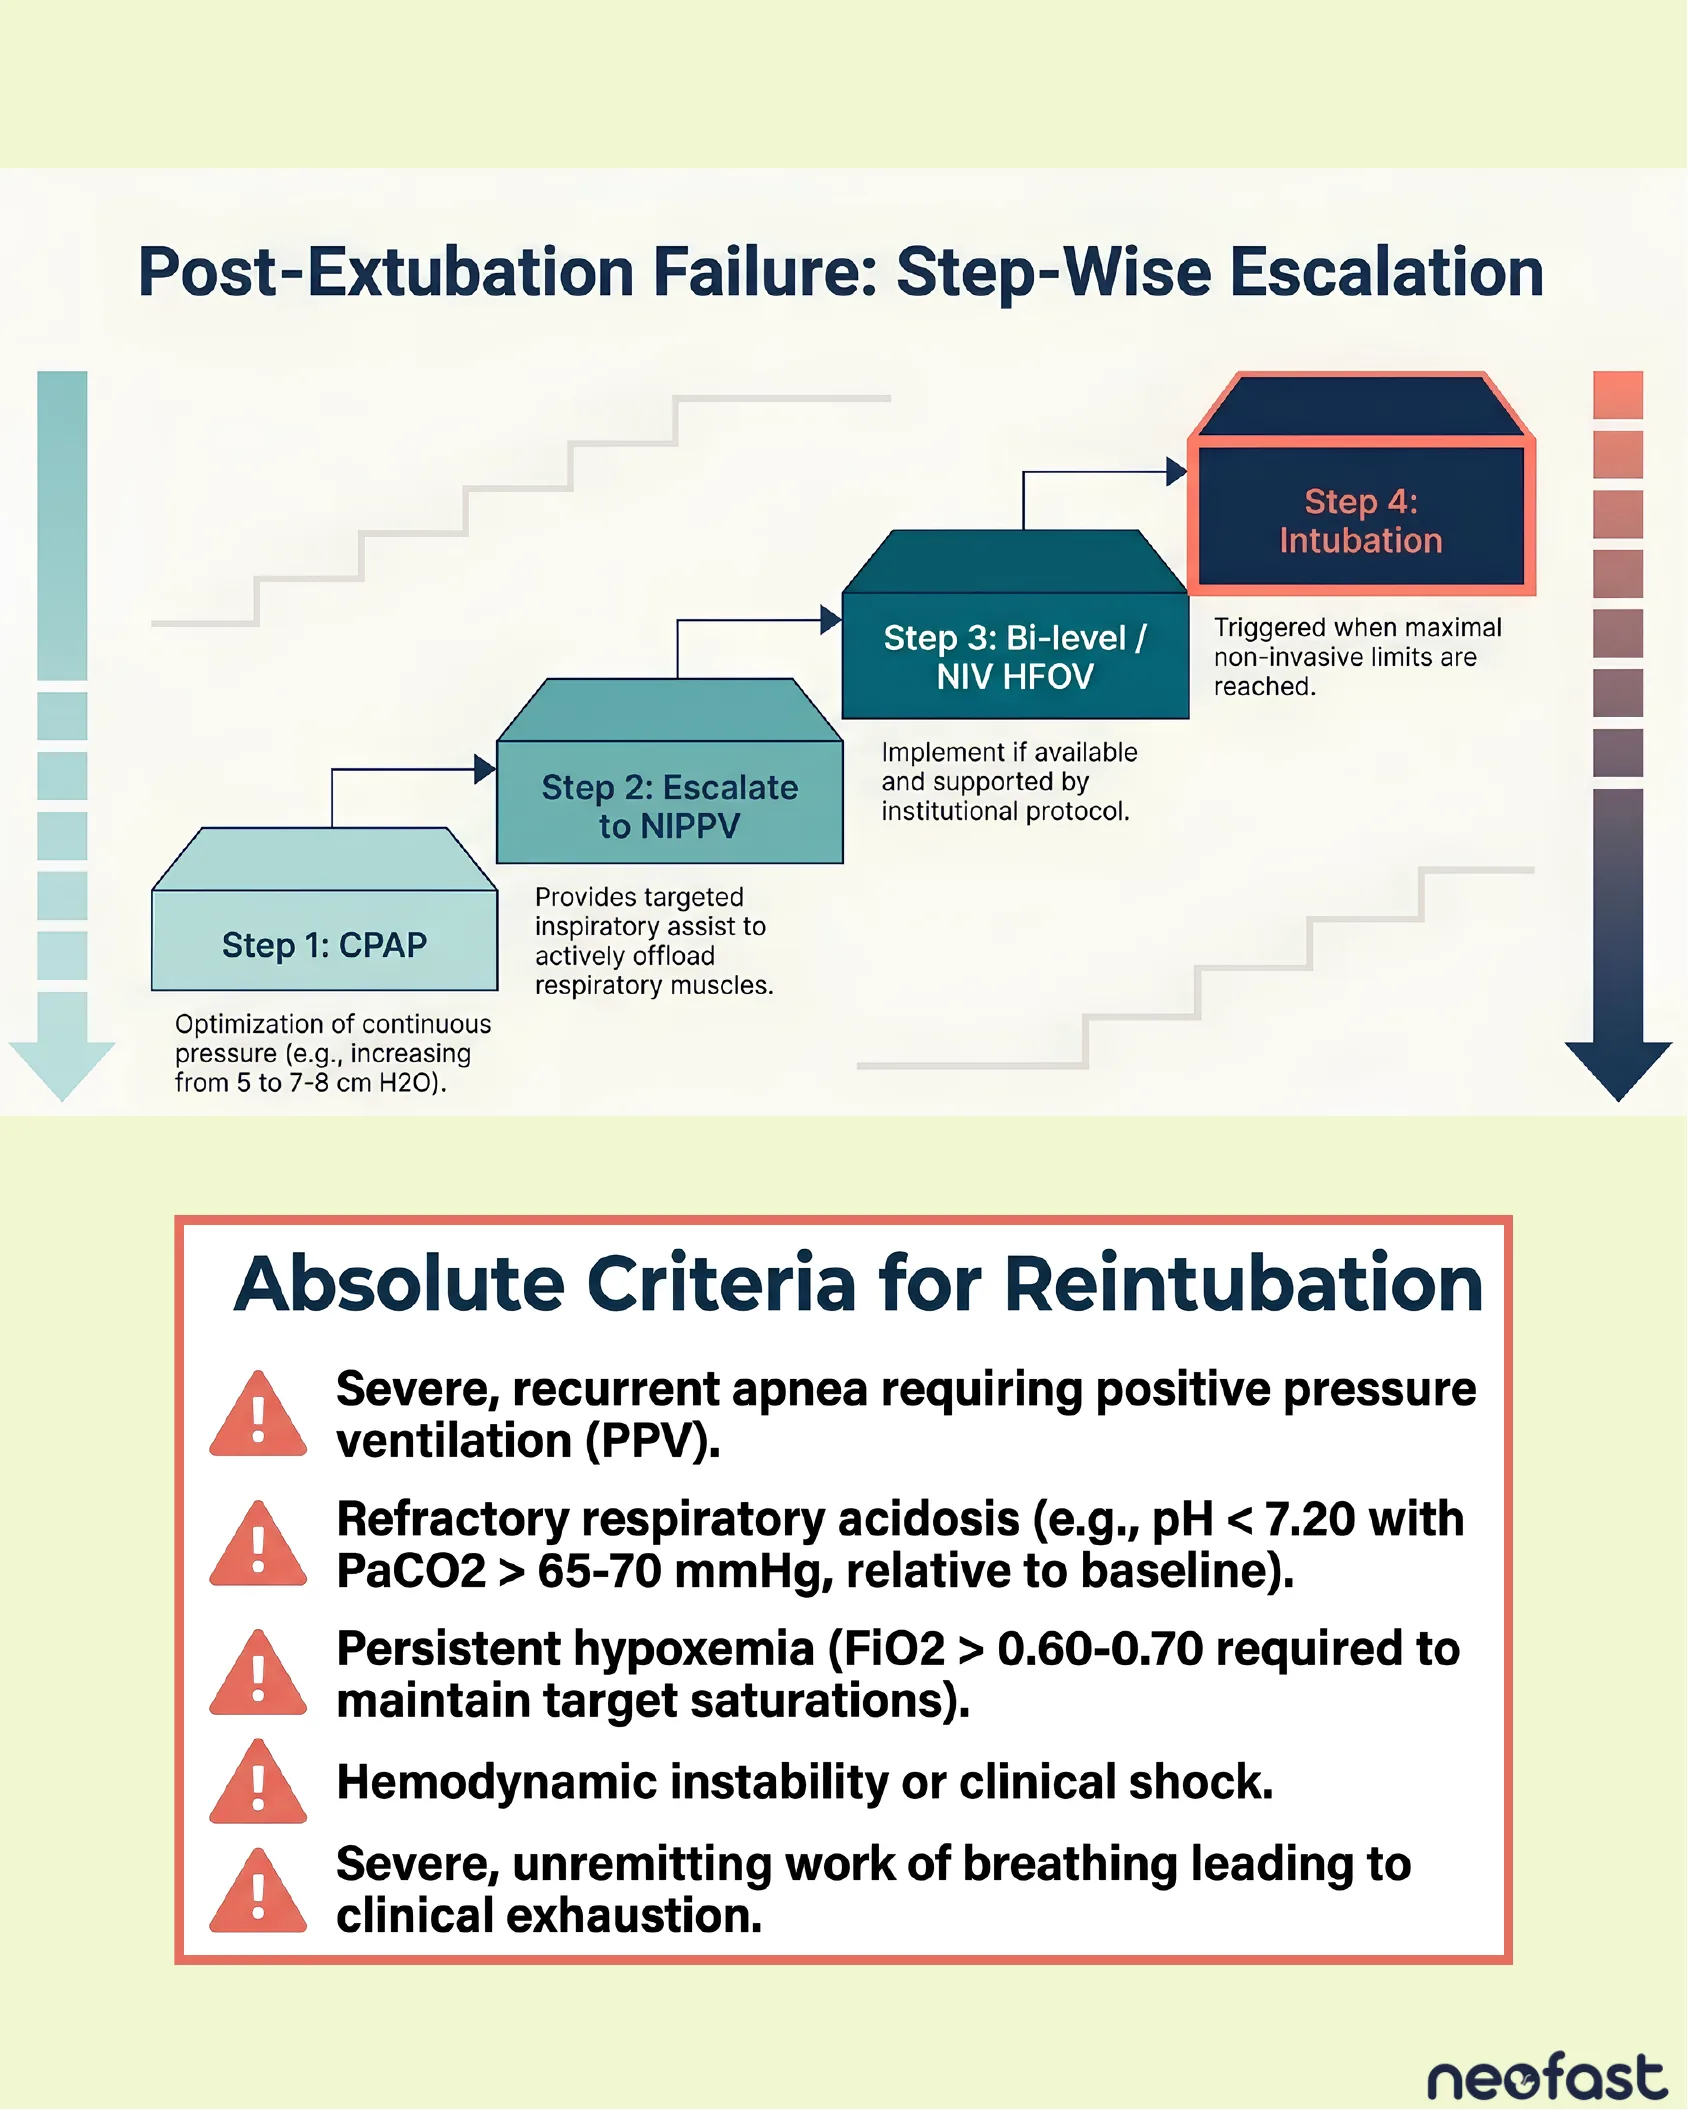
Post-Extubation Failure: Step-Wise Escalation
- Step 1: CPAP — Optimization of continuous pressure (e.g., increasing from 5 to 7-8 cm H2O).
- Step 2: Escalate to NIPPV — Provides targeted inspiratory assist to actively offload respiratory muscles.
- Step 3: Bi-level / NIV HFOV — Implement if available and supported by institutional protocol.
- Step 4: Intubation — Triggered when maximal non-invasive limits are reached.
Absolute Criteria for Reintubation
- Severe, recurrent apnea requiring positive pressure ventilation (PPV).
- Refractory respiratory acidosis (e.g., pH < 7.20 with PaCO2 > 65-70 mmHg, relative to baseline).
- Persistent hypoxemia (FiO2 > 0.60-0.70 required to maintain target saturations).
- Hemodynamic instability or clinical shock.
- Severe, unremitting work of breathing leading to clinical exhaustion.
The Protocolized Approach to Weaning
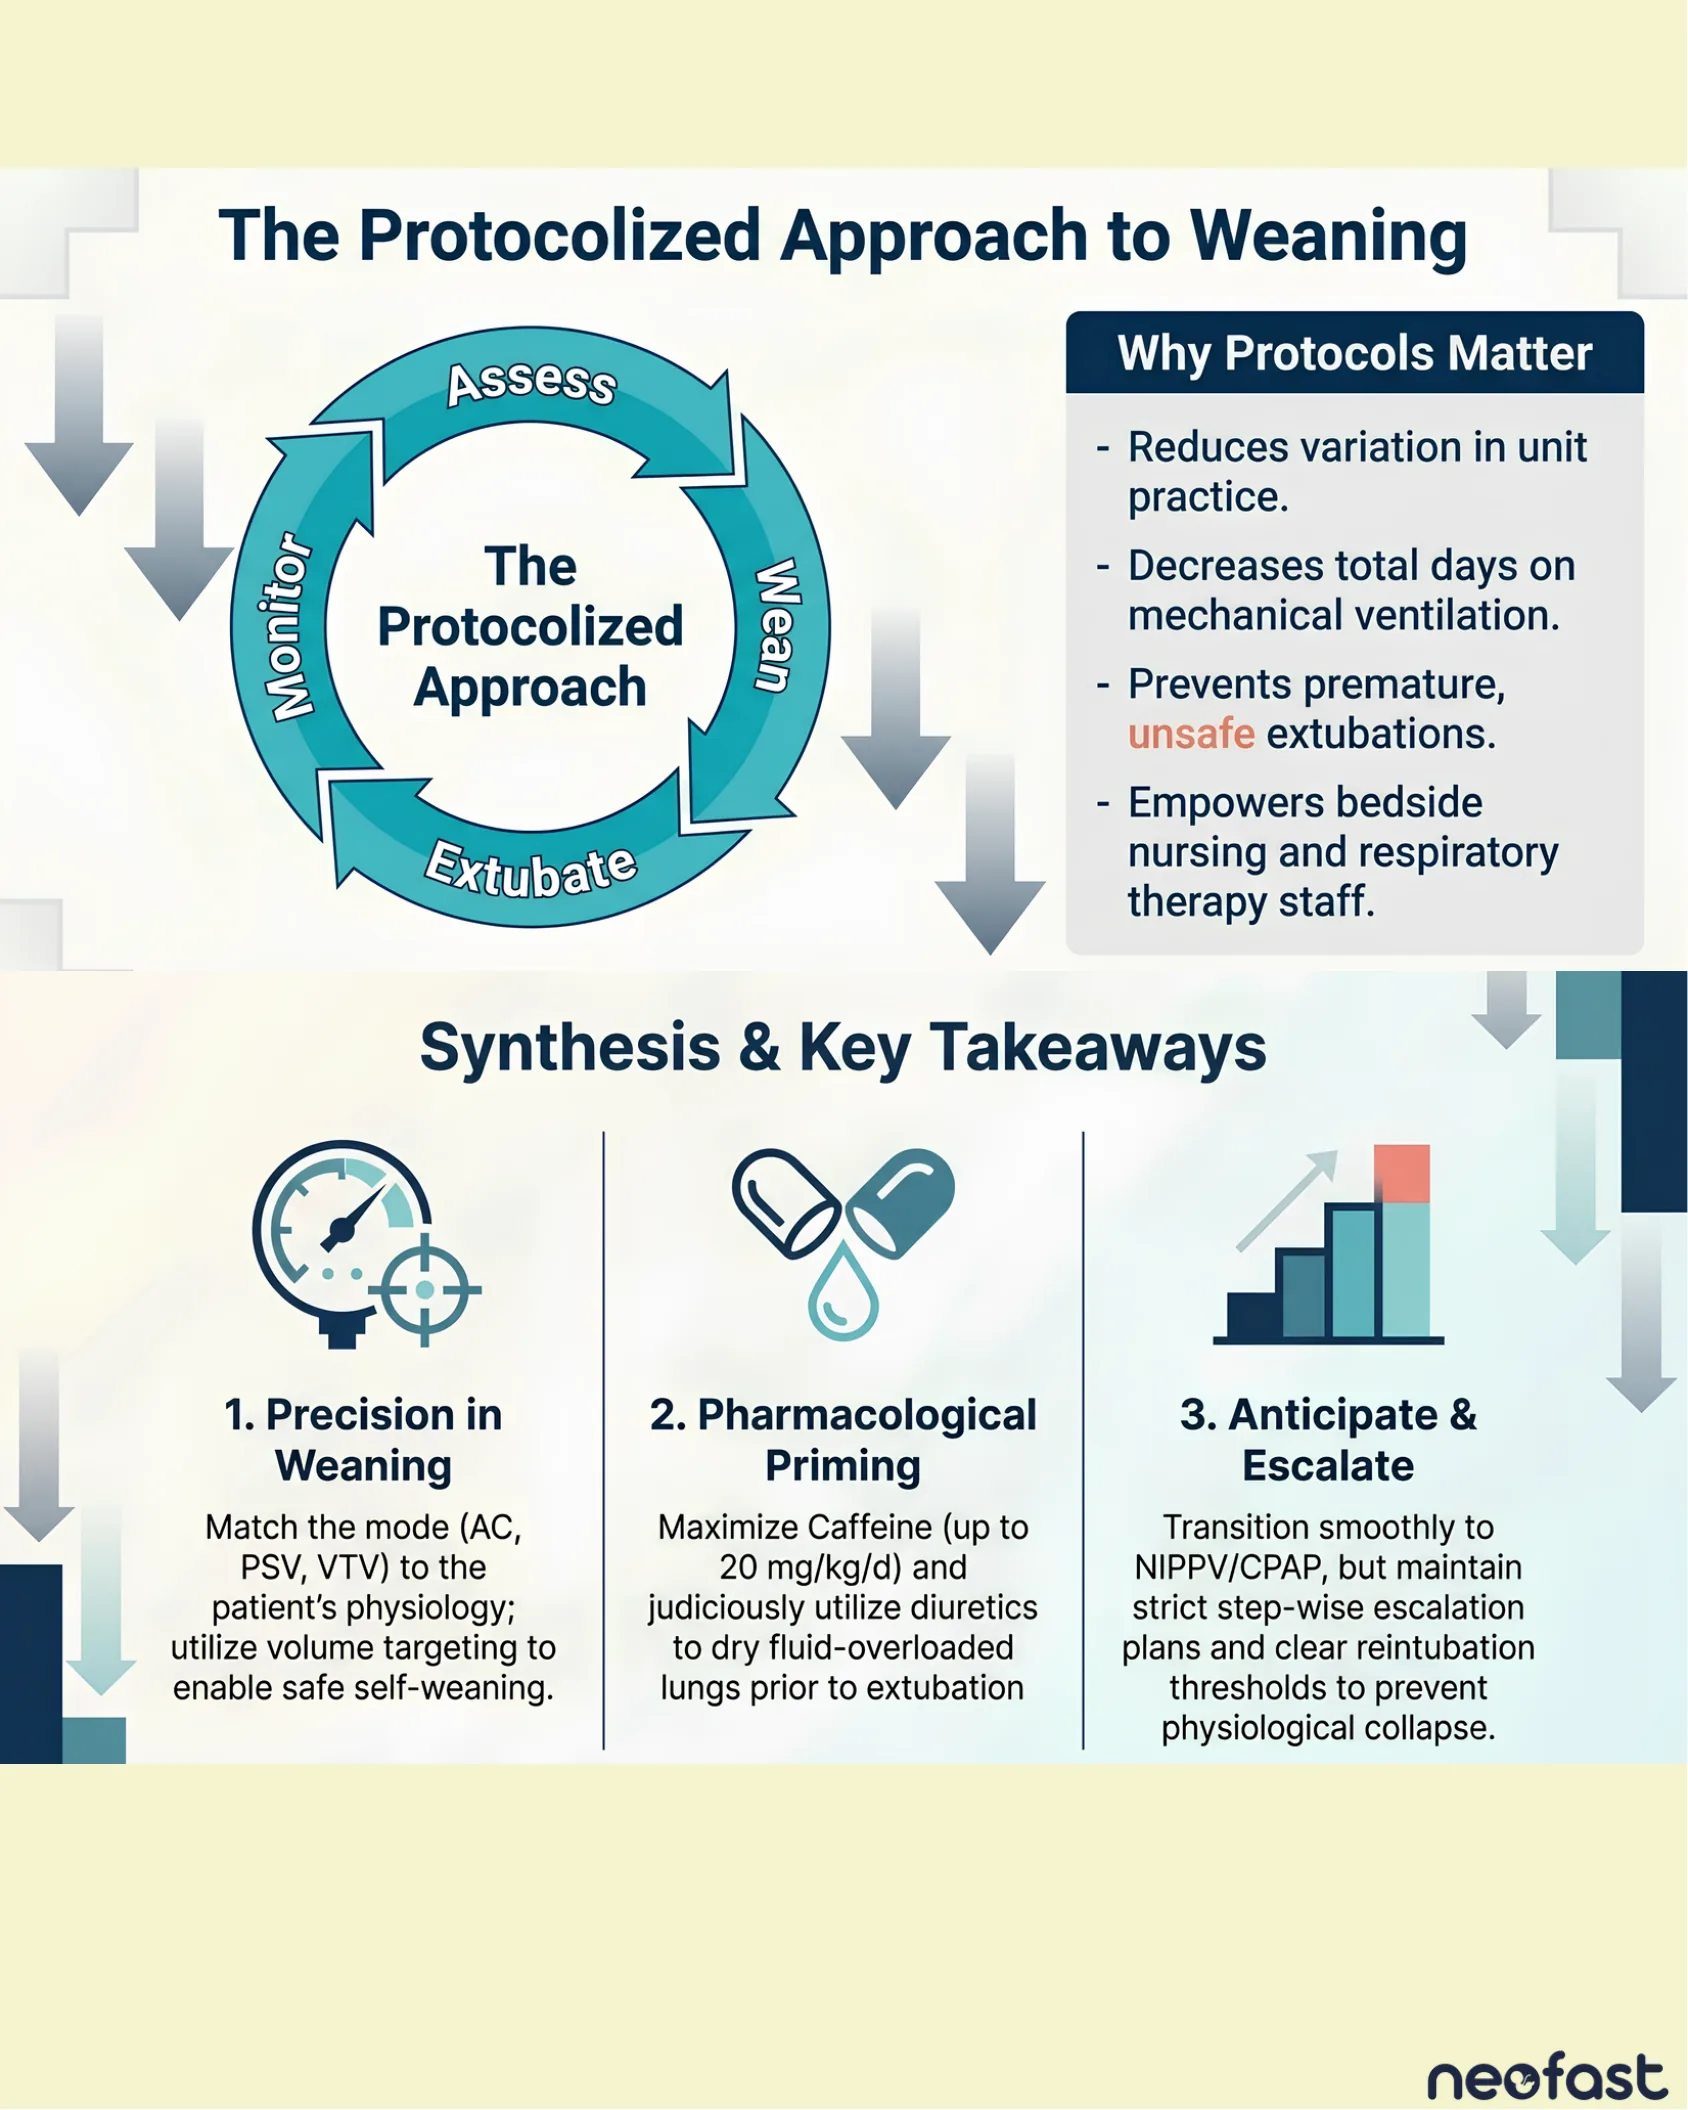
The Protocolized Approach to Weaning
- Assess
- Wean
- Extubate
- Monitor
Why Protocols Matter
- Reduces variation in unit practice.
- Decreases total days on mechanical ventilation.
- Prevents premature, unsafe extubations.
- Empowers bedside nursing and respiratory therapy staff.
Synthesis & Key Takeaways
- 1. Precision in Weaning — Match the mode (AC, PSV, VTV) to the patient’s physiology; utilize volume targeting to enable safe self-weaning.
- 2. Pharmacological Priming — Maximize Caffeine (up to 20 mg/kg/d) and judiciously utilize diuretics to dry fluid-overloaded lungs prior to extubation.
- 3. Anticipate & Escalate — Transition smoothly to NIPPV/CPAP, but maintain strict step-wise escalation plans and clear reintubation thresholds to prevent physiological collapse.
Neofast App
neofast
- Venous hydration
- Continuous medication
- Medicines
- Intubation
- Other calculations and scores
- Procedures
- Respiratory and hemodynamic monitoring
- Growth and Development
- Intuitive
- Fast
- Easy
- Smart
Download on the App Store
Get it on Google Play
Frequently asked questions
What are the extubation readiness thresholds for conventional ventilation?
Rate ≤15-20 bpm, PIP ≤14-16 cm H2O, MAP ≤7-8 cm H2O, with FiO2 <0.30-0.40, stable hemodynamics, resolved primary disease, and adequate spontaneous drive.
What is the caffeine citrate dosing protocol for extubation?
Loading dose is 20 mg/kg, standard maintenance is 5-10 mg/kg/day, and high maintenance is 10-20 mg/kg/day for frequent apnea or difficult weaning, guided by clinical response. The loading dose should be given well prior to planned extubation to ensure peak serum concentrations.
How is an Extubation Readiness Trial (ERT) performed?
The patient is placed on CPAP (5-7 cm H2O) via the endotracheal tube to simulate post-extubation work of breathing, observed for 3 to 10 minutes. Pass criteria include maintained SpO2, absence of severe bradycardia, and adequate spontaneous tidal volumes; failure shows desaturation, bradycardia, or poor effort.
What level of PaCO2 is acceptable under permissive hypercapnia during weaning?
PaCO2 of 55-65 mmHg is accepted, provided pH remains >7.20, to facilitate weaning and minimize barotrauma.
What are the absolute criteria for reintubation after extubation failure?
Severe recurrent apnea requiring PPV, refractory respiratory acidosis (pH decline with PaCO2 65-70 mmHg relative to baseline), persistent hypoxemia requiring FiO2 >0.60-0.70, hemodynamic instability or shock, and severe unremitting work of breathing leading to clinical exhaustion.

