


Key takeaways
- RDS targets VT 4–6 mL/kg with PEEP 5–8 cmH2O, while gentle ventilation for CDH/lung hypoplasia uses smaller VT (4–5 mL/kg, PIP <26) with PaCO2 tolerated up to 65 mmHg.
- In MAS, keep rate below 30/min on SIMV (or 240–360/min on HFJV) to allow a long expiratory time and avoid worsening air trapping.
- Severe-chronic BPD requires larger tidal volumes (6–12 mL/kg), longer I-time (0.5–1.0 s), slower rates (15–30/min) and higher PEEP (8–12 cmH2O, up to 14 in malacia) to stent airways and allow complete exhalation.
- Oxygenation Index between 15 and 25 suggests considering inhaled nitric oxide, while an OI of 40 or higher is an indication for ECMO.
- With standardized extubation protocols, about 90% of infants meeting criteria are extubated within 24 hours, and the authors’ QI program achieved a 40% reduction in ventilator days.
References
- Yoder BA, Grubb PH. Mechanical Ventilation: Disease-Specific Strategies. In: Keszler M, Gautham KS, eds. Goldsmith’s Assisted Ventilation of the Neonate: An Evidence-Based Approach to Newborn Respiratory Care. 7th ed. Philadelphia: Elsevier; 2022. Chapter 25, p. 288–302.
- Yoder BA, Grubb PH. In: Keszler M, Gautham KS, eds. Goldsmith’s Assisted Ventilation of the Neonate. 7th ed. Elsevier; 2022. Ch. 25.
Goldsmith’s Neonatal Mechanical Ventilation Strategies
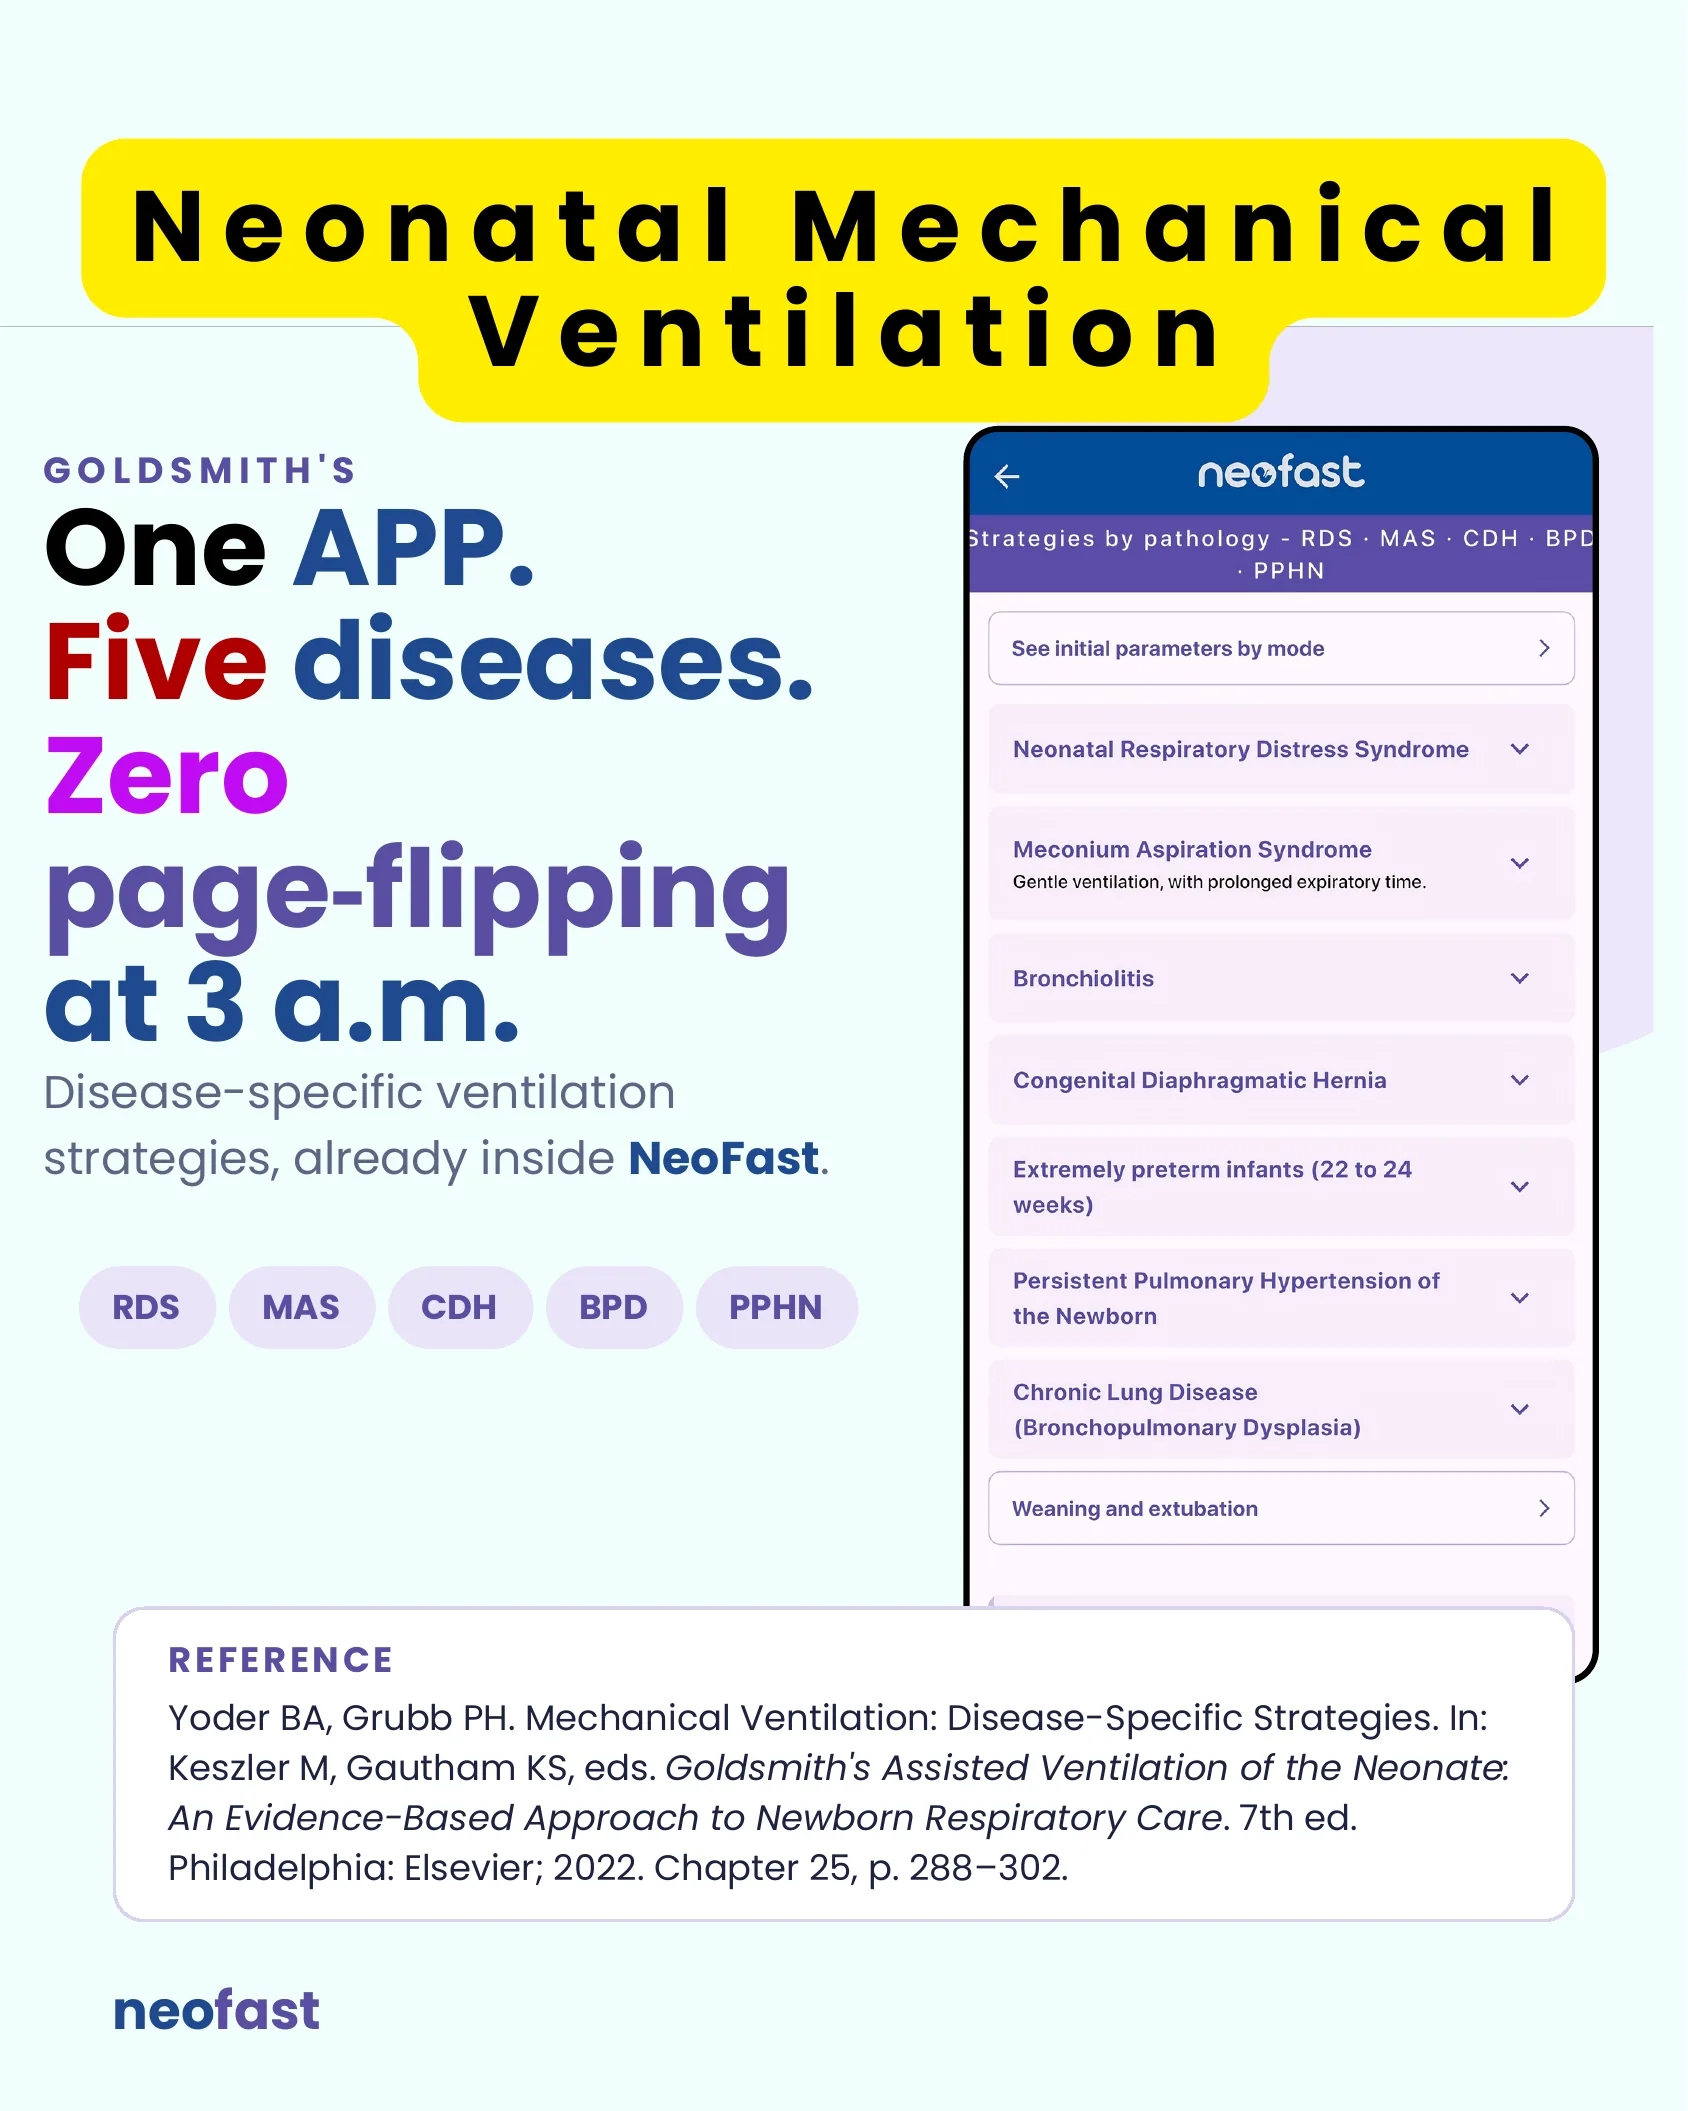
GOLDSMITH’S
One APP. Five diseases. Zero page-flipping at 3 a.m.
Disease-specific ventilation strategies, already inside NeoFast.
- RDS
- MAS
- CDH
- BPD
- PPHN
App screenshot shows a ‘Strategies by pathology’ menu listing: See initial parameters by mode; Neonatal Respiratory Distress Syndrome; Meconium Aspiration Syndrome (Gentle ventilation, with prolonged expiratory time); Bronchiolitis; Congenital Diaphragmatic Hernia; Extremely preterm infants (22 to 24 weeks); Persistent Pulmonary Hypertension of the Newborn; Chronic Lung Disease (Bronchopulmonary Dysplasia); Weaning and extubation.
NeoFast App Navigation for Respiratory Monitoring
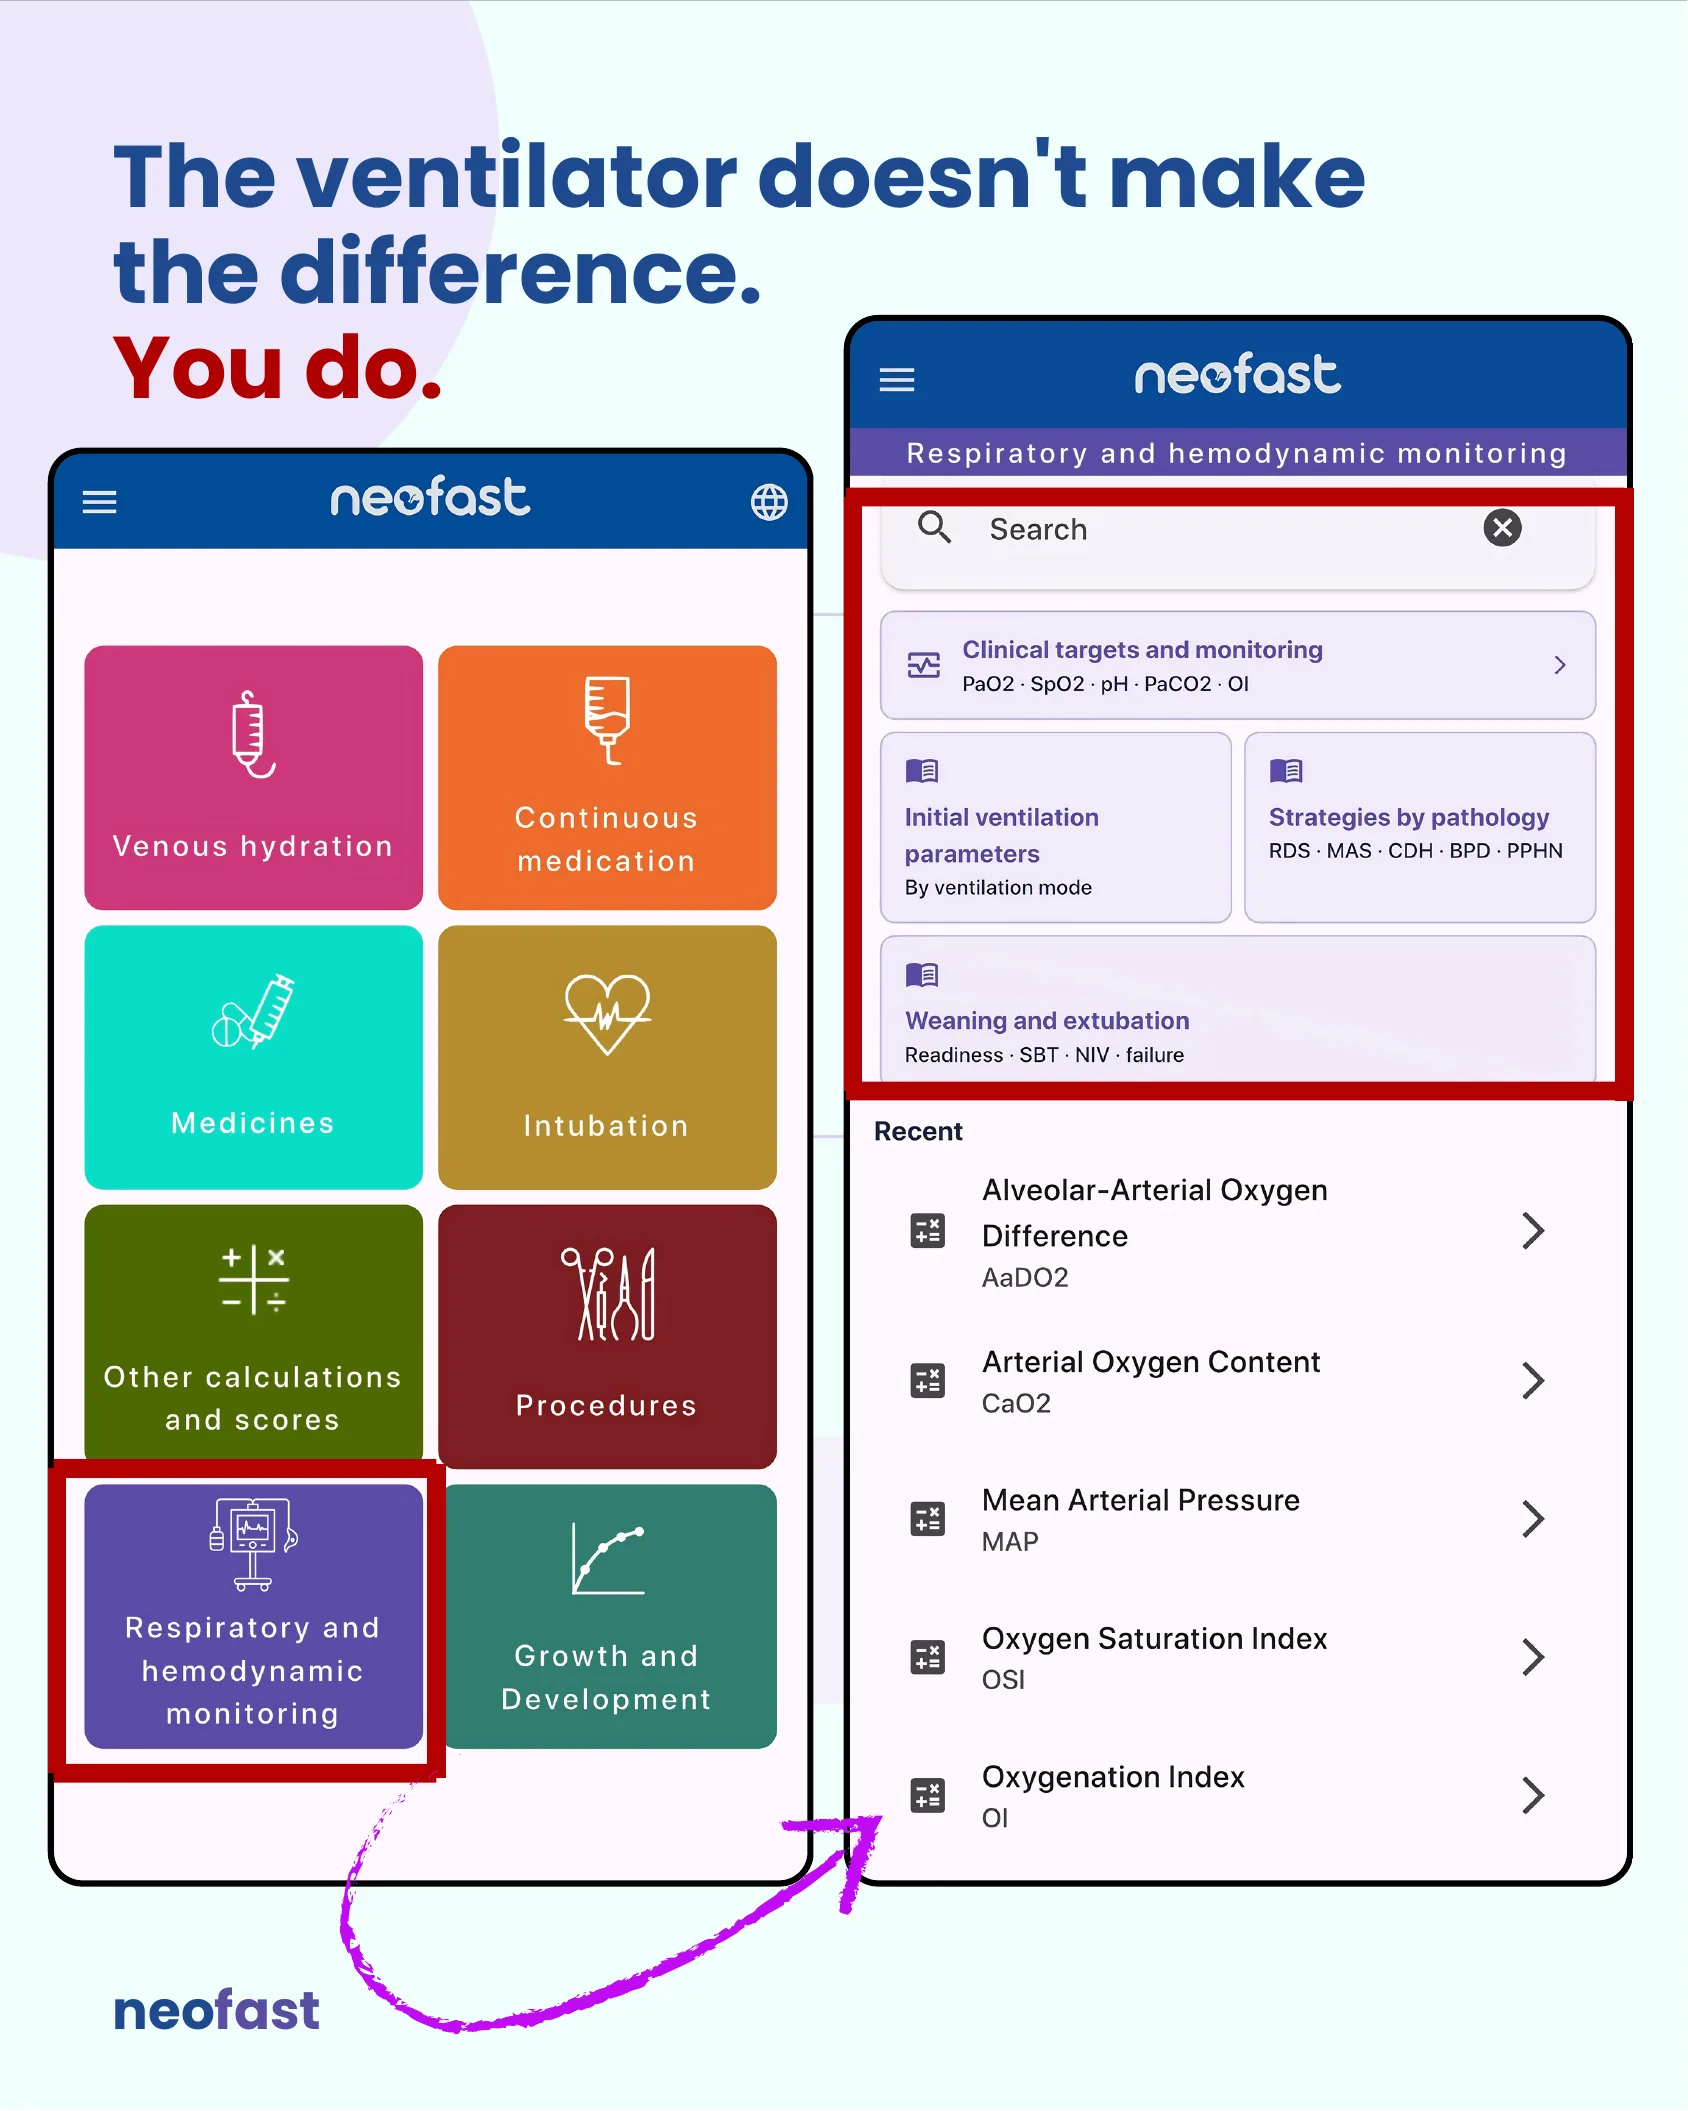
The ventilator doesn’t make the difference. You do.
Main menu tiles: Venous hydration, Continuous medication, Medicines, Intubation, Other calculations and scores, Procedures, Respiratory and hemodynamic monitoring (highlighted), Growth and Development.
Respiratory and hemodynamic monitoring submenu (highlighted):
- Search bar
- Clinical targets and monitoring – PaO2 · SpO2 · pH · PaCO2 · OI
- Initial ventilation parameters – By ventilation mode
- Strategies by pathology – RDS · MAS · CDH · BPD · PPHN
- Weaning and extubation – Readiness · SBT · NIV · failure
Recent calculators listed: Alveolar-Arterial Oxygen Difference (AaDO2); Arterial Oxygen Content (CaO2); Mean Arterial Pressure (MAP); Oxygen Saturation Index (OSI); Oxygenation Index (OI).
Dominant Problem and Ventilation Goal by Disease
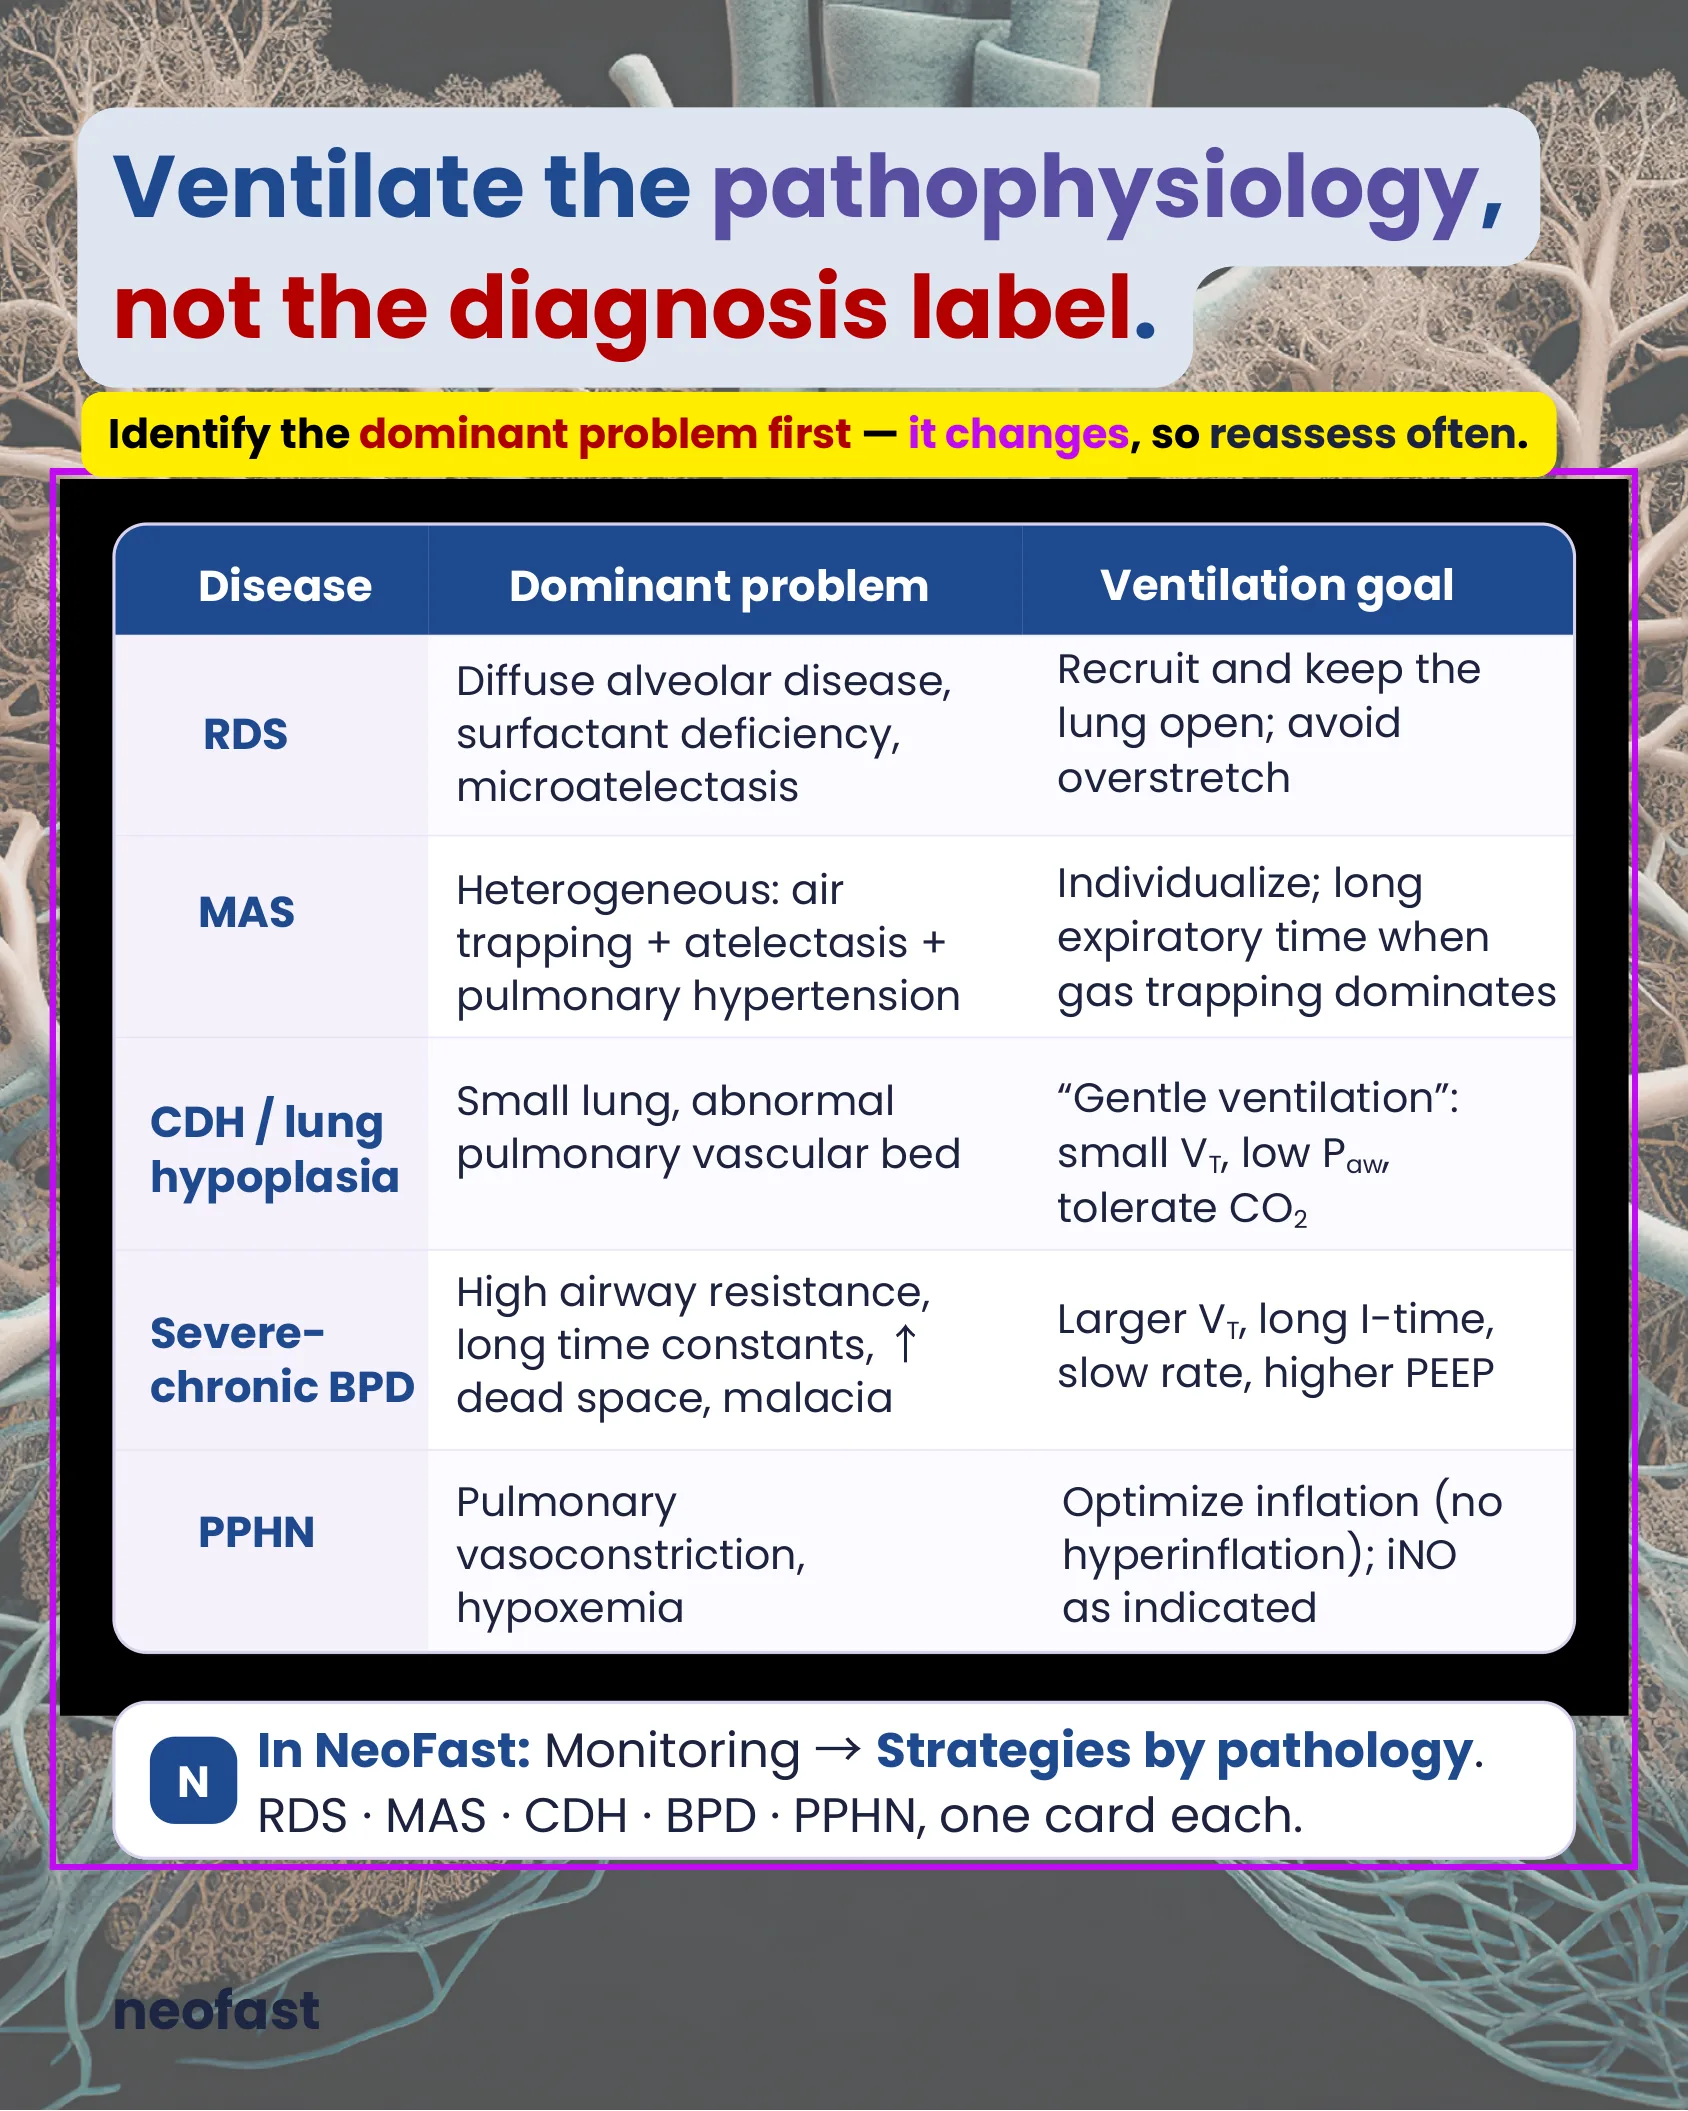
Ventilate the pathophysiology, not the diagnosis label.
Identify the dominant problem first — it changes, so reassess often.
| Disease | Dominant problem | Ventilation goal |
|---|---|---|
| RDS | Diffuse alveolar disease, surfactant deficiency, microatelectasis | Recruit and keep the lung open; avoid overstretch |
| MAS | Heterogeneous: air trapping + atelectasis + pulmonary hypertension | Individualize; long expiratory time when gas trapping dominates |
| CDH / lung hypoplasia | Small lung, abnormal pulmonary vascular bed | “Gentle ventilation”: small VT, low Paw, tolerate CO2 |
| Severe-chronic BPD | High airway resistance, long time constants, ↑ dead space, malacia | Larger VT, long I-time, slow rate, higher PEEP |
| PPHN | Pulmonary vasoconstriction, hypoxemia | Optimize inflation (no hyperinflation); iNO as indicated |
In NeoFast: Monitoring → Strategies by pathology. RDS · MAS · CDH · BPD · PPHN, one card each.
Volume-Targeted SIMV + PS Settings by Disease
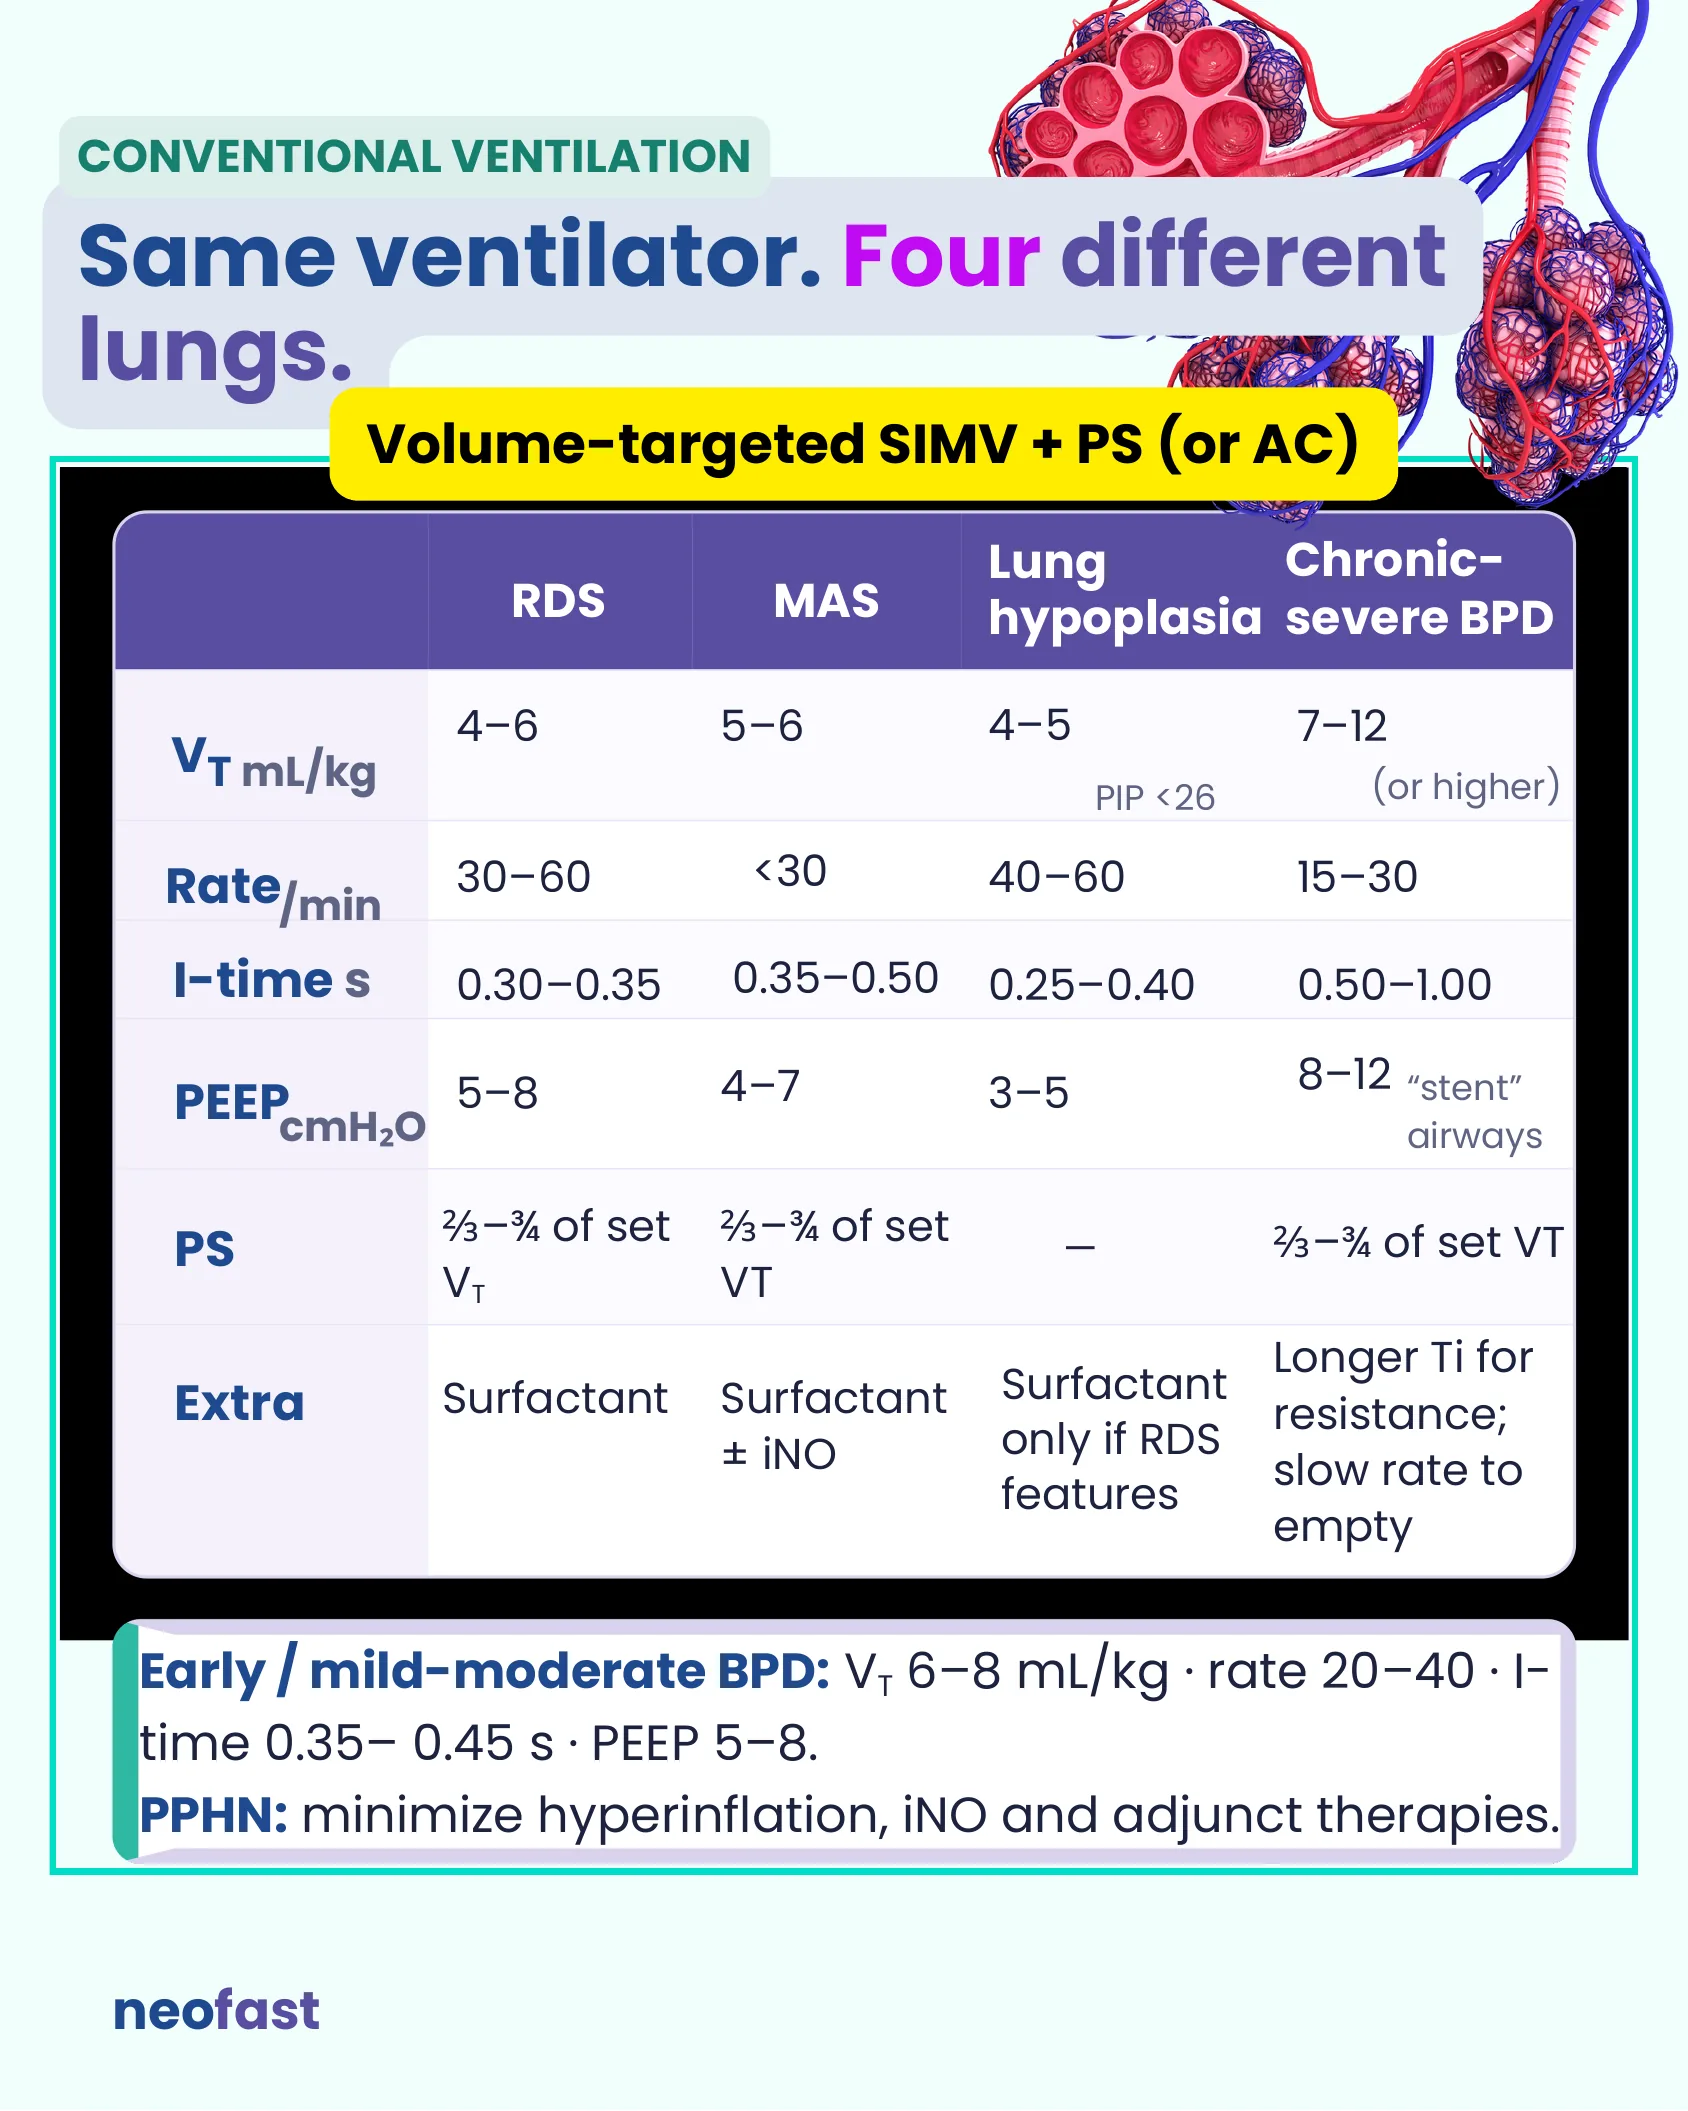
CONVENTIONAL VENTILATION
Same ventilator. Four different lungs.
Volume-targeted SIMV + PS (or AC)
| RDS | MAS | Lung hypoplasia | Chronic-severe BPD | |
|---|---|---|---|---|
| VT mL/kg | 4–6 | 5–6 | 4–5 (PIP <26) | 7–12 (or higher) |
| Rate /min | 30–60 | <30 | 40–60 | 15–30 |
| I-time s | 0.30–0.35 | 0.35–0.50 | 0.25–0.40 | 0.50–1.00 |
| PEEP cmH2O | 5–8 | 4–7 | 3–5 | 8–12 “stent” airways |
| PS | ⅔–¾ of set VT | ⅔–¾ of set VT | — | ⅔–¾ of set VT |
| Extra | Surfactant | Surfactant ± iNO | Surfactant only if RDS features | Longer Ti for resistance; slow rate to empty |
Early / mild-moderate BPD: VT 6–8 mL/kg · rate 20–40 · I-time 0.35–0.45 s · PEEP 5–8.
PPHN: minimize hyperinflation, iNO and adjunct therapies.
HFOV and HFJV Starting Points by Disease
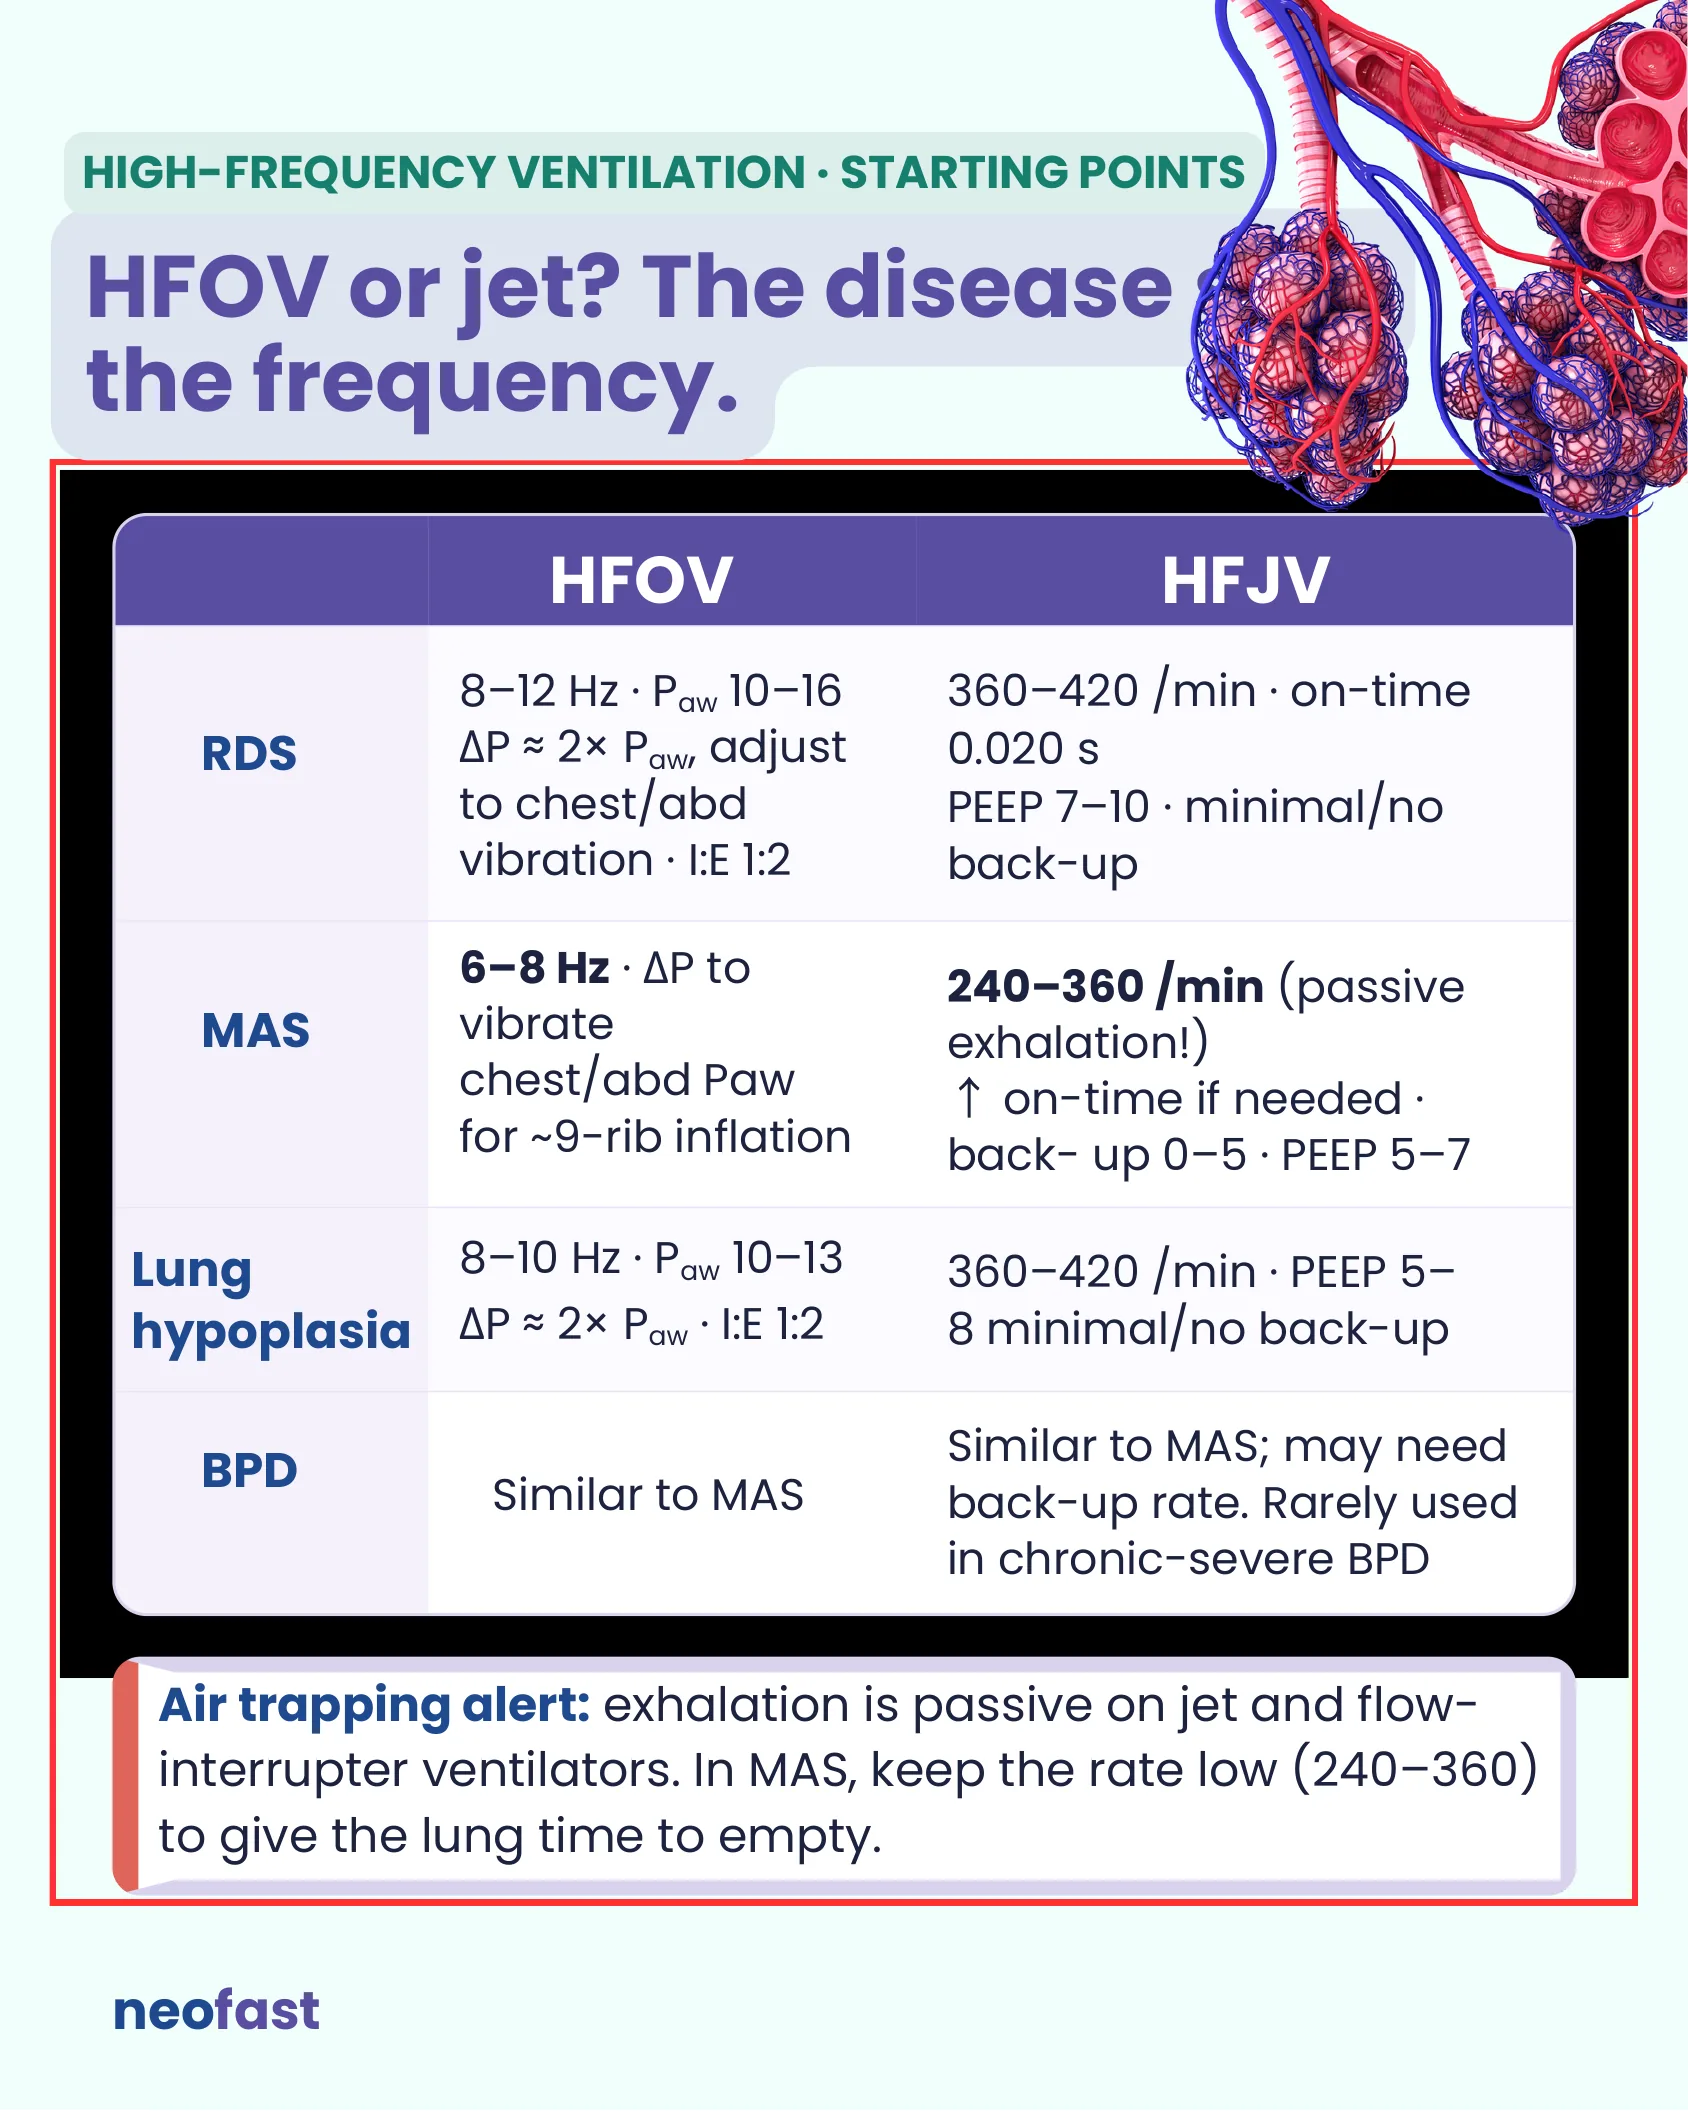
HIGH-FREQUENCY VENTILATION · STARTING POINTS
HFOV or jet? The disease sets the frequency.
| HFOV | HFJV | |
|---|---|---|
| RDS | 8–12 Hz · Paw 10–16, ΔP ≈ 2× Paw, adjust to chest/abd vibration · I:E 1:2 | 360–420 /min · on-time 0.020 s, PEEP 7–10 · minimal/no back-up |
| MAS | 6–8 Hz · ΔP to vibrate chest/abd, Paw for ~9-rib inflation | 240–360 /min (passive exhalation!) ↑ on-time if needed · back-up 0–5 · PEEP 5–7 |
| Lung hypoplasia | 8–10 Hz · Paw 10–13, ΔP ≈ 2× Paw · I:E 1:2 | 360–420 /min · PEEP 5–8 minimal/no back-up |
| BPD | Similar to MAS | Similar to MAS; may need back-up rate. Rarely used in chronic-severe BPD |
Air trapping alert: exhalation is passive on jet and flow-interrupter ventilators. In MAS, keep the rate low (240–360) to give the lung time to empty.
RDS: Initial HFOV and SIMV Settings by Weight
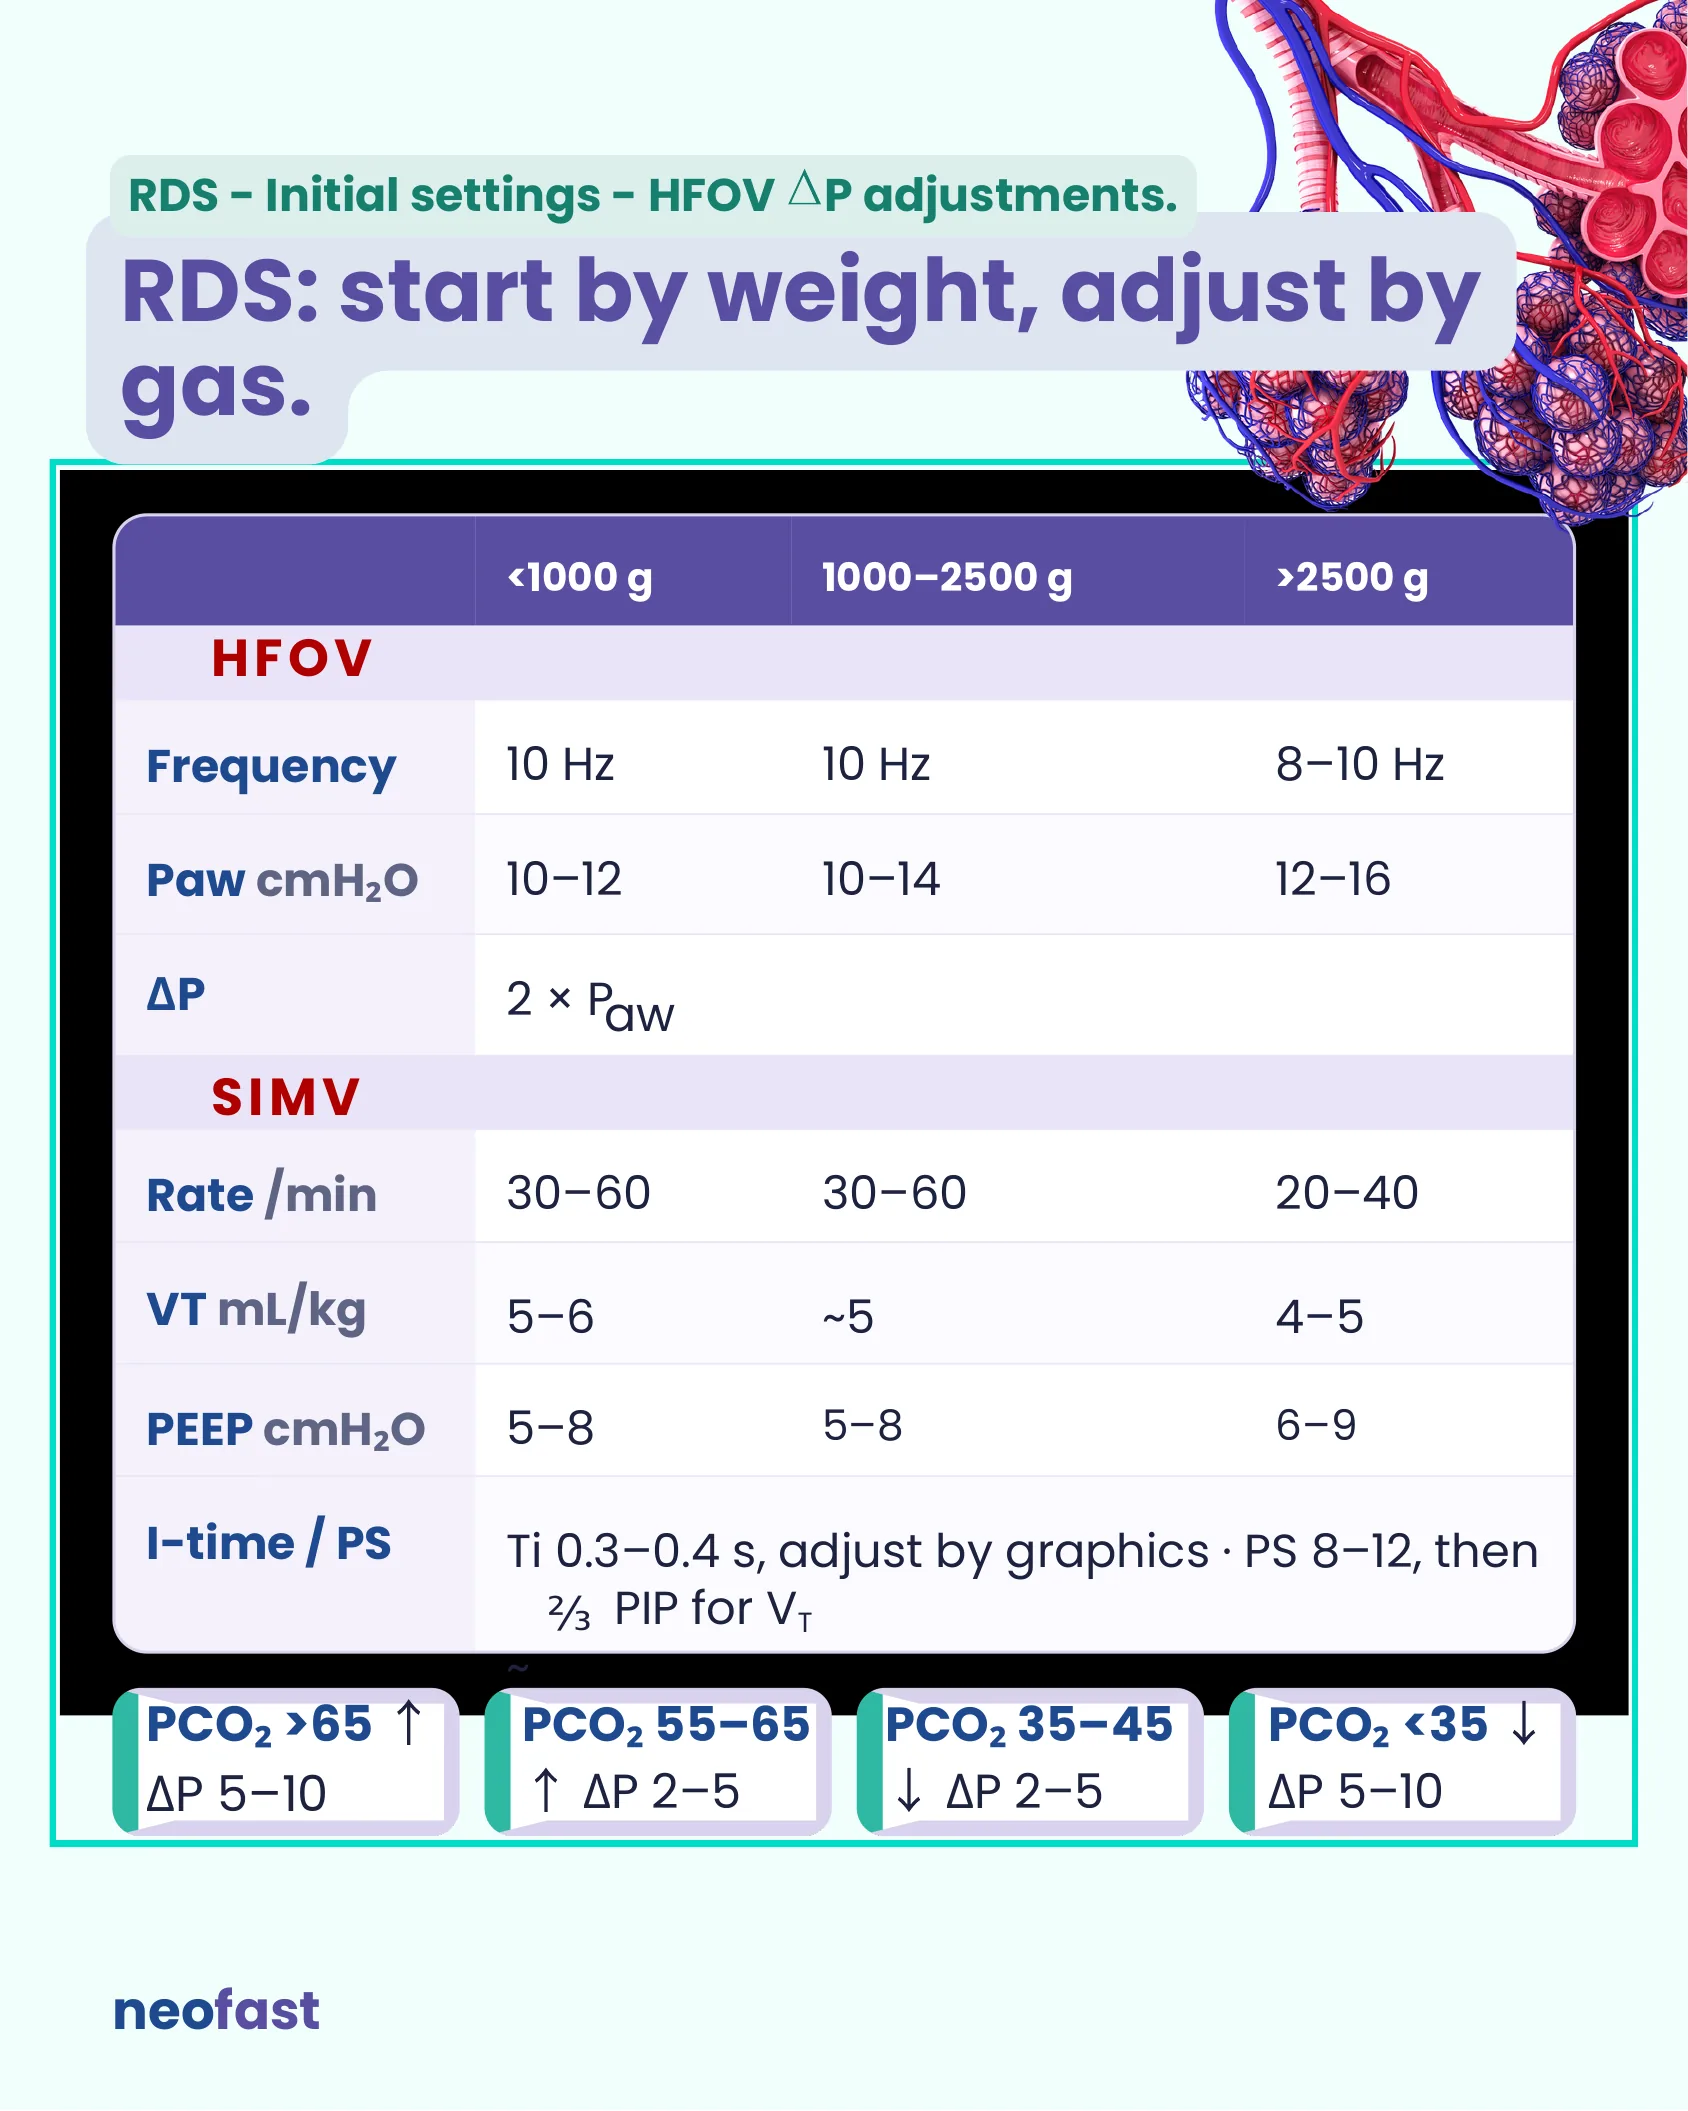 HFOV
- PCO2 >65 → ↑ ΔP 5–10
- PCO2 55–65 → ↑ ΔP 2–5
- PCO2 35–45 → ↓ ΔP 2–5
- PCO2 <35 → ↓ ΔP 5–10
MAS: Three Phenotypes and Mode-Specific Strategies
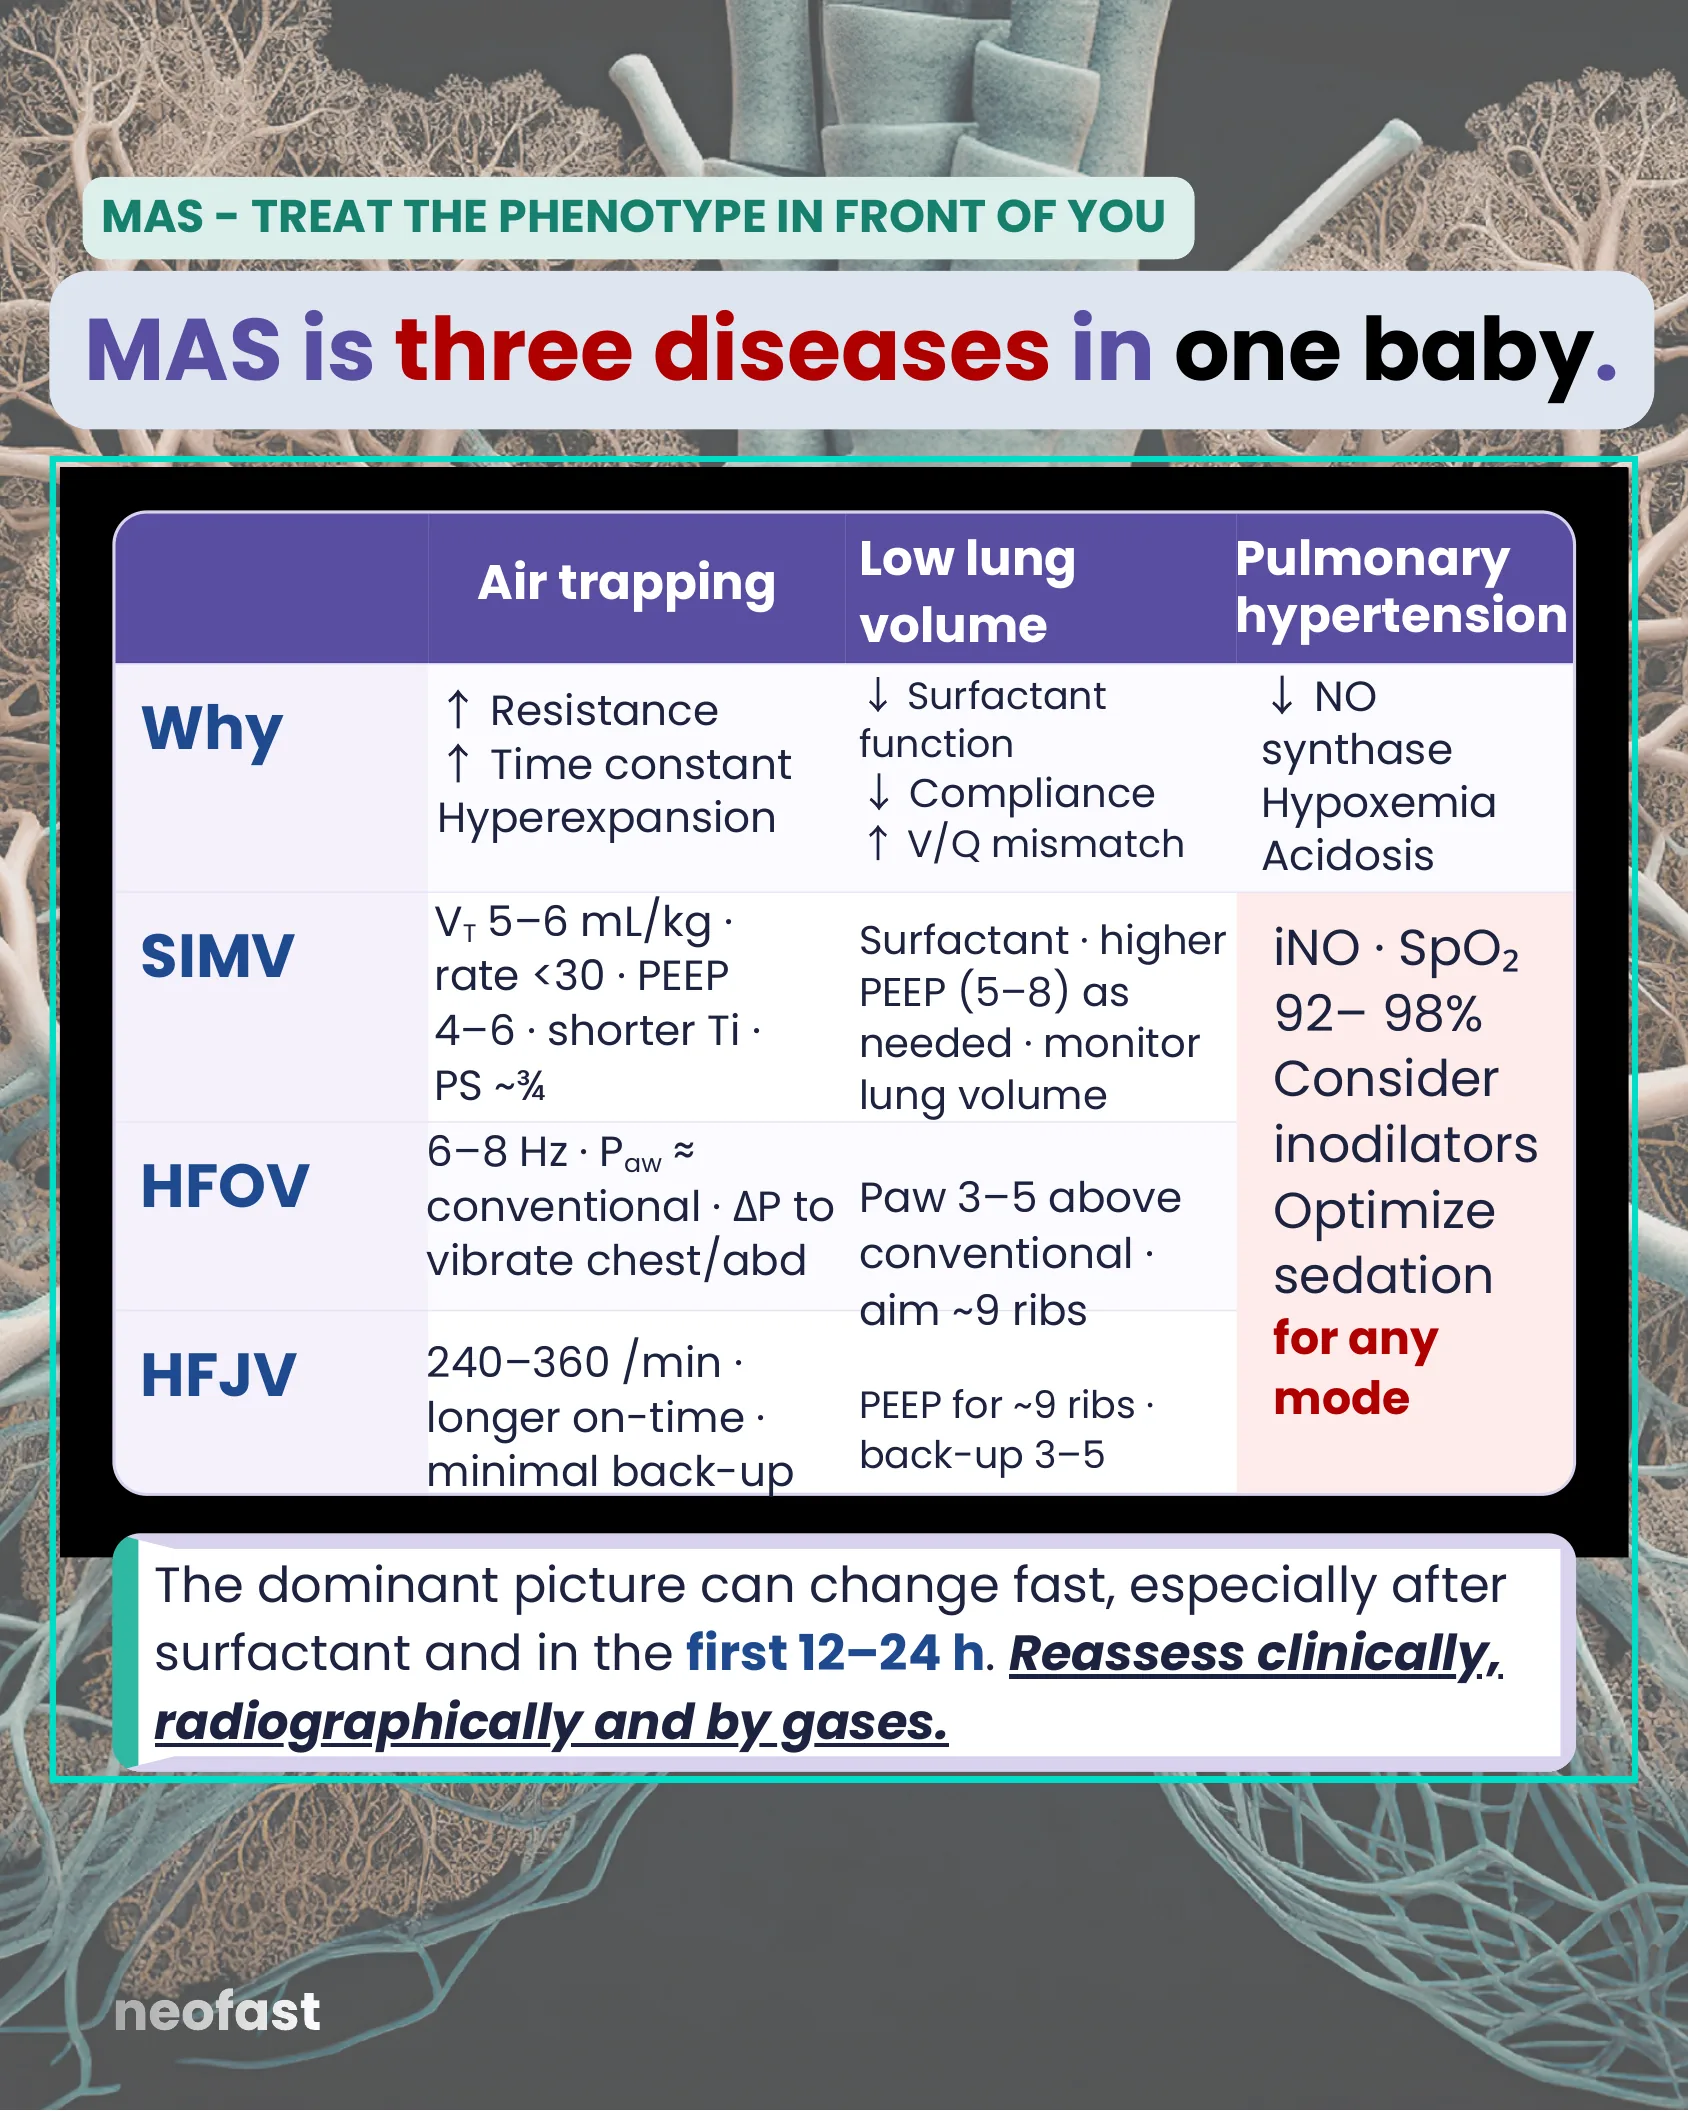
MAS – TREAT THE PHENOTYPE IN FRONT OF YOU
MAS is three diseases in one baby.
| Air trapping | Low lung volume | Pulmonary hypertension | |
|---|---|---|---|
| Why | ↑ Resistance, ↑ Time constant, Hyperexpansion | ↓ Surfactant function, ↓ Compliance, ↑ V/Q mismatch | ↓ NO synthase, Hypoxemia, Acidosis |
| SIMV | VT 5–6 mL/kg · rate <30 · PEEP 4–6 · shorter Ti · PS ~¾ | Surfactant · higher PEEP (5–8) as needed · monitor lung volume | iNO · SpO2 92–98% Consider inodilators Optimize sedation for any mode |
| HFOV | 6–8 Hz · Paw ≈ conventional · ΔP to vibrate chest/abd | Paw 3–5 above conventional · aim ~9 ribs | |
| HFJV | 240–360 /min · longer on-time · minimal back-up | PEEP for ~9 ribs · back-up 3–5 |
The dominant picture can change fast, especially after surfactant and in the first 12–24 h. Reassess clinically, radiographically and by gases.
CDH / Lung Hypoplasia: Gentle Ventilation Settings
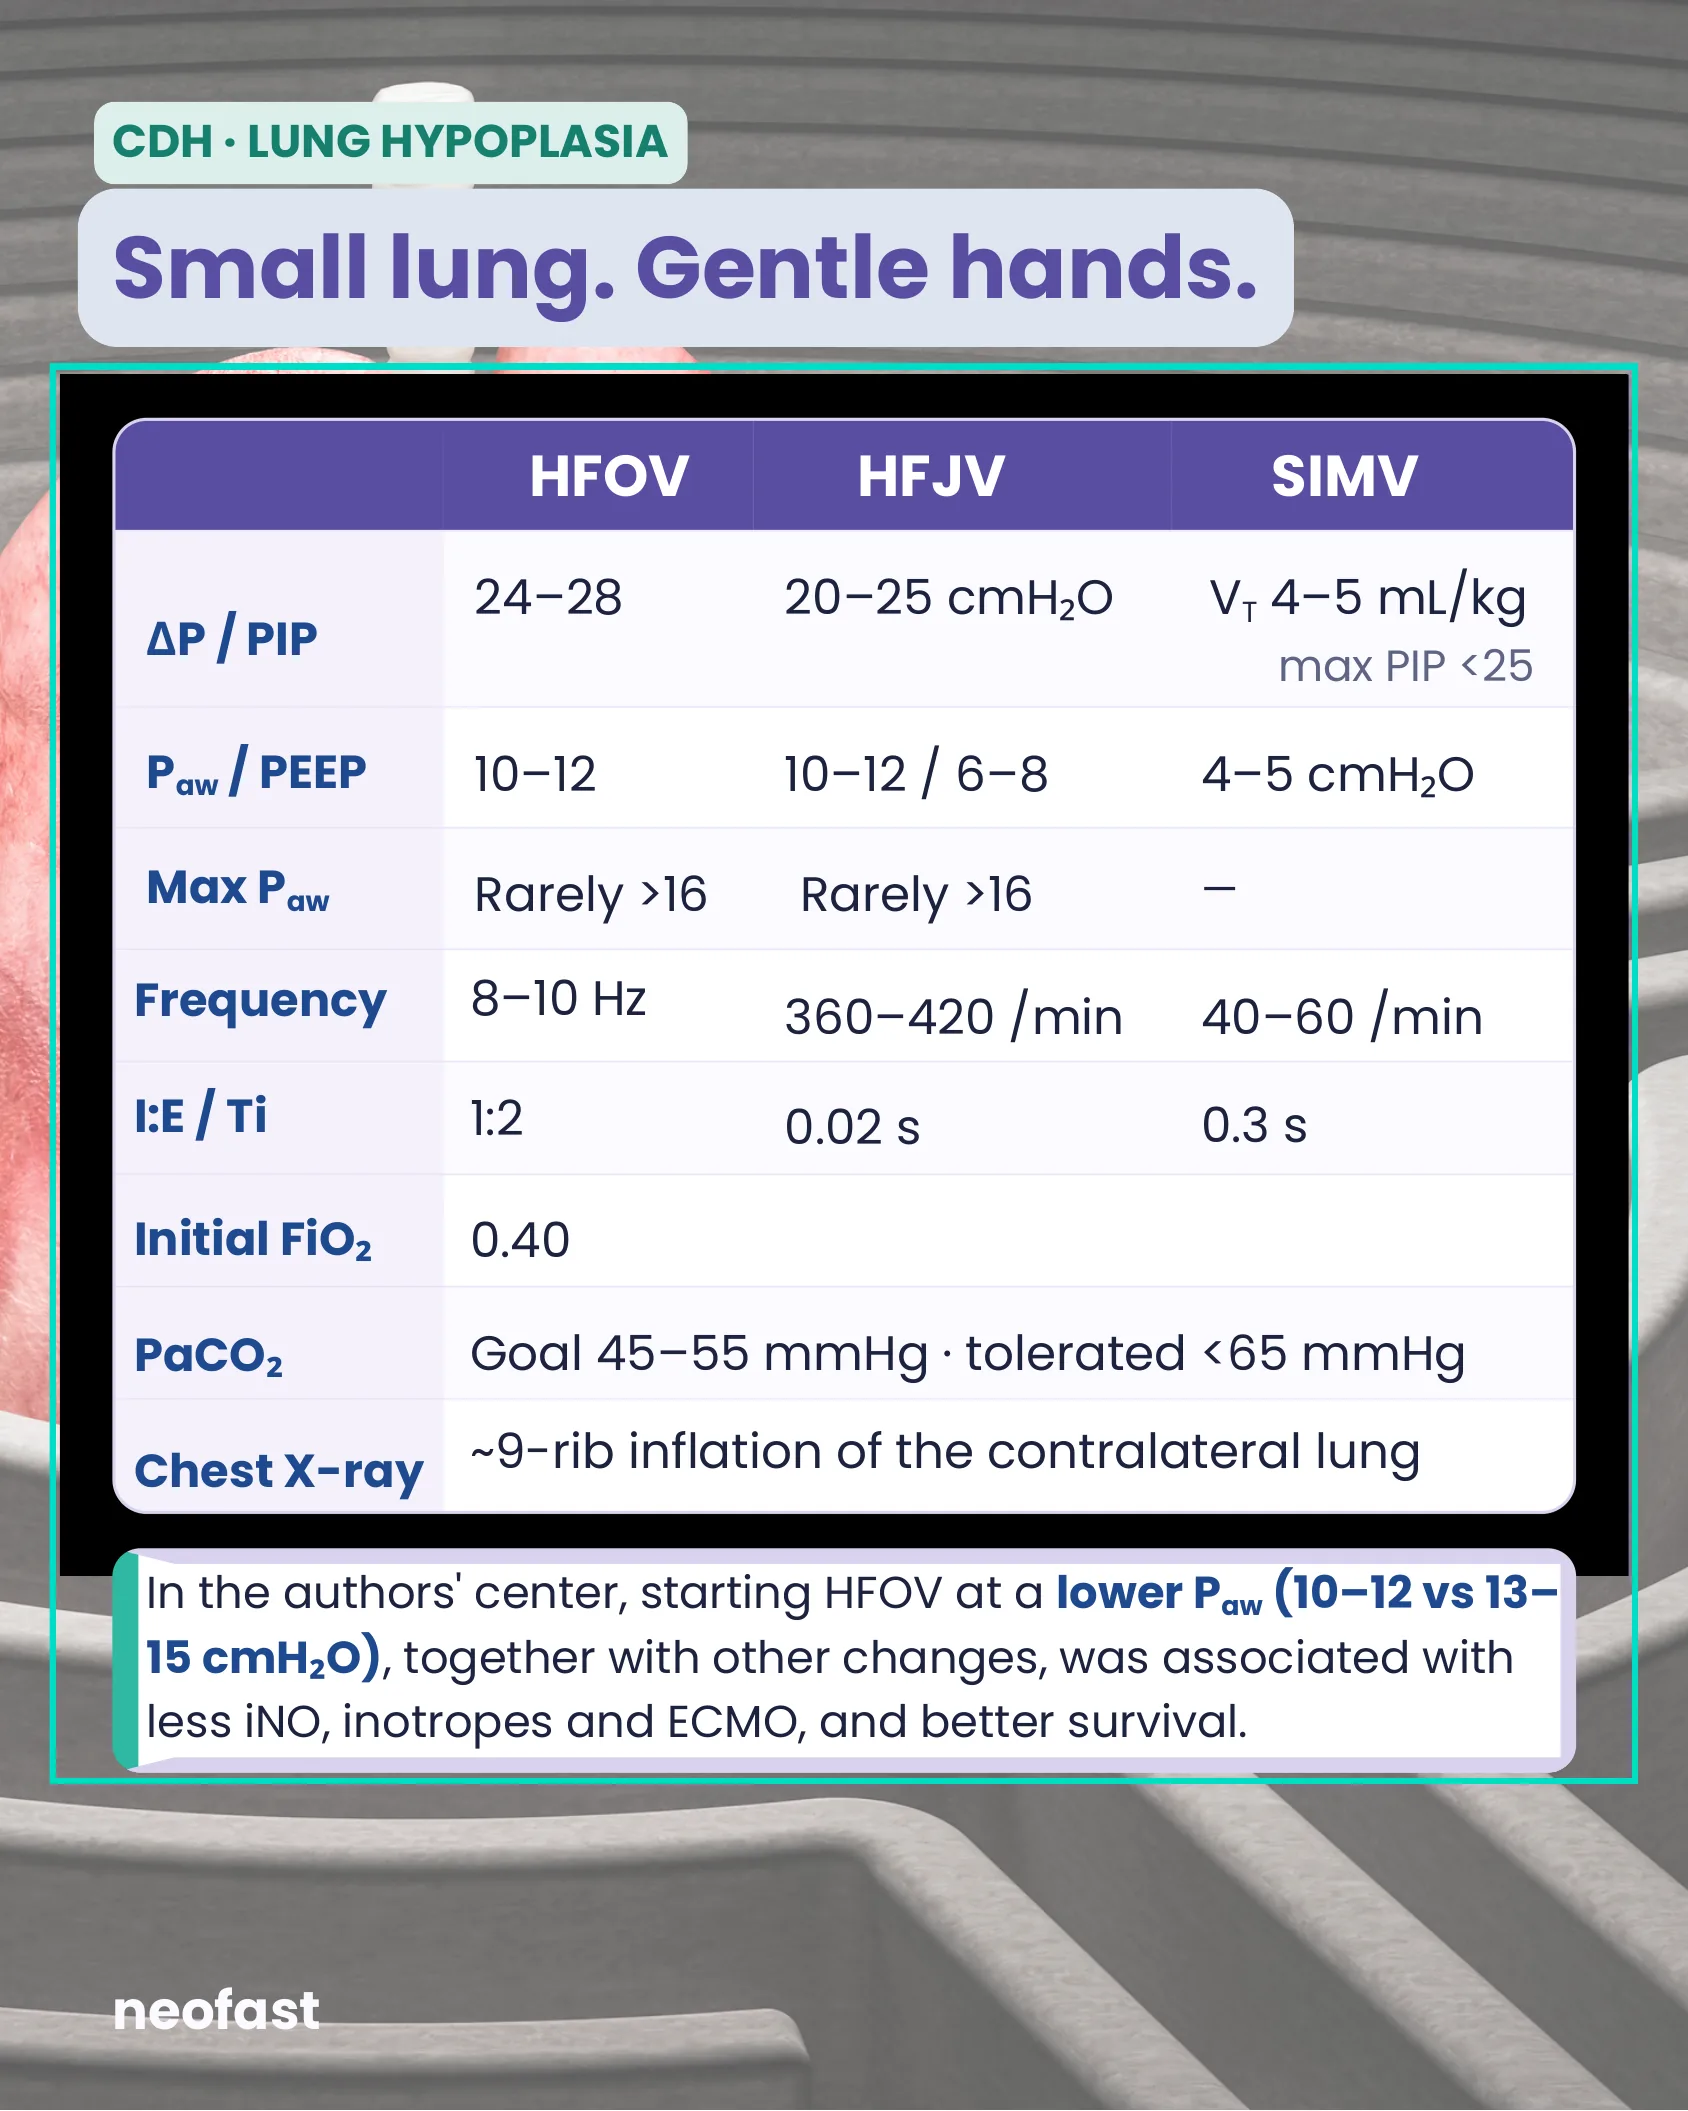
CDH · LUNG HYPOPLASIA
Small lung. Gentle hands.
| HFOV | HFJV | SIMV | |
|---|---|---|---|
| ΔP / PIP | 24–28 | 20–25 cmH2O | VT 4–5 mL/kg, max PIP <25 |
| Paw / PEEP | 10–12 | 10–12 / 6–8 | 4–5 cmH2O |
| Max Paw | Rarely >16 | Rarely >16 | — |
| Frequency | 8–10 Hz | 360–420 /min | 40–60 /min |
| I:E / Ti | 1:2 | 0.02 s | 0.3 s |
| Initial FiO2 | 0.40 | ||
| PaCO2 | Goal 45–55 mmHg · tolerated <65 mmHg | ||
| Chest X-ray | ~9-rib inflation of the contralateral lung | ||
In the authors’ center, starting HFOV at a lower Paw (10–12 vs 13–15 cmH2O), together with other changes, was associated with less iNO, inotropes and ECMO, and better survival.
BPD – Approach by severity
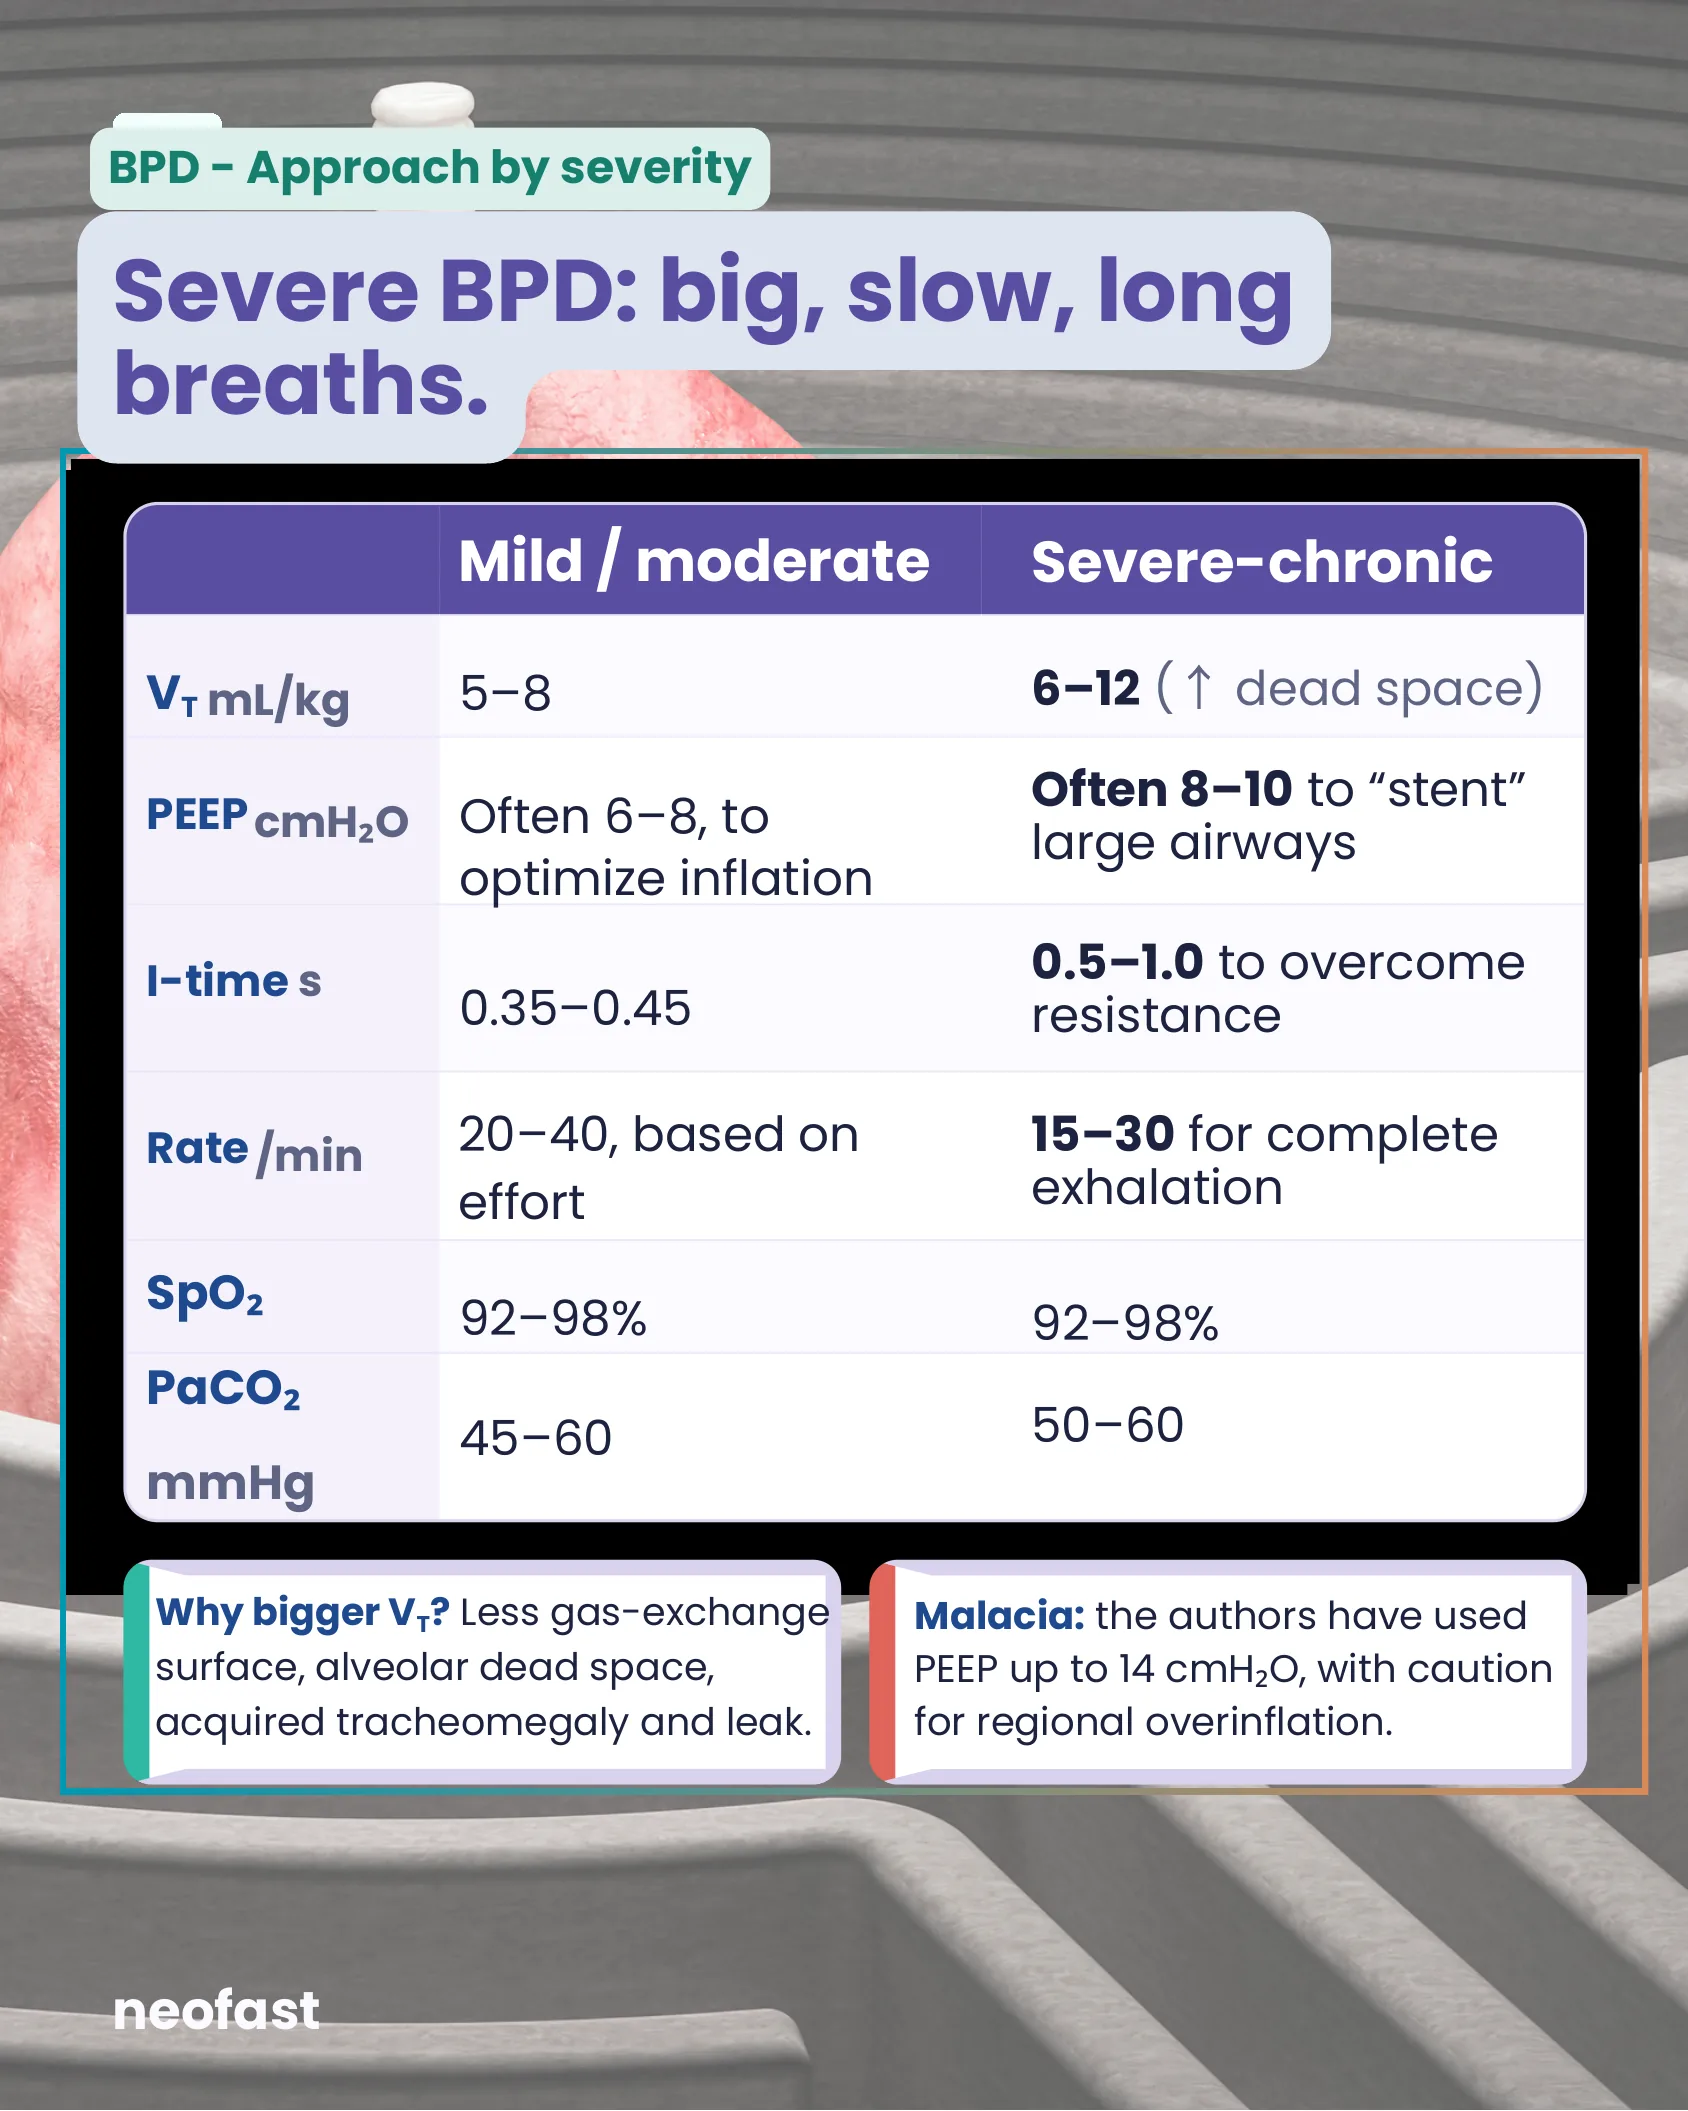
BPD – Approach by severity
Severe BPD: big, slow, long breaths.
| Mild / moderate | Severe-chronic | |
|---|---|---|
| VT mL/kg | 5-8 | 6-12 (↑ dead space) |
| PEEP cmH₂O | Often 6-8, to optimize inflation | Often 8-10 to “stent” large airways |
| I-time s | 0.35-0.45 | 0.5-1.0 to overcome resistance |
| Rate /min | 20-40, based on effort | 15-30 for complete exhalation |
| SpO₂ | 92-98% | 92-98% |
| PaCO₂ mmHg | 45-60 | 50-60 |
Why bigger VT? Less gas-exchange surface, alveolar dead space, acquired tracheomegaly and leak.
Malacia: the authors have used PEEP up to 14 cmH₂O, with caution for regional overinflation.
Weaning starts on day one
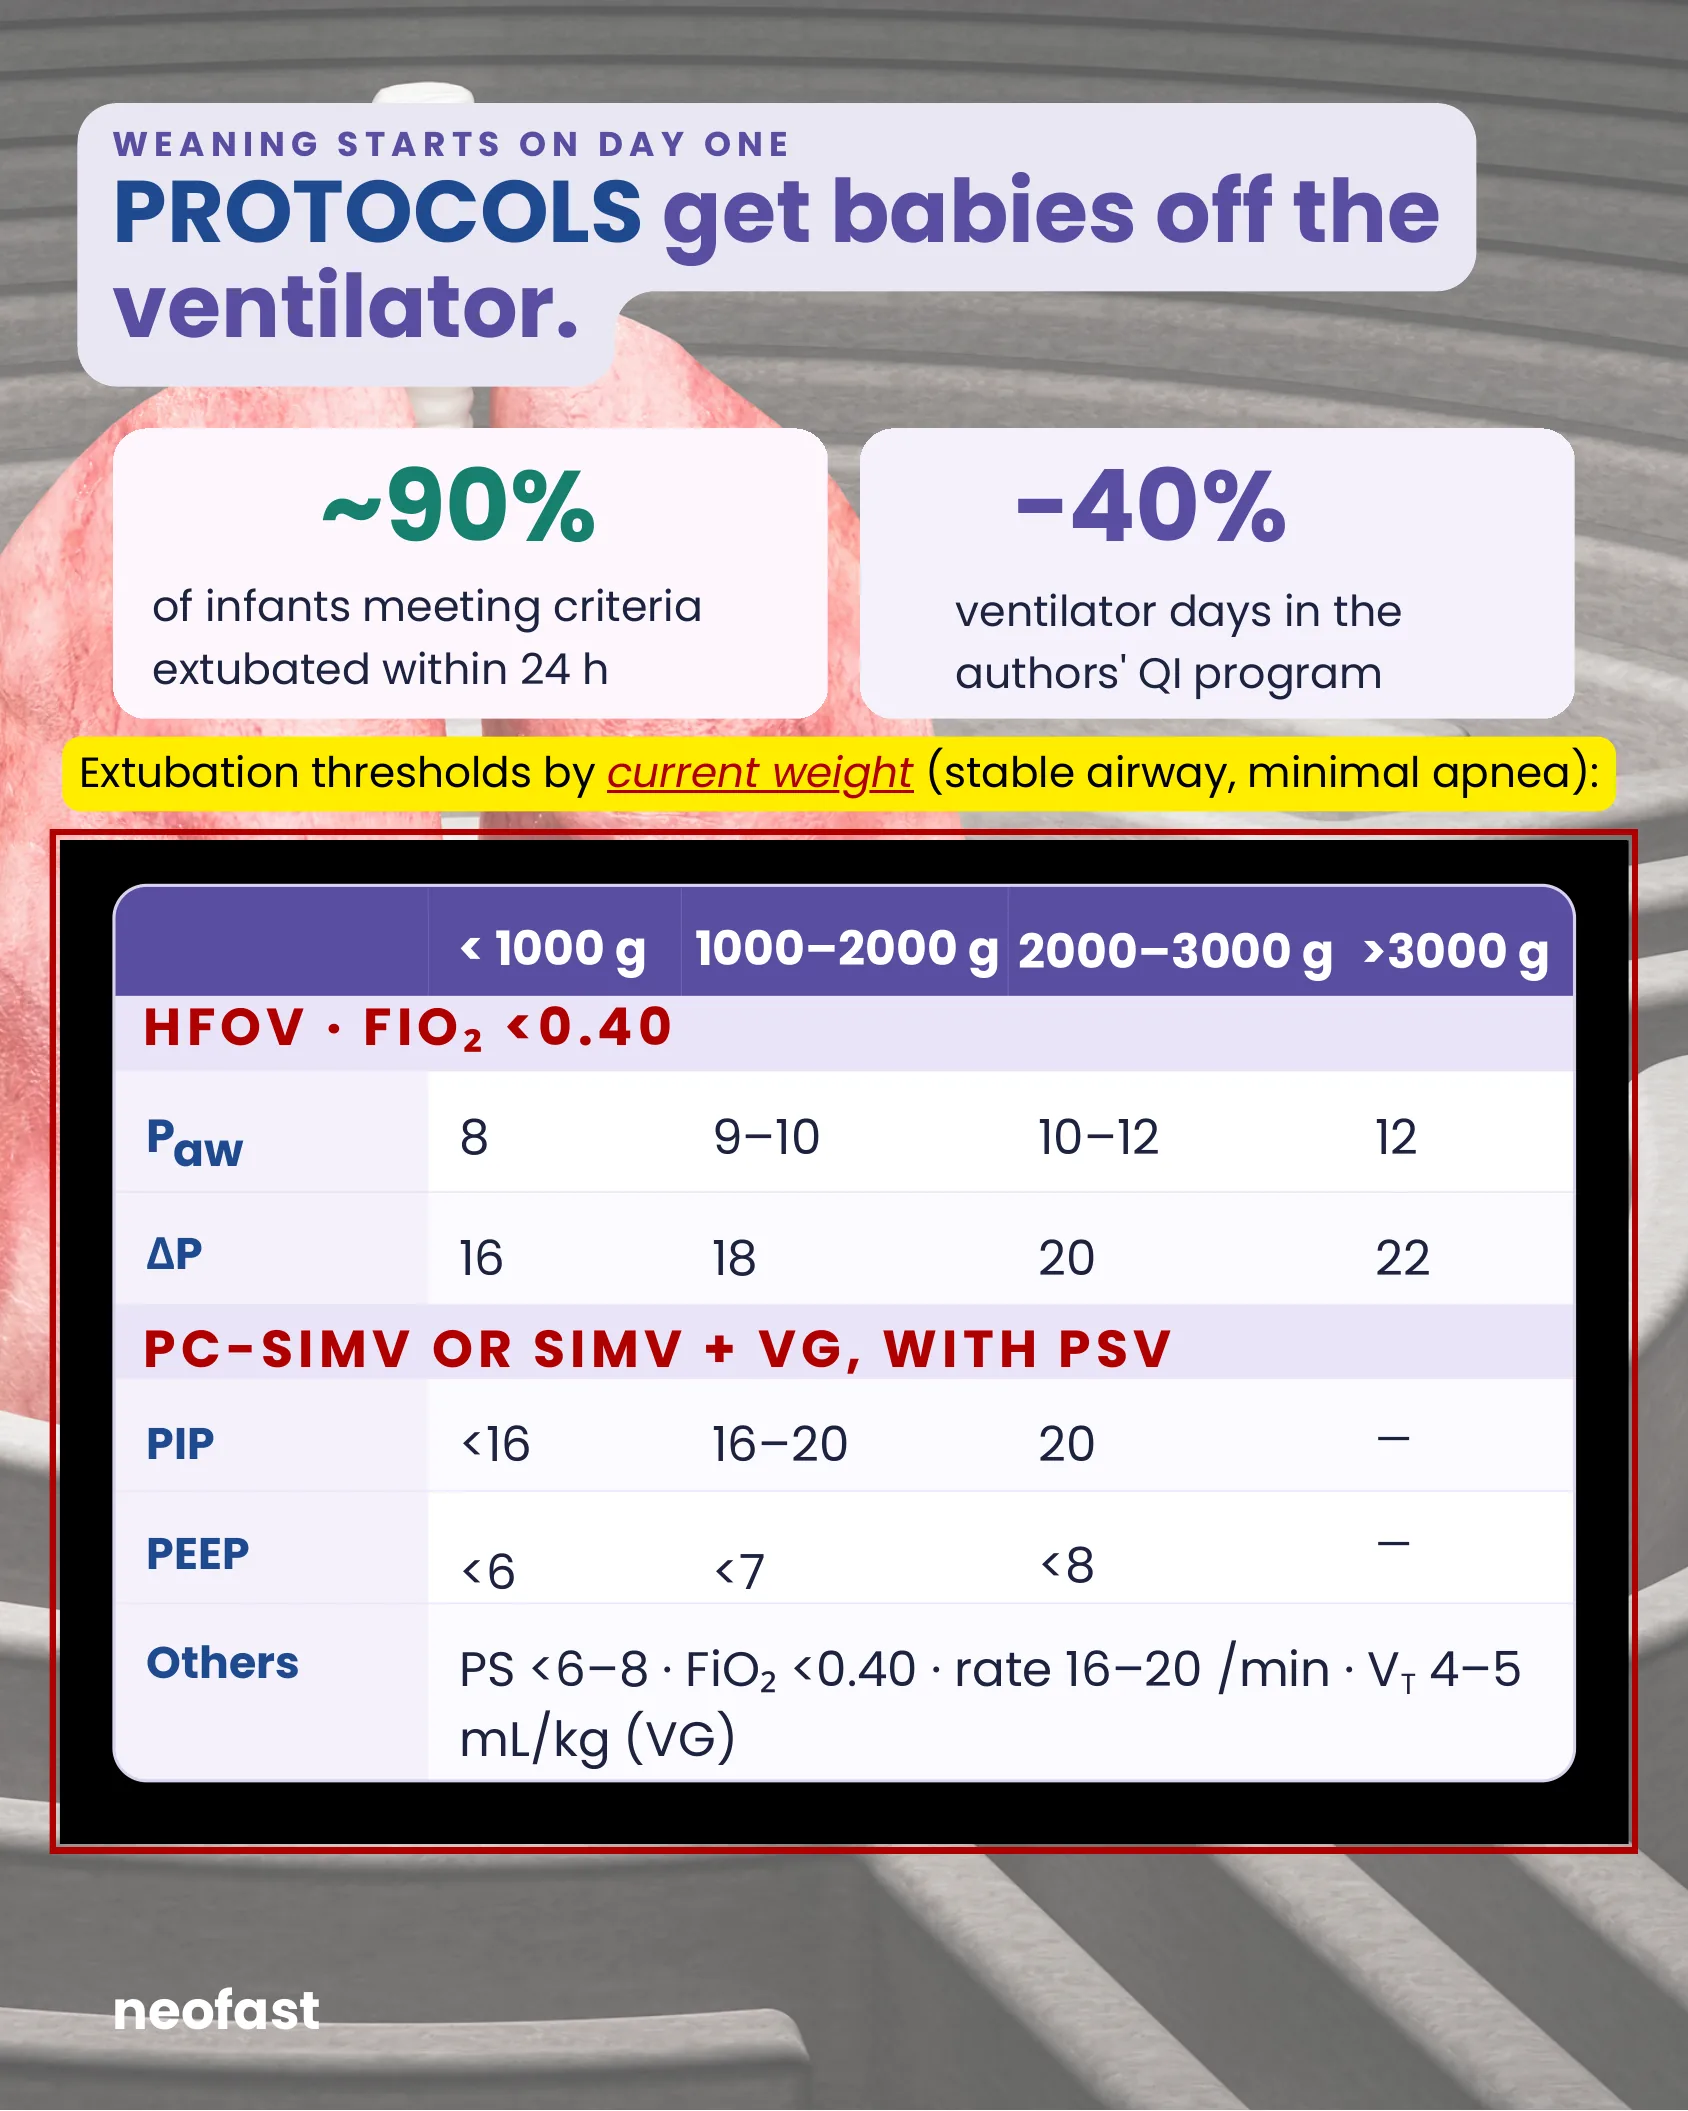
WEANING STARTS ON DAY ONE
PROTOCOLS get babies off the ventilator.
~90% of infants meeting criteria extubated within 24 h
-40% ventilator days in the authors’ QI program
Extubation thresholds by current weight (stable airway, minimal apnea):
| <1000 g | 1000-2000 g | 2000-3000 g | >3000 g | |
|---|---|---|---|---|
| HFOV · FiO₂ <0.40 | ||||
| Paw | 8 | 9-10 | 10-12 | 12 |
| ΔP | 16 | 18 | 20 | 22 |
| PC-SIMV OR SIMV + VG, WITH PSV | ||||
| PIP | <16 | 16-20 | 20 | – |
| PEEP | <6 | <7 | <8 | – |
| Others | PS <6-8 · FiO₂ <0.40 · rate 16-20 /min · VT 4-5 mL/kg (VG) | |||
One hub: targets by disease & settings by mode

NOW IMAGINE ALL OF THIS…
…in your pocket, at the bedside.
One hub
Clinical targets and monitoring – PaO2 · SpO2 · pH · PaCO2 · OI
Oxygenation and ventilation targets
| PaO2 (RDS) | 50 to 70 mmHg |
| SpO2 (RDS) | 90 to 94% |
| pH | 7.25 to 7.40 |
| PaCO2 (RDS) | 35 to 45 mmHg |
| PaCO2 (MAS) | 45 to 55 mmHg |
SpO2 by condition, according to Goldsmith
| MAS and PPHN | 92 to 98% |
| Mild to moderate BPD | 92 to 95% |
| Severe BPD | 92 to 98% |
| Pre-ductal CDH | Above 85% in the first hour, then 88 to 98% |
Permissive hypercapnia
| PaCO2 | 46 to 60 mmHg, frequently tolerated in Congenital Diaphragmatic Hernia and Meconium Aspiration Syndrome, to minimize lung injury |
Permissive hypercapnia, according to Goldsmith
| PaCO2 | 45 to 55 mmHg or higher, provided pH remains above 7.20 to 7.25 |
| CDH | 45 to 65 mmHg |
| Severe BPD | 50 to 65 mmHg, accepting compensated respiratory acidosis |
Standardizing CO2 targets prevents the clinical inertia of keeping the infant on high support just to achieve normal blood gases, and it is one of the facilitators of weaning.
Oxygenation Index (OI)
| Formula | OI = (MAP × FiO2 × 100) ÷ PaO2 |
| OI between 15 and 25 | Consider inhaled nitric oxide (iNO) |
| OI ≥ 40 | Indication for ECMO |
Initial ventilation parameters – By ventilation mode
- See strategies by pathology
NON-INVASIVE RESPIRATORY SUPPORT
- Nasal CPAP
- High-flow nasal cannula
- Nasal intermittent positive pressure ventilation
INVASIVE MECHANICAL VENTILATION
- PCV — Pressure controlled ventilation
- VCV — Volume controlled ventilation
- SIMV, A/C and PSV — trigger modes: How the ventilator responds to the infant’s effort. According to Goldsmith.
- VG / VTV — Volume guarantee
- NAVA — Neurally adjusted ventilatory assist
- HFJV — High-frequency jet ventilation
Weaning & respiratory monitoring tools
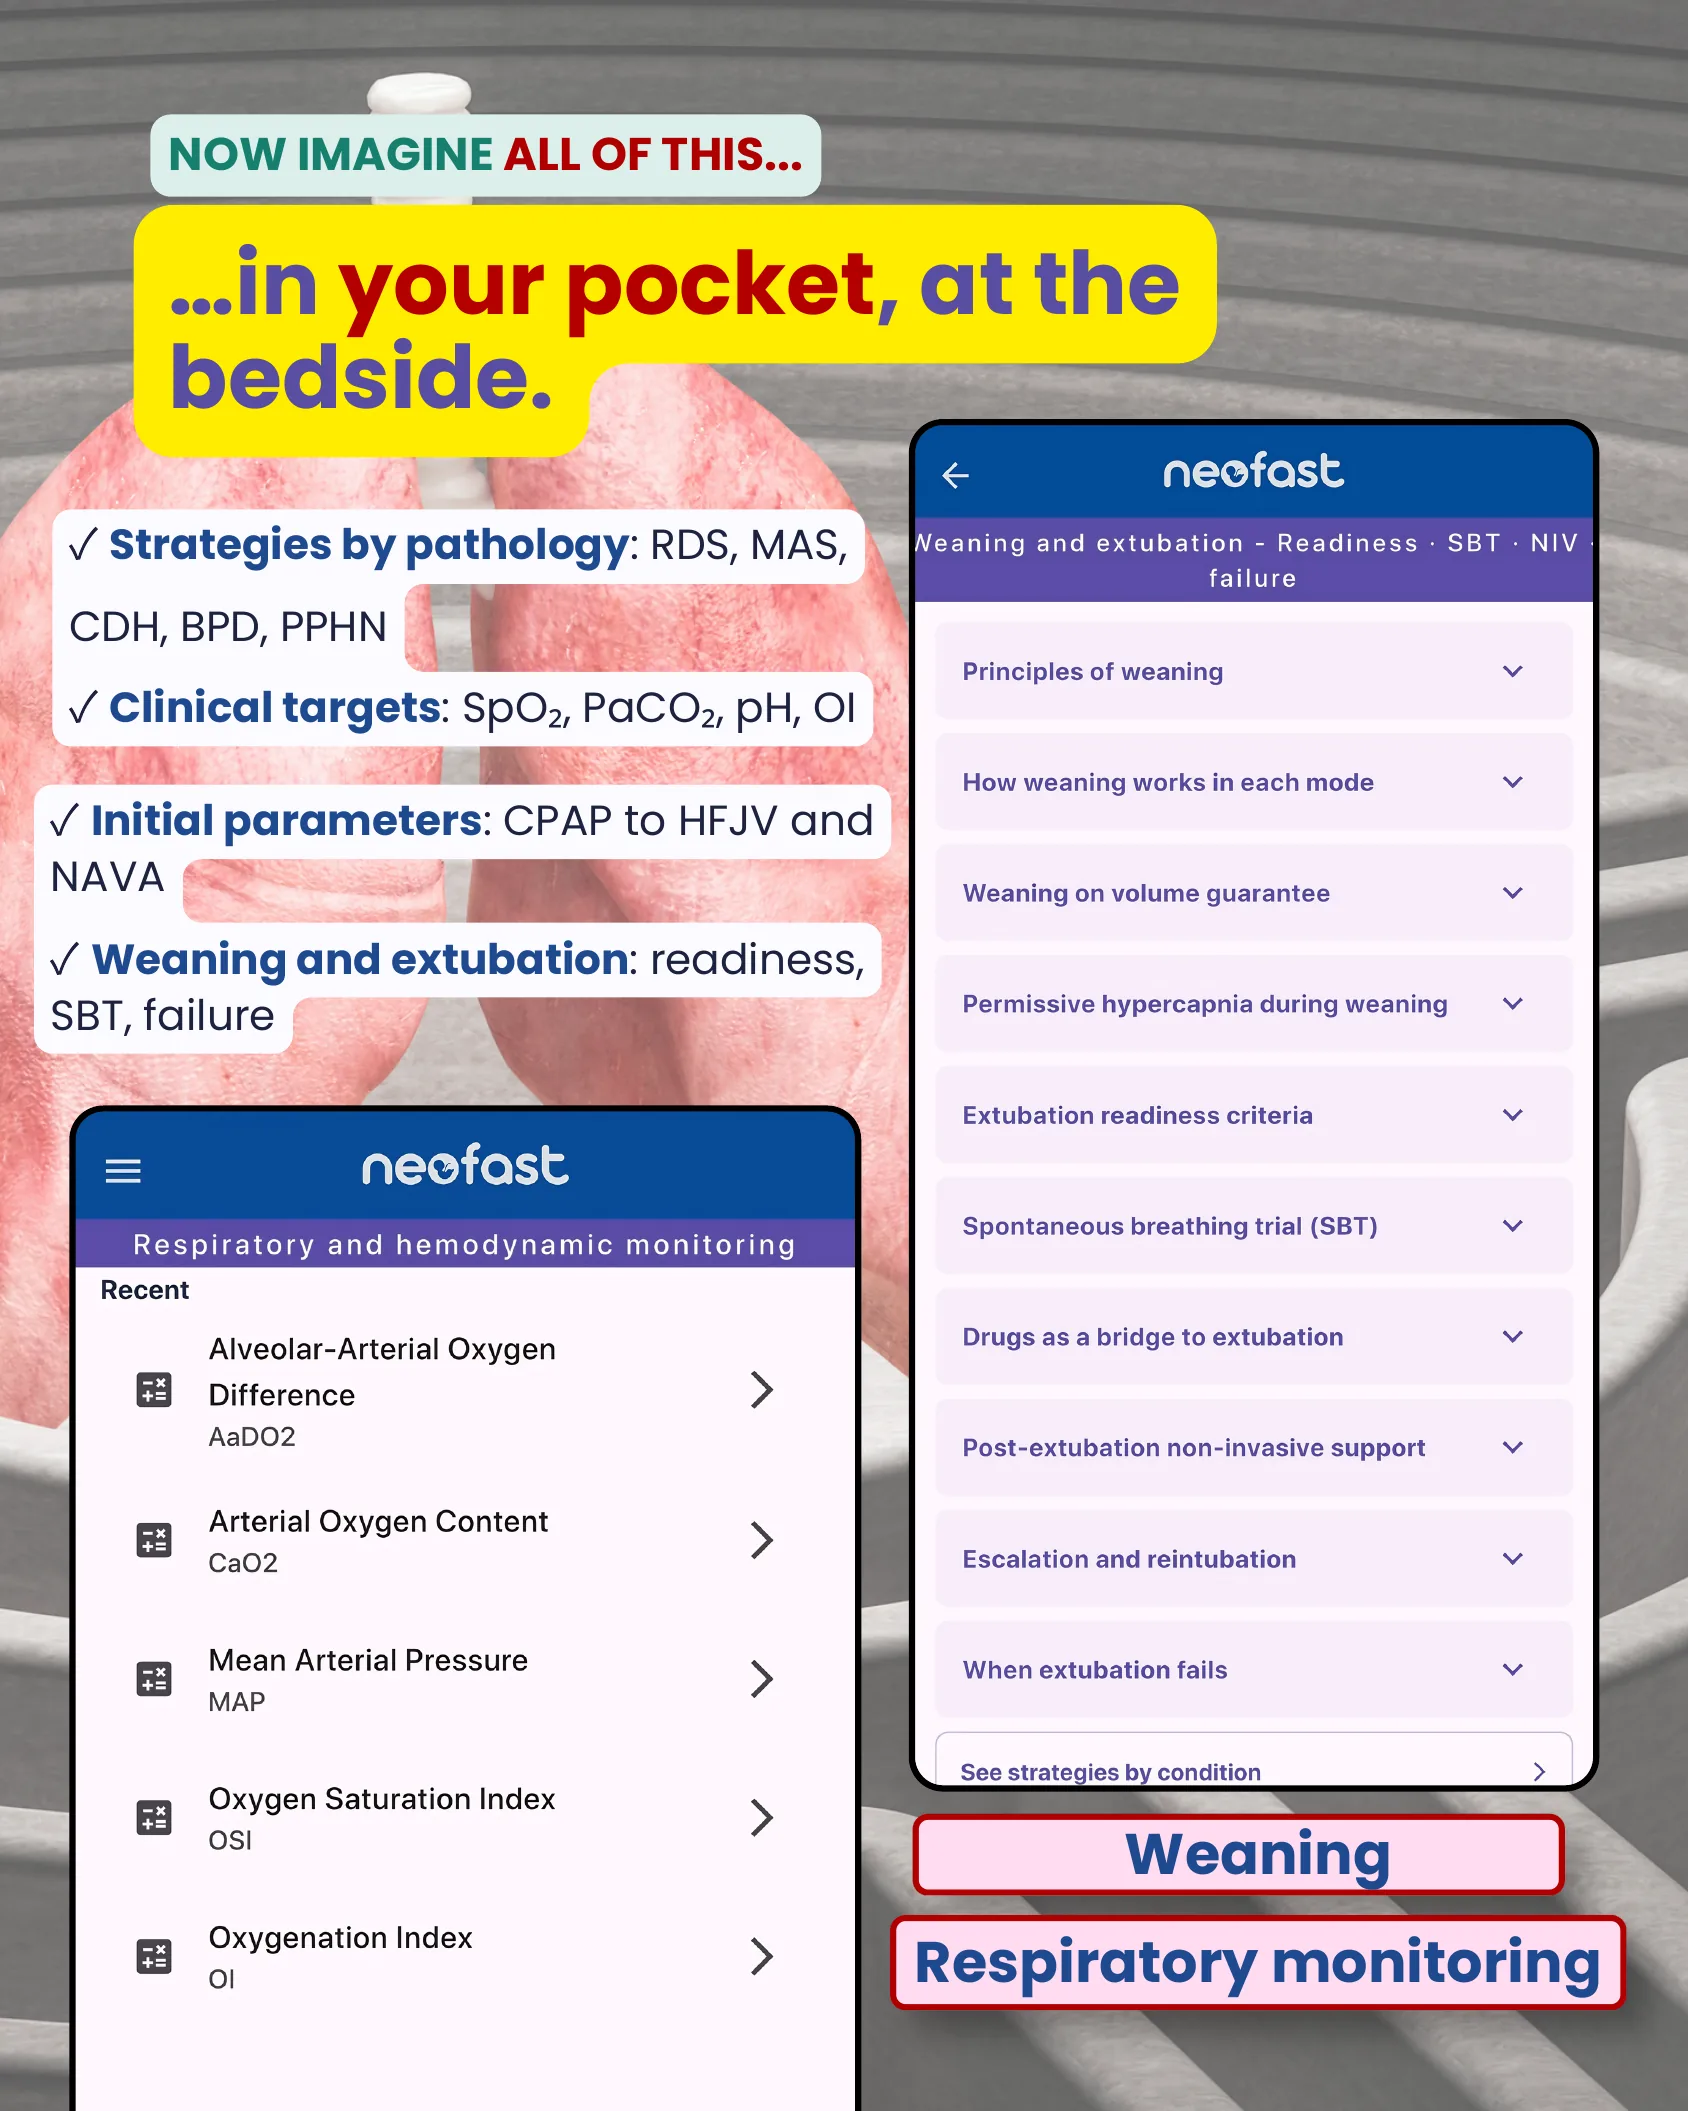
NOW IMAGINE ALL OF THIS…
…in your pocket, at the bedside.
- ✓ Strategies by pathology: RDS, MAS, CDH, BPD, PPHN
- ✓ Clinical targets: SpO₂, PaCO₂, pH, OI
- ✓ Initial parameters: CPAP to HFJV and NAVA
- ✓ Weaning and extubation: readiness, SBT, failure
Respiratory and hemodynamic monitoring
Recent
- Alveolar-Arterial Oxygen Difference (AaDO2)
- Arterial Oxygen Content (CaO2)
- Mean Arterial Pressure (MAP)
- Oxygen Saturation Index (OSI)
- Oxygenation Index (OI)
Weaning and extubation – Readiness · SBT · NIV failure
- Principles of weaning
- How weaning works in each mode
- Weaning on volume guarantee
- Permissive hypercapnia during weaning
- Extubation readiness criteria
- Spontaneous breathing trial (SBT)
- Drugs as a bridge to extubation
- Post-extubation non-invasive support
- Escalation and reintubation
- When extubation fails
- See strategies by condition
Download NeoFast
LESS SEARCHING. MORE CARING.
Stop flipping pages. Start ventilating with confidence.
Download NeoFast
neofastapp.com
- Get it on Google Play
- Download on the App Store
↓ Save this carousel for your next shift
→ Send it to your NICU team
- Venous hydration
- Continuous medication
- Medicines
- Intubation
- Other calculations and scores
- Procedures
- Respiratory and hemodynamic monitoring
- Growth and Development
Educational content. Settings are suggested starting points from the cited chapter; always individualize to the patient and follow your unit’s protocols. Source: Yoder BA, Grubb PH. In: Keszler M, Gautham KS, eds. Goldsmith’s Assisted Ventilation of the Neonate. 7th ed. Elsevier; 2022. Ch. 25.
Frequently asked questions
What are the initial volume-targeted SIMV settings for RDS?
For RDS, use VT 4–6 mL/kg, rate 30–60/min, I-time 0.30–0.35 s, PEEP 5–8 cmH2O, PS set to ⅔–¾ of the set VT, plus surfactant.
What HFOV settings are recommended for CDH / lung hypoplasia?
For CDH/lung hypoplasia on HFOV: frequency 8–10 Hz, Paw 10–12 cmH2O (max Paw rarely >16), ΔP 24–28, I:E 1:2, initial FiO2 0.40, with PaCO2 goal 45–55 mmHg (tolerated <65 mmHg) and chest X-ray target of ~9-rib inflation of the contralateral lung.
Why does MAS need a different HFJV rate than RDS?
MAS causes air trapping from heterogeneous airway disease, so HFJV rate is kept at 240–360/min (passive exhalation) to give the lung time to empty, compared to 360–420/min used in RDS.
What PaCO2 and PEEP targets are used for severe BPD?
Severe-chronic BPD targets PaCO2 50–60 mmHg (permissive hypercapnia accepting compensated respiratory acidosis), with PEEP often 8–10 cmH2O (up to 14 cmH2O in cases of malacia, with caution for regional overinflation).
What are the extubation thresholds by weight for infants <1000 g?
For infants <1000 g: on HFOV, Paw 8 and ΔP 16 with FiO2 <0.40; on PC-SIMV/SIMV+VG with PSV, PIP <16, PEEP <6, PS <6–8, FiO2 <0.40, rate 16–20/min, and VT 4–5 mL/kg if using volume guarantee.

